Related Experiment Video
Updated: Aug 3, 2025


Standardized Model of Ventricular Fibrillation and Advanced Cardiac Life Support in Swine
Published on: January 30, 2020
Center-Level Variation in Failure to Rescue After Elective Adult Cardiac Surgery
Arjun Verma1, Syed Shahyan Bakhtiyar2, Nikhil Chervu3
1Cardiovascular Outcomes Research Laboratories (CORELAB), David Geffen School of Medicine at UCLA, University of California Los Angeles, Los Angeles, California.

Background:
There has been increasing emphasis on evaluation of failure to rescue (FTR) after major inpatient operations. The present study characterized center-level variation in FTR within a national cohort of patients undergoing elective cardiac operations.
Methods:
All adults undergoing elective coronary artery bypass grafting and/or valve operations were identified in the 2016-2019 Nationwide Readmissions Database. FTR was defined as in-hospital death after prolonged mechanical ventilation, stroke, reoperation, acute kidney injury requiring dialysis, sepsis, cardiac arrest or pulmonary embolism. Multi-level, mixed-effects regressions were used to model mortality, complications, and FTR. Centers with high hospital-specific rates of FTR (≥95th percentile) were identified and compared to others.
Results:
Of an estimated 454,506 patients included for analysis, 32,537 (7.2%) developed at least 1 complication, and 7669 (1.7%) died before discharge. Overall, 5370 (16.5%) patients experienced FTR. Compared with those who developed ≥1 complication but survived to discharge, FTR patients were significantly older, more commonly female, and had a greater burden of comorbidities as measured by the Elixhauser Comorbidity Index. Risk-adjusted, hospital-specific rates of mortality and FTR were moderately correlated (r = 0.64), mortality and complications were weakly associated (r = 0.16), and complications and FTR exhibited a very weak relationship (r = -0.02). Relative to others, centers with high rates of FTR had lower annual cardiac surgical volume (median 61 [interquartile range 33-133] vs 80 [interquartile range 43-149] cases/y, P = .019).
Conclusions:
The present findings affirm prior work demonstrating a close link between variation in FTR and mortality, but not complications. Further study is necessary to delineate modifiable care pathways that mitigate FTR.
More Related Videos
 04:55
Author Spotlight: Simulating Pediatric Cardiac Surgery Using a Neonatal Piglet Model
Published on: May 26, 2023
 08:19
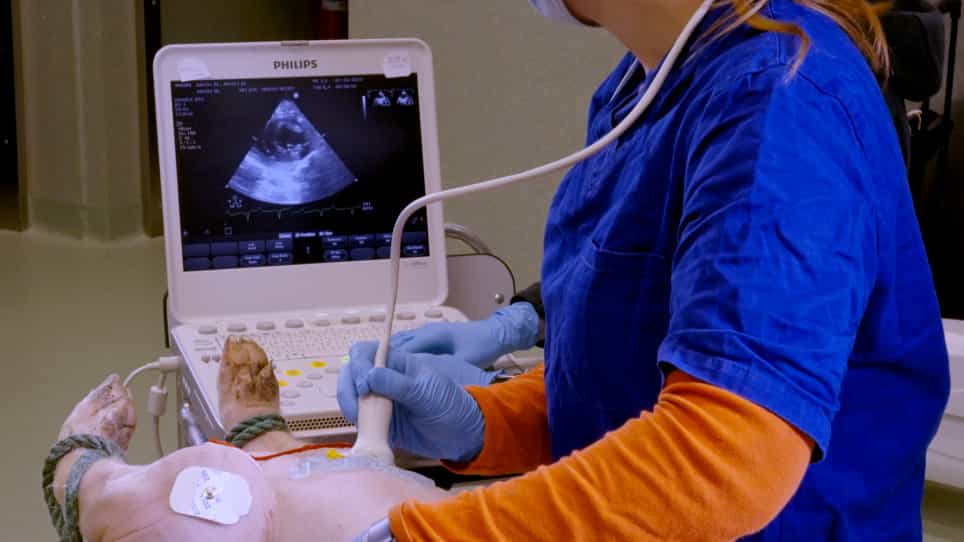
Transthoracic Echocardiography to Assess Post-Resuscitation Left Ventricular Dysfunction After Acute Myocardial Infarction and Cardiac Arrest in Pigs
Published on: July 12, 2022
Related Concept Videos
 01:21
Cardiopulmonary Resuscitation I: Adult
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:23
Cardiopulmonary Resuscitation III: AED Use
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:29
Cardiomyopathy V: Interprofessional Care
 01:26
Cardiac Catheterization IV: Nursing Management