Related Experiment Video
Updated: Aug 1, 2026


Modeling Encephalopathy of Prematurity Using Prenatal Hypoxia-ischemia with Intra-amniotic Lipopolysaccharide in Rats
Published on: November 20, 2015
Case report: Fatal cerebral herniation caused by hypoglycemic due to mistaking glibenclamide in children
Chunlan Song1, Wanyu Jia1, Shengli Shi1
1Children's Hospital Affiliated to Zhengzhou University, Henan Children's Hospital, Zhengzhou, China.

Insights
A child in China accidentally ingested glibenclamide, a diabetes medication, leading to fatal hypoglycemia and brain herniation. This case highlights the critical need for awareness of accidental drug ingestion in children.
Area of Science:
- Pediatrics
- Toxicology
- Endocrinology
Background:
- Glibenclamide is a common hypoglycemic agent used in China.
- Increased prevalence of diabetes and a significant population of 'left-behind' children in China raise concerns for accidental medication ingestion.
- Accidental ingestion of medications by children is a serious public health issue.
Observation:
- A case report details a child who mistakenly ingested glibenclamide.
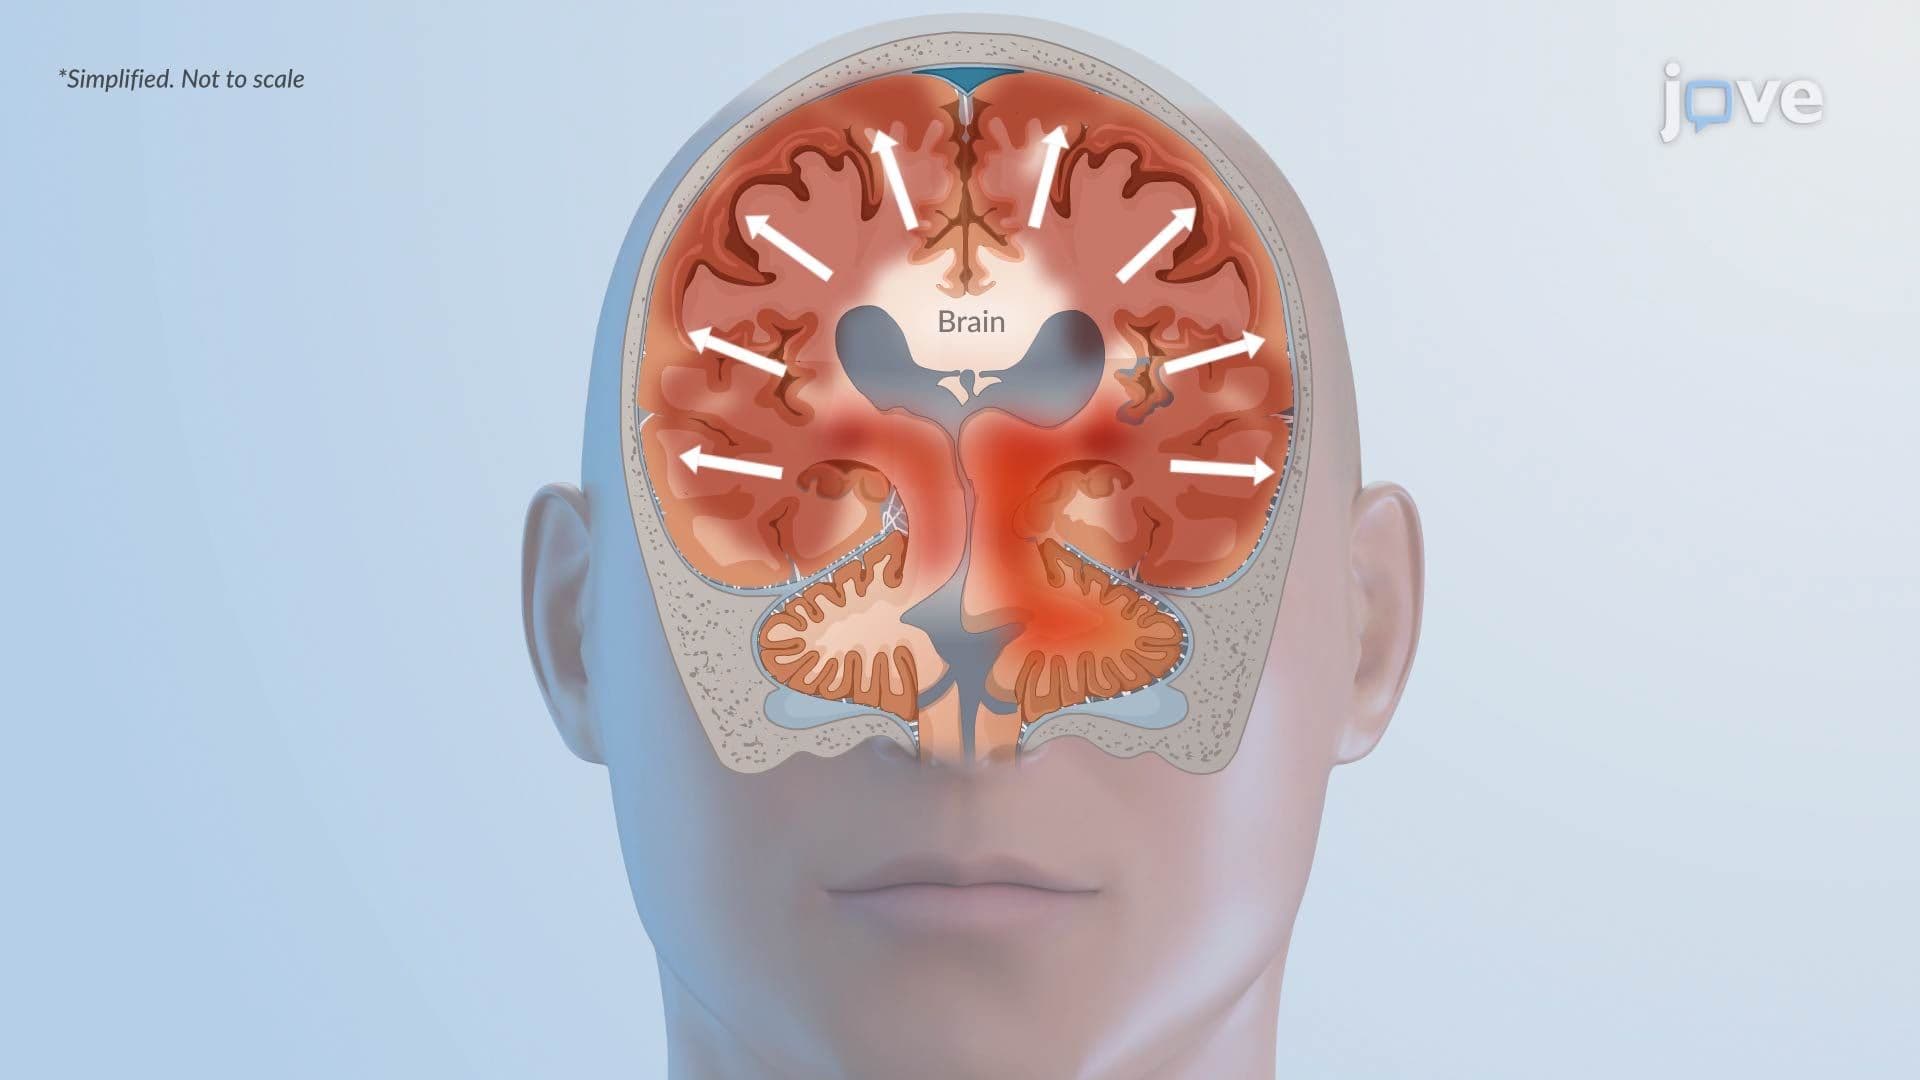
- The child developed severe hypoglycemia, leading to cerebral edema and brain herniation.
- This represents the first reported pediatric fatality from glibenclamide-induced brain herniation in China.
Findings:
- Accidental glibenclamide ingestion can cause severe hypoglycemia in children.
- Hypoglycemia can rapidly progress to life-threatening complications like cerebral edema and brain herniation.
- Delayed recognition and treatment of hypoglycemia increase mortality risk.
Implications:
- Clinicians must consider accidental glibenclamide ingestion in children presenting with unexplained seizures and coma.
- Detailed medical history is crucial for diagnosing non-obvious causes of pediatric emergencies.
- Prompt administration of high-concentration glucose is vital for managing hypoglycemia and preventing severe neurological damage.
- Pediatricians should maintain a high index of suspicion for accidental medication exposure in children with altered consciousness.
Abstract:
In recent years, the prevalence of diabetes in China has significantly increased, and glibenclamide is widely used as a basic hypoglycemic drug in China's primary clinical practice. There are many left-behind children in the grass-roots areas in China and various dangerous incidents of children taking drugs by mistake continue to occur. This article reports a case of cerebral edema and fatal cerebral hernia caused by hypoglycemia induced by mistakenly ingesting glibenclamide in a child. This is the first reported case in China of a child who died from brain herniation caused by accidental administration of glibenclamide. This case reminded that clinicians must comprehensively consider the cause of convulsions and coma in children with unknown causes, ask the history in detail and cannot ignore the risk of hypoglycemic convulsions and coma. When hypoglycemic is detected, high concentration of glucose should be given promptly to normalize blood glucose. When dealing with unexplained convulsions and comatose children, clinical pediatricians must be alert to the possibility of accidental medication.
More Related Videos


Related Concept Videos
 01:20
Inborn Errors of Metabolism
 01:15
Hypoglycemia and Glucagon
 01:26
Hypoglycemia
 01:29
Hyperglycemia
 01:19
Cerebral Edema l: Introduction
 01:21
Cytotoxic Edema: Pathophysiology