Related Experiment Video
Updated: Aug 3, 2025
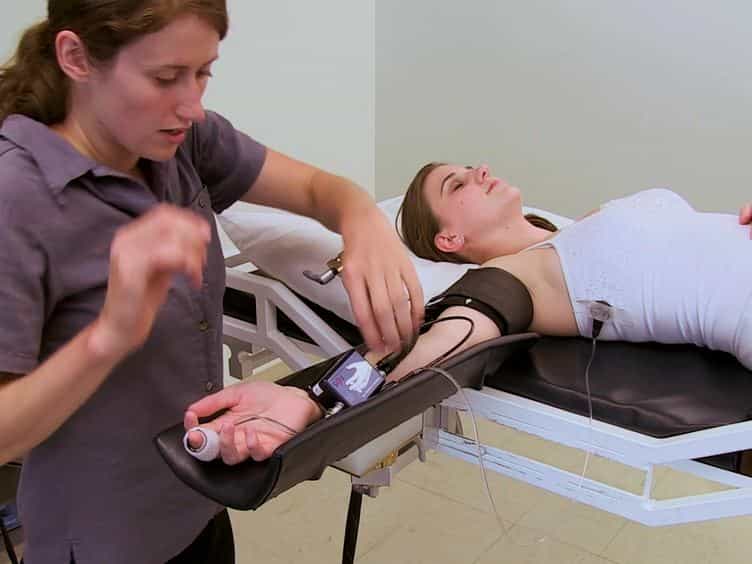

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
Syncope Diagnosis at Referral to a Tertiary Syncope Unit: An in-Depth Analysis of the FAST II
Jelle S Y de Jong1, Steven van Zanten2, Roland D Thijs3,4
1Department of Clinical and Experimental Cardiology, Heart Center, Amsterdam Cardiovascular Sciences, Amsterdam UMC, University of Amsterdam, 1105 AZ Amsterdam, The Netherlands.

Objective:
A substantial number of patients with a transient loss of consciousness (T-LOC) are referred to a tertiary syncope unit without a diagnosis. This study investigates the final diagnoses reached in patients who, on referral, were undiagnosed or inaccurately diagnosed in secondary care.
Methods:
This study is an in-depth analysis of the recently published Fainting Assessment Study II, a prospective cohort study in a tertiary syncope unit. The diagnosis at the tertiary syncope unit was established after history taking (phase 1), following autonomic function tests (phase 2), and confirming after critical follow-up of 1.5-2 years, with the adjudicated diagnosis (phase 3) by a multidisciplinary committee. Diagnoses suggested by the referring physician were considered the phase 0 diagnosis. We determined the accuracy of the phase 0 diagnosis by comparing this with the phase 3 diagnosis.
Results:
51% (134/264) of patients had no diagnosis upon referral (phase 0), the remaining 49% (130/264) carried a diagnosis, but 80% (104/130) considered their condition unexplained. Of the patients undiagnosed at referral, three major causes of T-LOC were revealed: reflex syncope (69%), initial orthostatic hypotension (20%) and psychogenic pseudosyncope (13%) (sum > 100% due to cases with multiple causes). Referral diagnoses were either inaccurate or incomplete in 65% of the patients and were mainly altered at tertiary care assessment to reflex syncope, initial orthostatic hypotension or psychogenic pseudosyncope. A diagnosis of cardiac syncope at referral proved wrong in 17/18 patients.
Conclusions:
Syncope patients diagnosed or undiagnosed in primary and secondary care and referred to a syncope unit mostly suffer from reflex syncope, initial orthostatic hypotension or psychogenic pseudosyncope. These causes of T-LOC do not necessarily require ancillary tests, but can be diagnosed by careful history-taking. Besides access to a network of specialized syncope units, simple interventions, such as guideline-based structured evaluation, proper risk-stratification and critical follow-up may reduce diagnostic delay and improve diagnostic accuracy for syncope.
More Related Videos

Related Concept Videos
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:30
Heart Failure IV: Classification and Diagnostic Evaluation
 01:30
Dysrhythmias V: Evaluating Dysrhythmias
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy