Underweight predicts extubation failure after planned extubation in intensive care units
Related Experiment Video
Updated: Aug 2, 2025
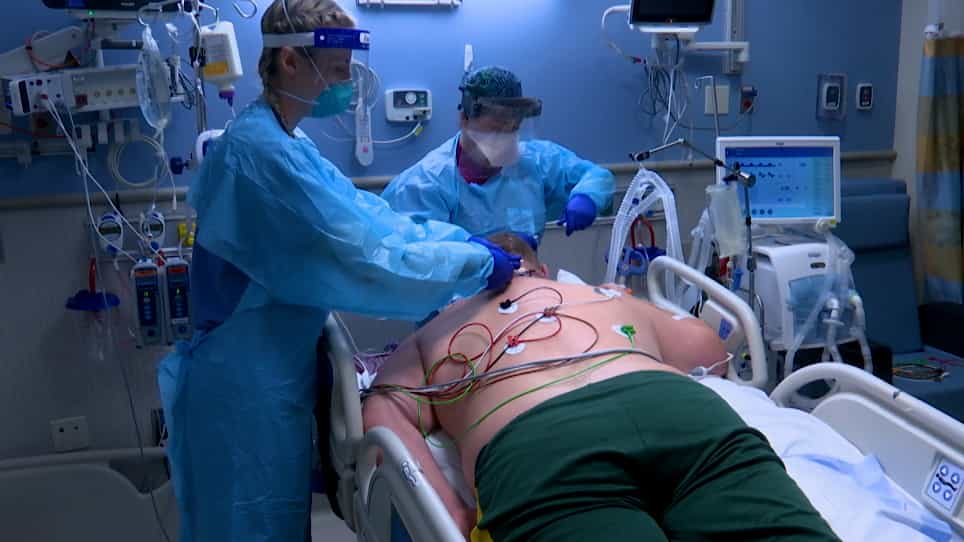
An Educational Video Demonstration of How to Prone a Critically Ill Intubated Patient
Published on: November 30, 2022
Chung-Yeh Chuang1,2, Han-Shui Hsu1,3, Guan-Jhou Chen4,5
1Institute of Emergency and Critical Care Medicine, National Yang-Ming Chiao Tung University, Taipei, Taiwan.

Insights
Underweight patients face a higher risk of extubation failure after mechanical ventilation. Lower inspiratory muscle strength also significantly increases this risk in critical care settings.
Area of Science:
- Critical Care Medicine
- Pulmonology
- Clinical Nutrition
Background:
- Body weight is a known factor influencing physiological changes, with implications for mortality in critical care.
- Previous research has explored the link between weight and mortality, but the specific impact on post-extubation outcomes requires further investigation.
Purpose of the Study:
- To investigate the association between underweight status and the incidence of post-extubation failure in patients requiring mechanical ventilation in intensive care units (ICUs).
- To identify potential risk factors contributing to extubation failure in this vulnerable patient population.
Main Methods:
- A retrospective cohort study was conducted involving 268 patients who underwent prolonged mechanical ventilation (>72 hours) and a planned extubation.
- Data on demographic and clinical characteristics were collected, and extubation failure was defined as reintubation within 72 hours.
- Multivariate logistic regression analysis was employed to determine risk factors for extubation failure.
Main Results:
- The overall extubation failure rate was 7.1% (19/268).
- Underweight patients exhibited the highest risk of extubation failure (8/50).
- Multivariate analysis revealed that being underweight (adjusted OR, 3.80) and lower maximal inspiratory pressure (adjusted OR per 1 cmH2O decrease, 1.05) were significantly associated with increased extubation failure.
Conclusions:
- Underweight status is a significant risk factor for post-extubation respiratory failure following planned extubation in critically ill patients.
- Reduced maximal inspiratory airway pressure is also independently associated with a higher likelihood of extubation failure.
Background:
Body weight is associated with different physiological changes and the association between weight and mortality in critical care setting had been discussed before. In this study, we investigated the linkage between underweight and post-extubation failure in mechanical ventilated patients in critical setting.
Methods:
This is a retrospective cohort study including patients who were admitted to medical or surgical intensive care units (ICU) between June 2016 and July 2018 and had received endotracheal intubation for more than 72 hours. Those who passed spontaneous breathing trial and underwent a planned extubation were enrolled. Extubation failure was defined as those who required reintubation within the first 72 hours for any reasons. The probability of extubation failure was calculated. Demographic and clinical characteristics were recorded. Multivariate logistic regression models were then used to determine the potential risk factors associated with extubation failure.
Results:
Overall, 268 patients met the inclusion criteria and were enrolled in our study for analysis. The median age of included patients was 67 years (interquartile range, 55-80 years) with 65.3% being male; 63.1% of the patients were included from medical ICU. The proportion of extubation failure in our cohort was 7.1% (19/268; 95% confidence interval [CI], 4.3-10.9%). Overall, underweight patients had the highest risk of extubation failure (8/50), as compared with normoweight (9/135) and overweight patients (2/83). In the multivariate analysis, being underweight (adjust OR [aOR], 3.80, compared to normoweight; 95% CI, 1.23-11.7) and lower maximal inspiratory airway pressure (aOR per one cmH2O decrease, 1.05; 95% CI 1.00-1.09) remained significantly associated with extubation failure.
Conclusion:
In our study, being underweight and lower maximal inspiratory airway pressure was associated with post-extubation respiratory failure after a planned extubation.
Related Concept Videos
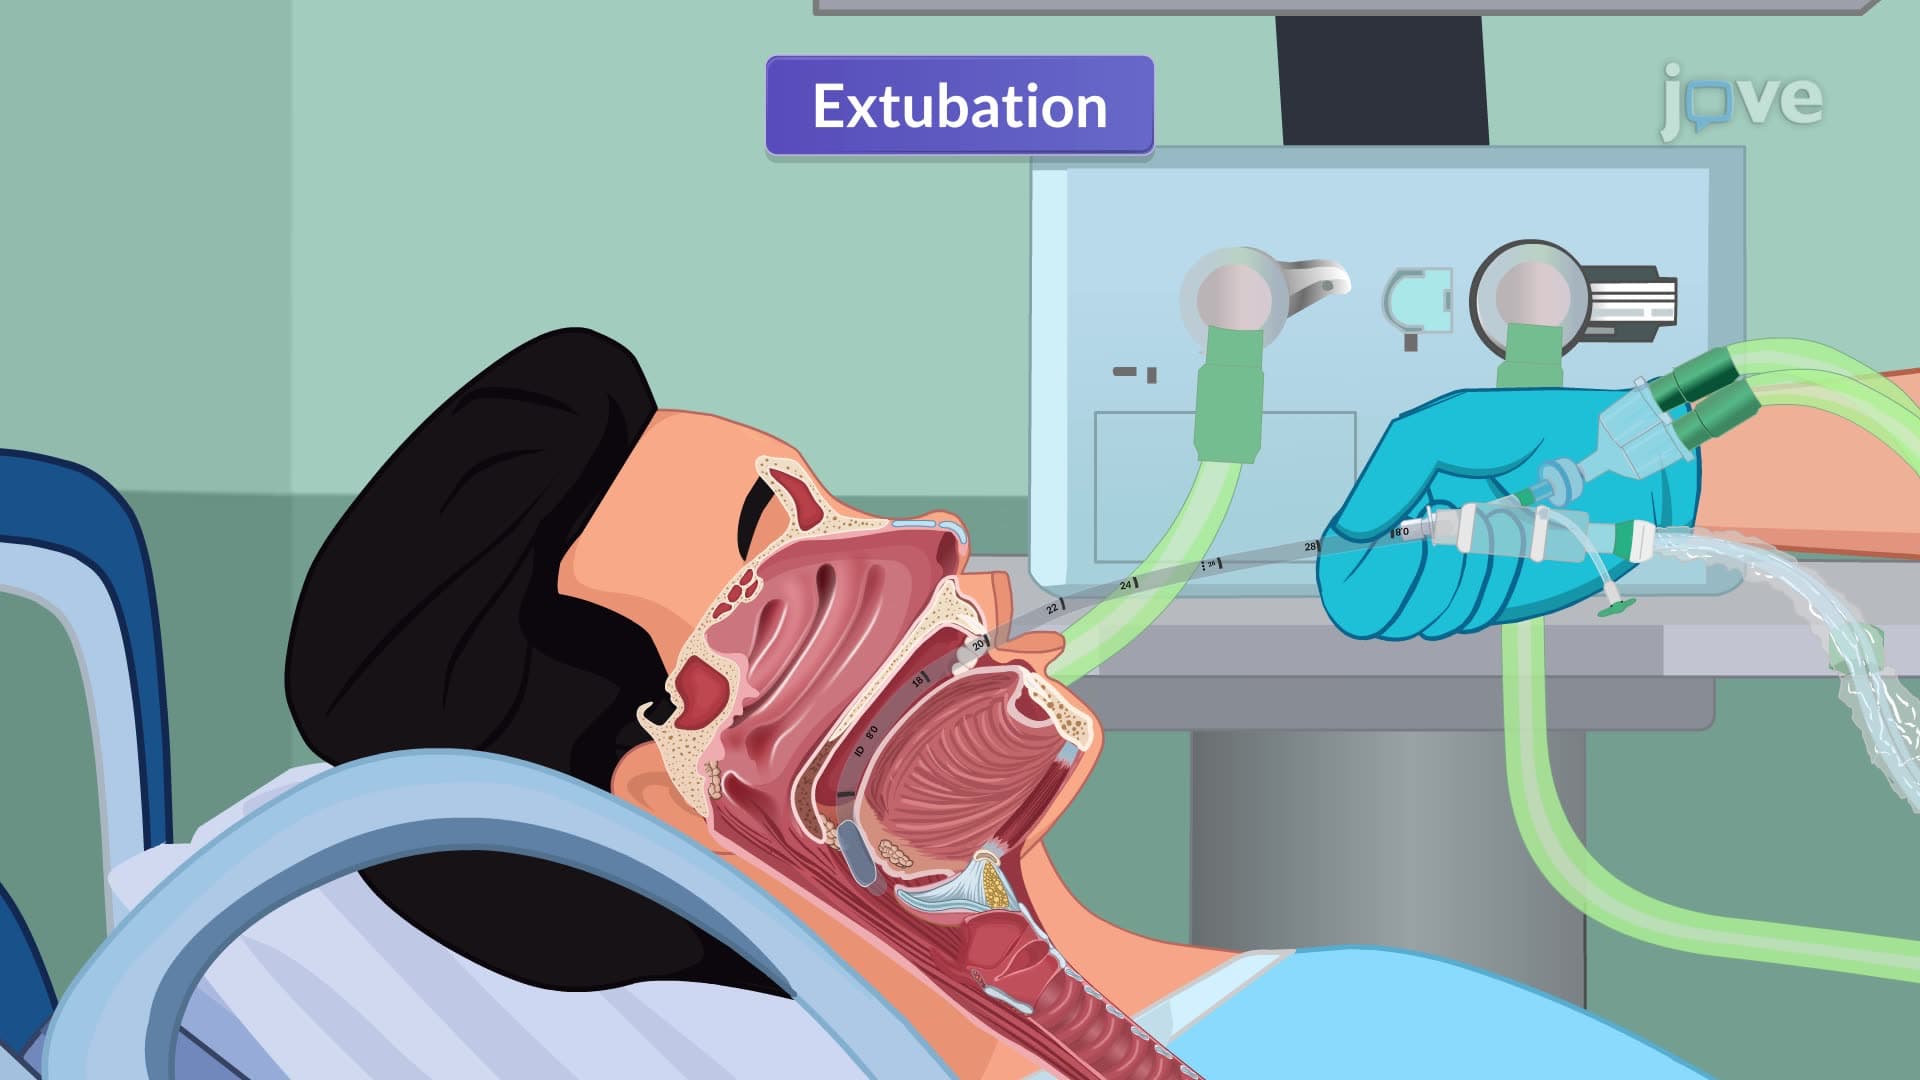 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
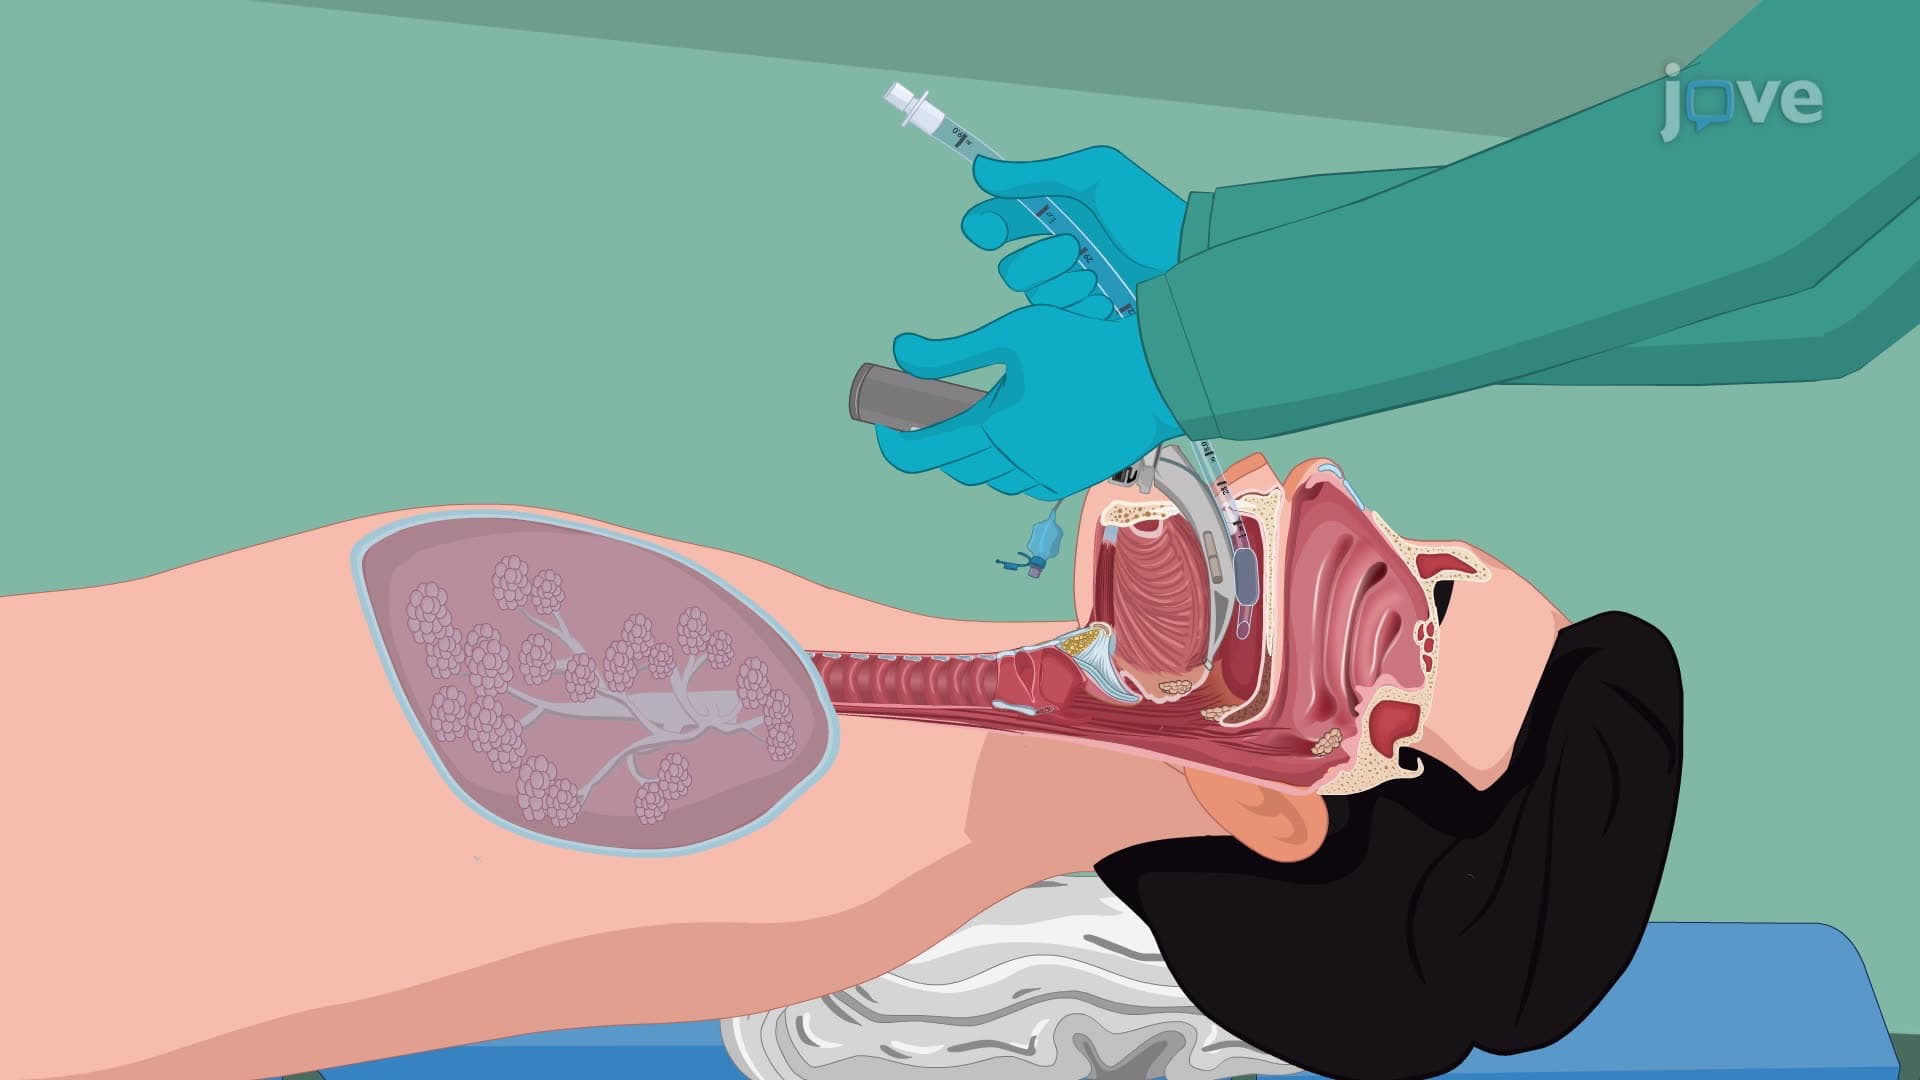
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:15
Endotracheal Intubation I: Procedure
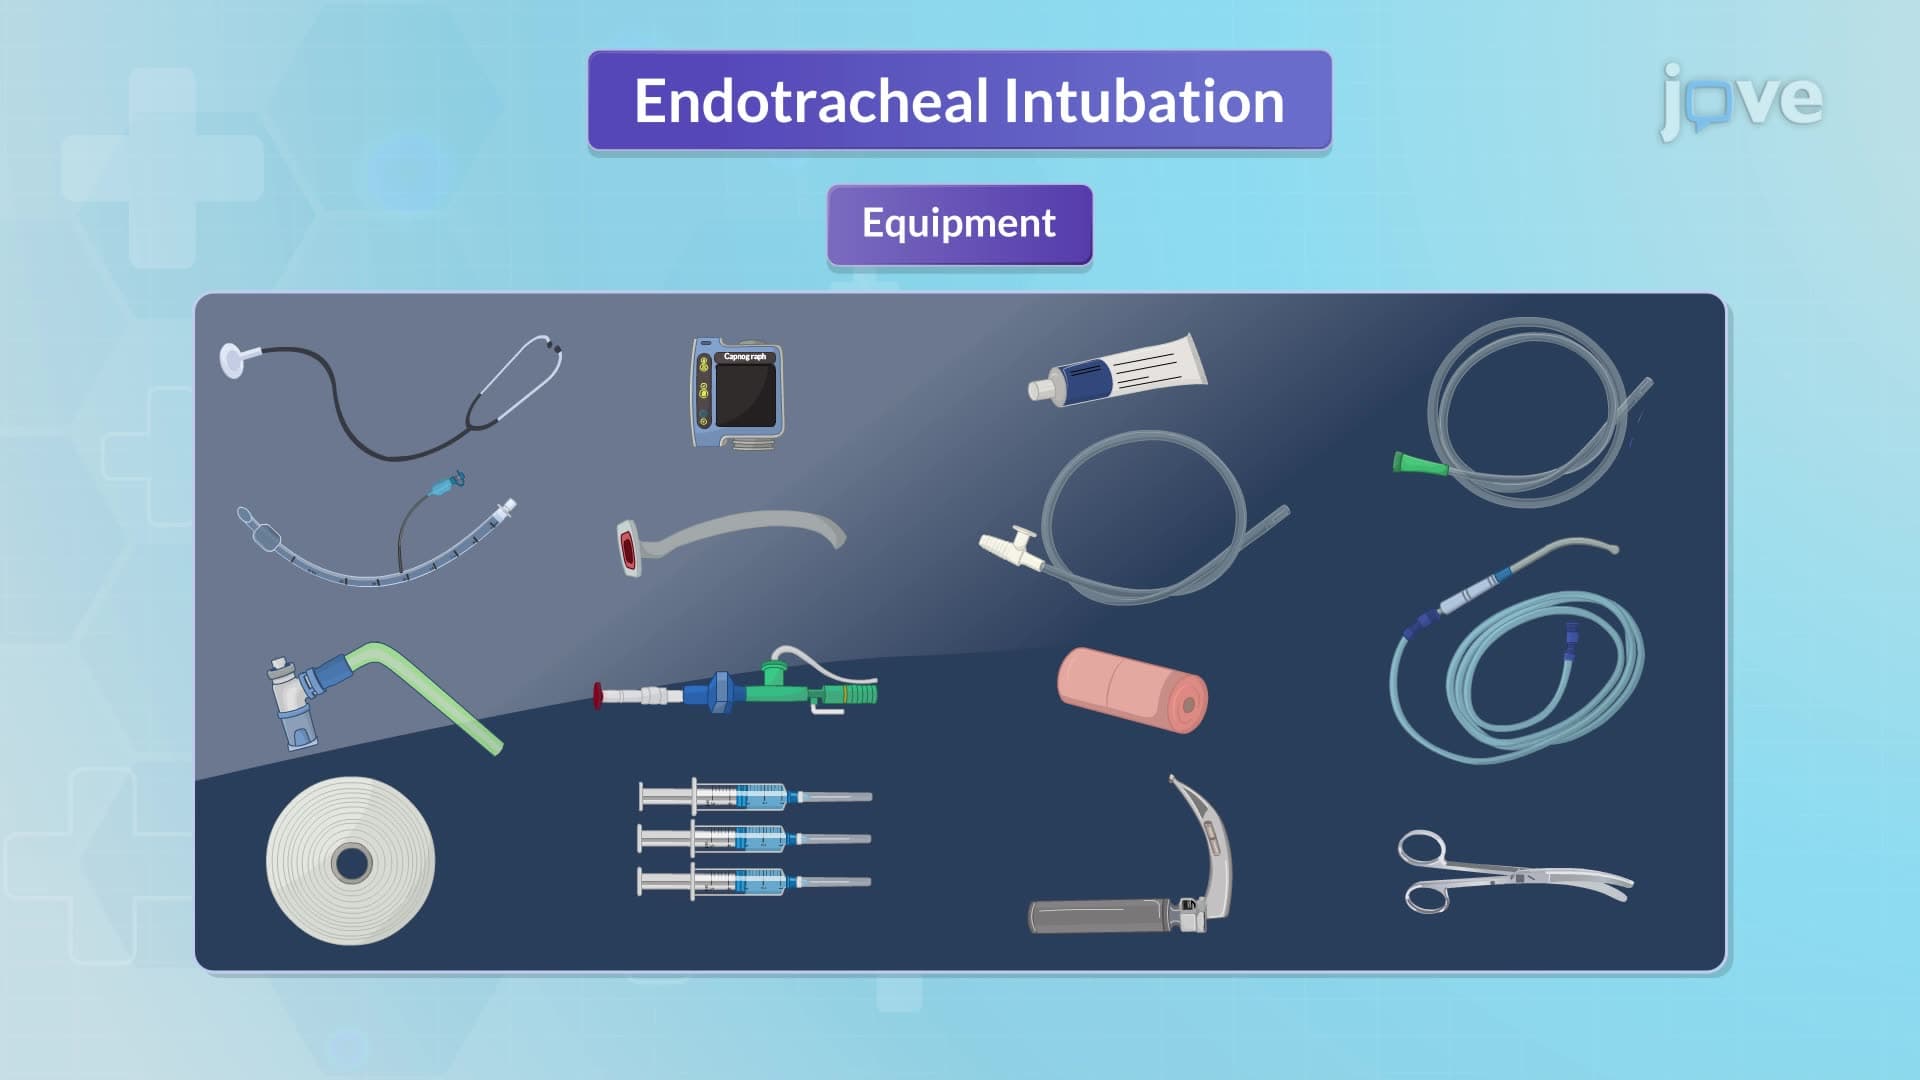
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:30
Acute Respiratory Failure-III