Related Experiment Video
Updated: Aug 2, 2025

Microsurgical Creation of Giant Bifurcation Aneurysms in Rabbits for the Evaluation of Endovascular Devices
Published on: September 8, 2023
Outcomes of Complex Endovascular Treatment of Post-Dissection Aneurysms
Thomas F X O'Donnell1, Priya B Patel2, Christina L Marcaccio3
1Department of Surgery, Division of Vascular and Endovascular Surgery, Beth Israel Deaconess Medical Centre, Harvard Medical School, Boston, MA, USA; Division of Cardiac, Thoracic, and Vascular Surgery, New York-Presbyterian/Columbia University Irving Medical Centre/Columbia University Vagelos College of Physicians & Surgeons, New York, NY, USA.

Objective:
Reports of endovascular treatment of chronic post-dissection aneurysms are limited to high volumes centres, posing questions about generalisability.
Methods:
All endovascular repairs of intact pararenal and thoraco-abdominal aneurysms in the Vascular Quality Initiative from 2014 to 2021 were studied, and peri-operative and long term outcomes were compared between repairs of degenerative and post-dissection aneurysms. Peri-operative outcomes were compared using mixed effects logistic regression, and long term outcomes using Medicare linkage.
Results:
There were 123 patients who completed treatment for post-dissection aneurysms and 3 635 for degenerative aneurysms, with 36% of post-dissection repairs and 6.7% of degenerative repairs performed in a staged fashion (p < .001). The majority (84%) of post-dissection aneurysms were extensive thoraco-abdominal aneurysms (TAAAs: Crawford Type 1, 2, 3, 5), compared with 22% of degenerative aneurysms (p < .001). Physician modified endografts were the primary repair type for post-dissection (73%), while commercially available fenestrated grafts were the dominant repair for degenerative (48%). The first stage of staged procedures was associated with a 2.8% peri-operative mortality rate, 5.1% spinal cord ischaemia, and 8.9% thoraco-abdominal life altering events (the composite of peri-operative death, stroke, permanent spinal cord ischaemia, and dialysis). Th final stage procedure and fluoroscopy times were similar, but technical success was lower in post-dissection repairs (75% vs. 83%, p = .018), both due to issues with the main endograft or bridging vessels (11% vs. 6.6%, p = .055), and types 1and 3 endoleak at completion (17% vs. 10%, p = .035). In addition, high volume surgeons had two fold higher odds of technical success than their low volume counterparts. Adjusted peri-operative outcomes were similar between pathology types, including when comparisons were restricted to extensive TAAAs. Crude and adjusted three year survival were similar, but three year re-interventions were significantly higher following post-dissection repairs (p < .001).
Conclusion:
Complex endovascular repair of chronic post-dissection aneurysms is feasible but is associated with high rates of re-interventions and non-trivial rates of lack of technical success. More data are needed to evaluate the long term durability of these procedures, and the utility of centralising these complex procedures.


Related Concept Videos
 01:26
Aneurysm III: Interprofessional Care
 01:22
Aneurysm IV: Nursing Management
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:29
Venous Thrombosis III: Interprofessional Care
 01:19
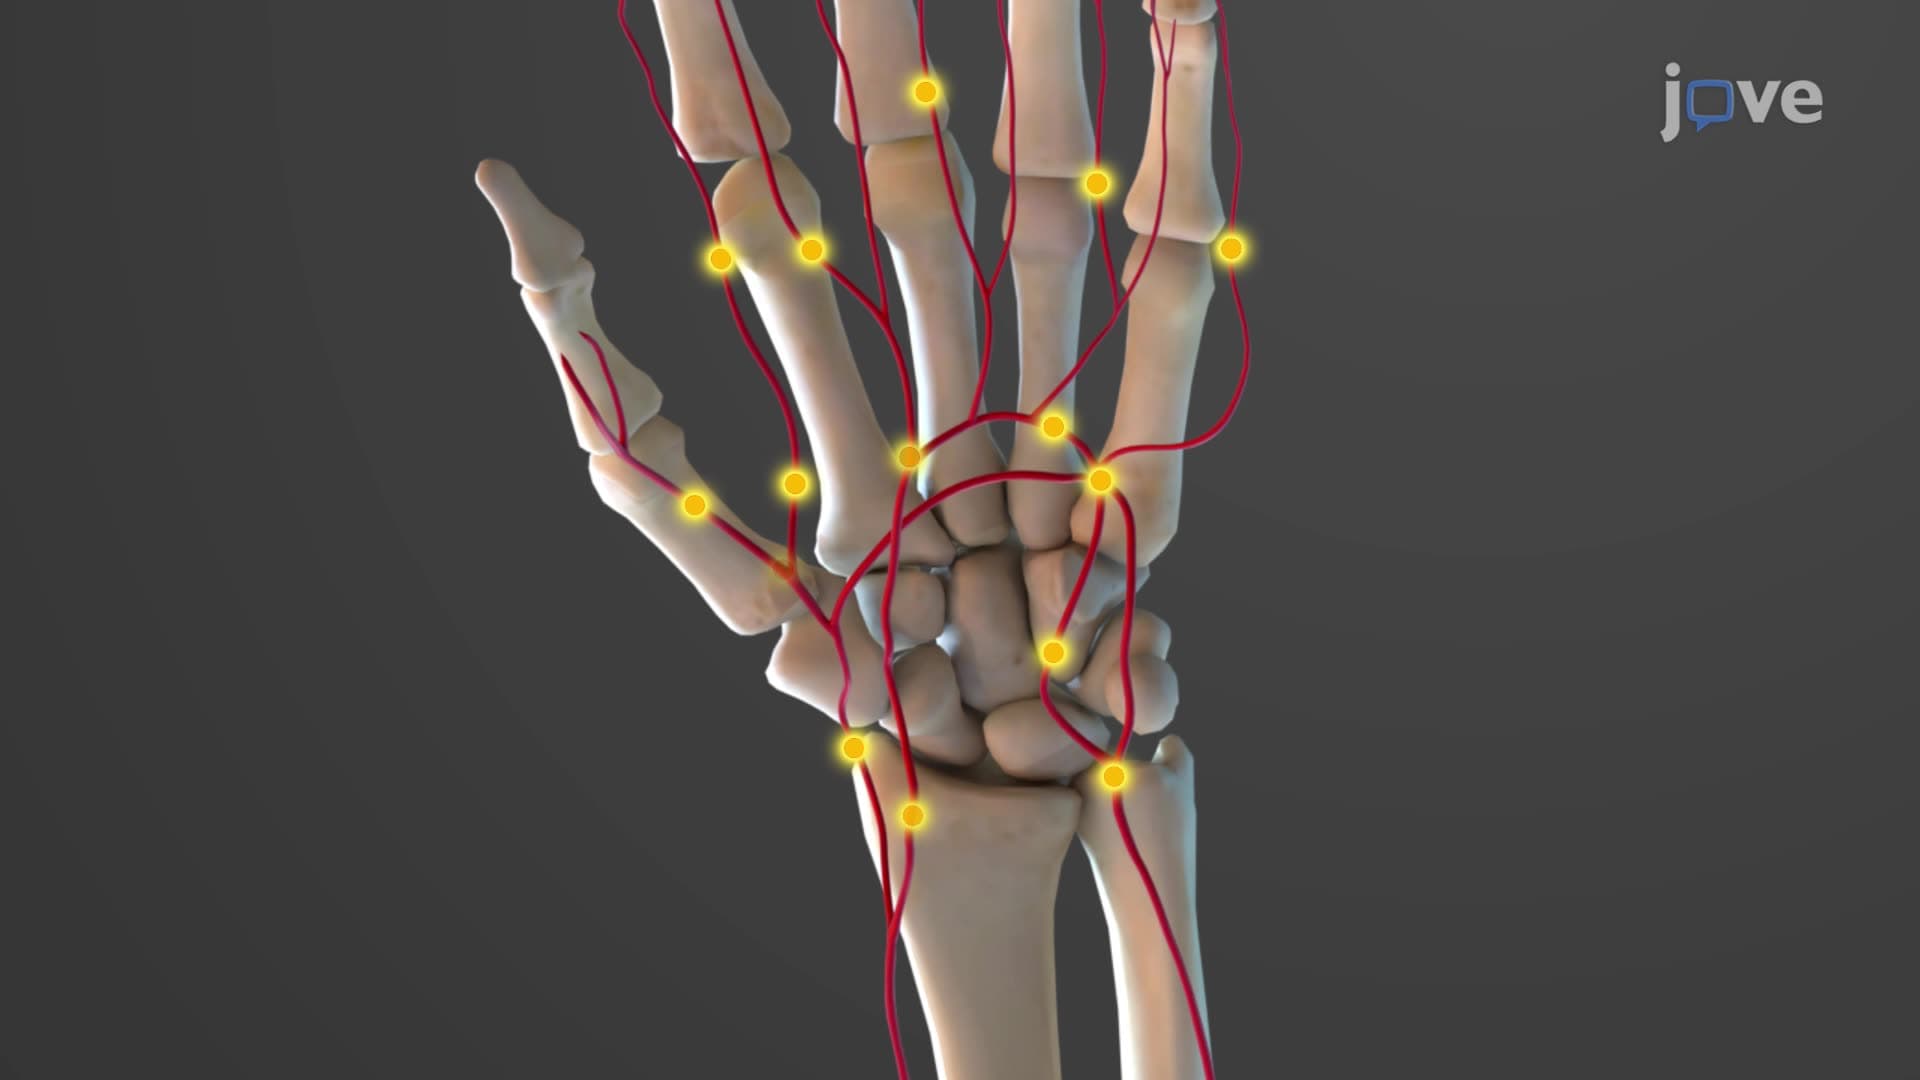
Anastomoses
Anastomoses can be formed at arterial, venous, and lymphatic vessels.
Arterial Anastomosis: These occur between arteries. They...