Related Experiment Video
Updated: Aug 1, 2025

Author Spotlight: Assessment of Cardiac Output Calculation by Thermodilution in Pigs for Effective Perfusion Flow During EVLP
Published on: June 28, 2024
Comparison of cardiac index measurements in intensive care patients using continuous wave vs. pulsed wave
Prashant Parulekar1, James Powys-Lybbe2, Paul Bassett3
1Intensive Care and Acute Medicine, East Kent Hospitals University NHS Foundation Trust, William Harvey Hospital, London, UK. parulekar79@gmail.com.

Insights
Continuous wave Doppler velocity time integral (CW-VTI) may offer a more accurate assessment of cardiac index (CI) compared to pulsed wave Doppler (PW-VTI) in critical care. However, neither Doppler method may accurately reflect actual CI if using a 30% percentage error cutoff.
Area of Science:
- Critical care medicine
- Cardiovascular physiology
- Medical imaging and diagnostics
Background:
- Cardiac index (CI) is crucial for shock assessment and guiding resuscitation in critical care.
- Echocardiography offers a non-invasive method for CI assessment, showing good agreement with thermodilution methods.
- CI is calculated using the velocity time integral (VTI) divided by body mass index.
Purpose of the Study:
- To compare the accuracy of continuous wave Doppler (CW-VTI) and pulsed wave Doppler (PW-VTI) in assessing cardiac index against thermodilution.
- To evaluate the potential of CW-VTI as a more accurate echocardiographic method for CI assessment.
Main Methods:
- A prospective, observational study was conducted in a 15-bed intensive care unit.
- Simultaneous measurements of CI were performed using Pulse Contour Cardiac Output (PiCCO) thermodilution, transthoracic echocardiographic PW-VTI, and CW-VTI.
- Data analysis included Bland-Altman limits of agreement and percentage error (PE) calculations.
Main Results:
- Data from 52 patients, 71% on noradrenaline, were analyzed.
- Mean CIs: CW-VTI 2.7 L/min/m², PW-VTI 2.33 L/min/m², PiCCO 2.86 L/min/m².
- Percentage errors (PE) with PiCCO: CW-VTI 43.5%, PW-VTI 38.6%.
Conclusions:
- Both CW-VTI and PW-VTI methods underestimated CI compared to PiCCO.
- CW-VTI showed closer agreement with PiCCO than PW-VTI, suggesting potential for more accurate CI assessment.
- Neither Doppler method achieved a 30% PE, indicating potential limitations in accurately reflecting actual CI in this cohort.
Purpose:
Cardiac index (CI) assessments are commonly used in critical care to define shock aetiology and guide resuscitation. Echocardiographic assessment is non-invasive and has high levels of agreement with thermodilution assessment of CI. CI assessment is derived from the velocity time integral (VTI) assessed using pulsed wave (PW) doppler at the level of the left ventricular outflow tract divided by body mass index. Continuous wave (CW) doppler through the aortic valve offers an alternative means to assess VTI and may offer better assessment at high velocities.
Methods:
We performed a single centre, prospective, observational study in a 15-bed intensive care unit in a busy district general hospital. Patients had simultaneous measurements of cardiac index by Pulse Contour Cardiac Output (PiCCO) (thermodilution), transthoracic echocardiographic PW-VTI and CW-VTI. Mean differences were measured with Bland-Altman limits of agreement and percentage error (PE) calculations.
Results:
Data were collected on 52 patients. 71% were supported with noradrenaline with or without additional inotropic or vasopressor agents. Mean CIs were: CW-VTI 2.7 L/min/m2 (range 0.78-5.11, SD 0.92). PW-VTI 2.33 L/min/m2 (range 0.77-5.40, SD 0.90) and PiCCO 2.86 L/min/m2 (range 1.50-5.56, SD 0.93). CW-VTI and PiCCO mean difference was - 0.16 L/min/m2 PE 43.5%. PW-VTI and PiCCO had a mean difference of - 0.54 L/min/m2 PE 38.6%. CW-VTI and PW-VTI had a mean difference of 0.38 L/min/m2 PE 46.0%.
Conclusions:
CI derived from both CW-VTI and PW-VTI methods underestimate CI compared to PiCCO, with the CW-VTI method having closer values overall to PiCCO. CW-VTI may offer a more accurate assessment of CI. If using Critchley's PE cutoff of 30%, none of the doppler methods may accurately reflect the actual cardiac index.
Related Concept Videos
 01:30
Pulse rhythm
Conversely, an irregular pulse pattern is termed dysrhythmia, stemming from disruptions in cardiac...
 01:05
Pulse
Pulse Rate and its Significance
Pulse rate, often measured in beats per minute (bpm), reflects the heart rate (HR), which is influenced by numerous factors such as stress, physical activity, and hormonal changes. A normal resting adult pulse rate falls...
 01:30
Equipments Used To Measure Blood Pressure
This invasive approach involves cannulating a peripheral artery. During each cardiac contraction, pressure generates mechanical motion within the catheter, transmitted through rigid, fluid-filled tubing to a transducer. This transducer converts mechanical motion into electrical signals displayed as waveforms on a monitor. An automatic flushing system prevents blood backflow. Due to the potential risk of unexpected arterial blood loss, this method is primarily used in intensive...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:19
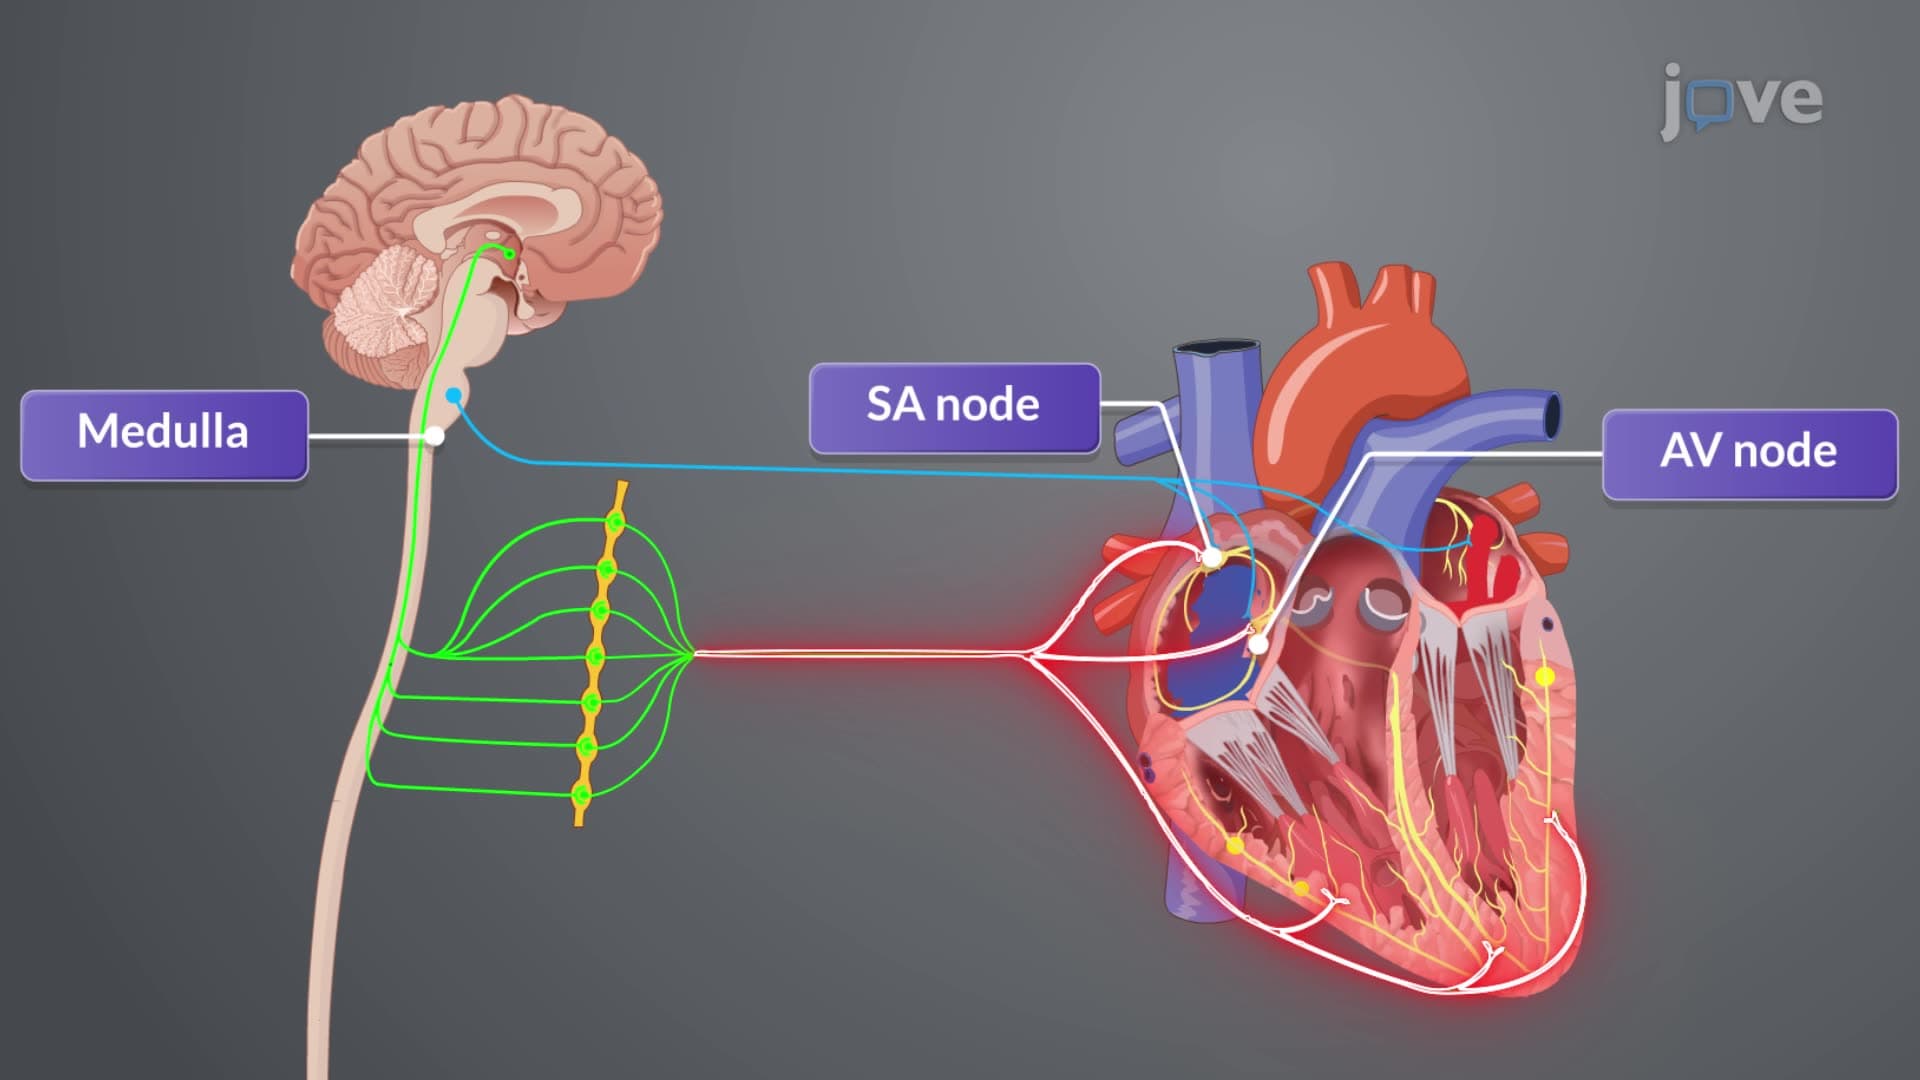
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac...