Related Experiment Video
Updated: Aug 1, 2025

Novel and Innovative Hybrid Technique for Type A Aortic Dissection
Published on: March 28, 2025
Physician-Modified Endovascular Graft for Left Subclavian Artery Fenestration during Thoracic Endovascular Aortic
Fei Mei1, Jianfeng Sun1, Kewei Wang1
1Department of Vascular Surgery, Yichang Central People's Hospital, The First College of Medical Science, China Three Gorges University, Hubei, China.

Insights
Physician-modified endovascular grafts for thoracic endovascular aortic repair safely preserve the left subclavian artery. This technique demonstrates high success rates and good mid-term outcomes for various aortic pathologies.
Area of Science:
- Vascular Surgery
- Interventional Cardiology
- Thoracic Surgery
Background:
- Thoracic endovascular aortic repair (TEVAR) is a common treatment for thoracic aortic pathologies.
- Preservation of the left subclavian artery (LSA) is crucial during TEVAR to prevent complications.
- Physician-modified endovascular grafts (PMEGs) offer a customizable solution for LSA revascularization.
Purpose of the Study:
- To evaluate the safety and efficacy of PMEG for LSA preservation during TEVAR.
- To assess perioperative outcomes and mid-term follow-up results.
- To determine the feasibility of PMEG in achieving adequate proximal landing zones for TEVAR.
Main Methods:
- A retrospective analysis of 66 patients who underwent TEVAR with PMEG for LSA fenestration from June 2019 to October 2022.
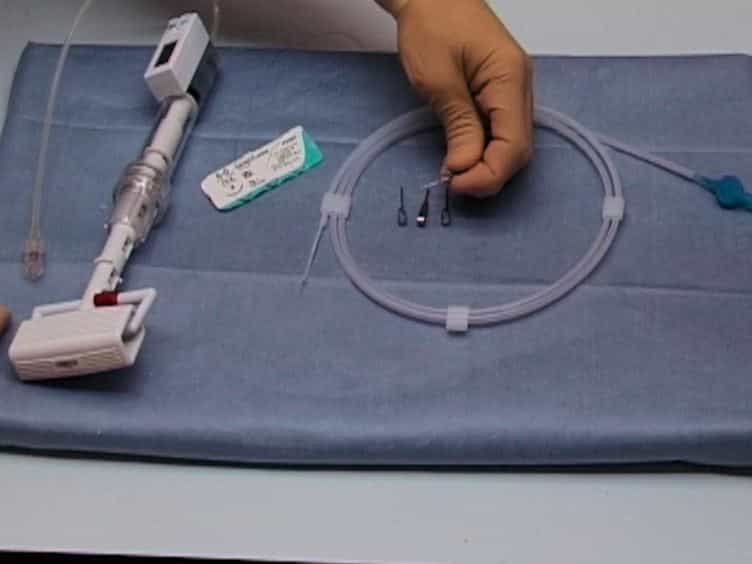
- Detailed description of surgical techniques for PMEG creation and implantation.
- Analysis of perioperative morbidity, mortality, and mid-term follow-up data.
Main Results:
- The technique success rate was 96.97% in 66 patients (80.30% with type B aortic dissection).
- 30-day perioperative morbidities included stroke (4.55%) and retrograde type A aortic dissection (1.52%).
- Mid-term follow-up (17 months) showed 100% primary patency of LSA fenestration stents, with low rates of late complications.
Conclusions:
- TEVAR with PMEG for LSA revascularization is a safe, feasible, and effective technique.
- The procedure is associated with a high success rate and favorable mid-term outcomes.
- Further investigation into long-term outcomes is warranted.
Background:
This study aimed to evaluate the safety and efficacy of physician-modified endovascular graft for preservation of left subclavian artery during thoracic endovascular aortic repair.
Methods:
From June 2019 to October 2022, 66 patients with a variety of thoracic aortic pathologies were treated with thoracic endovascular aortic repair using physician-modified endovascular graft left subclavian artery fenestration to achieve adequate proximal landing zone. The details of surgical techniques were described. The perioperative morbidity, mortality, and the outcomes of mid-term follow-up were analyzed.
Results:
Of the 66 patients (men: women, 53:13; age, 55.18 [55.18 ± 10.62] years), 53 (80.30%) presented with type B aortic dissection, 10 (15.15%) with thoracic penetrating aortic ulcer, 2 (3.03%) with thoracic aortic aneurysm, and 1 (1.52%) with left subclavian artery aneurysm. All of them underwent thoracic endovascular aortic repair using physician-modified endovascular graft left subclavian artery fenestration on the sterile back table. The technique success rate was 96.97% (n = 64). Total operation time was 92 min (interquartile range, 86-118), graft modification time was 19 min (interquartile range, 17-21), fluoroscopy time was 49 min (interquartile range, 41-62), and contrast agent dosage was 165 mL (interquartile range, 155-185). 30-day perioperative morbidities were 3 (4.55%) strokes, 1 (1.52%) retrograde type A aortic dissection, 1 (1.52%) aortic intimal intussusception, 1 (1.52%) left arm ischemia, and 3 (4.55%) type Ia endoleaks. Postoperative 30-day mortality and reintervention rates were 1.52% and 4.55%, respectively. Among the 63 patients included in the follow-up of 17 months (interquartile range, 7.75-18.25), the primary patency of left subclavian artery fenestration stents was 100%. Late complications were 1 (1.59%) distal stent graft-induced new entry and 1 (1.59%) death due to retrograde type A aortic dissection during the follow-up. The stent graft-induced new entry patient was observed with stable false lumen.
Conclusions:
Thoracic endovascular aortic repair with physician-modified endovascular graft for left subclavian artery revascularization is a safe, feasible, and efficacious technique associated with high success rate. Further study is needed for long-term outcome investigation.