Related Experiment Video
Updated: Jul 31, 2025
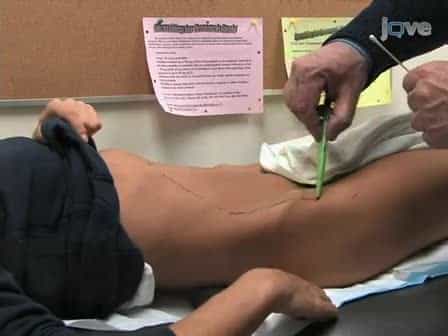

Demonstration of Cutaneous Allodynia in Association with Chronic Pelvic Pain
Published on: June 23, 2009
Levator Ani Syndrome Presenting with Vaginal Pain
Louise Dunphy1, Frances Wood2, Emad Saleem Mubarak3
1Department of Gynaecology, Leighton Hospital, Crewe, UK Louise.Dunphy@doctors.org.uk.

Abstract:
Levator ani syndrome (LAS), also known as levator ani spasm, puborectalis syndrome, chronic proctalgia, pyriformis syndrome and pelvic tension myalgia, produces chronic anal pain. The levator ani muscle is susceptible to the development of myofascial pain syndrome, and trigger points may be elicited on physical examination. The pathophysiology remains to be fully delineated. The diagnosis of LAS is suggested primarily by the clinical history, physical examination and the exclusion of organic disease that can produce recurrent or chronic proctalgia. Digital massage, sitz bath, electrogalvanic stimulation and biofeedback are the treatment modalities most frequently described in the literature. Pharmacological management includes non-steroidal anti-inflammatory medications, diazepam, amitriptyline, gabapentin and botulinum toxin. The evaluation of these patients can be challenging due to a diversity of causative factors. The authors present the case of a nulliparous woman in her mid-30s presenting with acute onset of lower abdominal and rectal pain radiating to her vagina. There was no history of trauma, inflammatory bowel disease, anal fissure or altered bowel habit. Each pain episode lasted longer than 20 min and was exacerbated by sitting. Neurological examination showed no evidence of neurological dysfunction. Rectal examination was unremarkable. During vaginal examination, palpation of the levator ani muscles elicited pain indicating pelvic floor dysfunction. Laboratory investigations including a full blood count and C reactive protein were within normal range. Further investigation with a transabdominal ultrasound scan, CT of the abdomen and pelvis and MRI of the lumbar spine were unremarkable. She commenced treatment with amitriptyline 20 mg once daily. She was referred for pelvic floor physiotherapy. Functional pain syndromes, such as LAS, should be regarded as diagnoses of exclusion and considered only after a thorough evaluation has been performed to rule out structural causes of pain. Knowledge of the pelvic floor and pelvic wall muscles may enable the physician to identify LAS, a possible cause of chronic pelvic pain.
More Related Videos

Related Concept Videos
 01:17
Drugs for Treatment of Diarrhea-Predominant IBS
Two specific drugs used in the treatment are alosetron (Lotronex) and eluxadoline (Viberzi). Alosetron, a 5-HT3 antagonist, works by slowing the movement of stools in the gut, reducing bowel...
 01:26
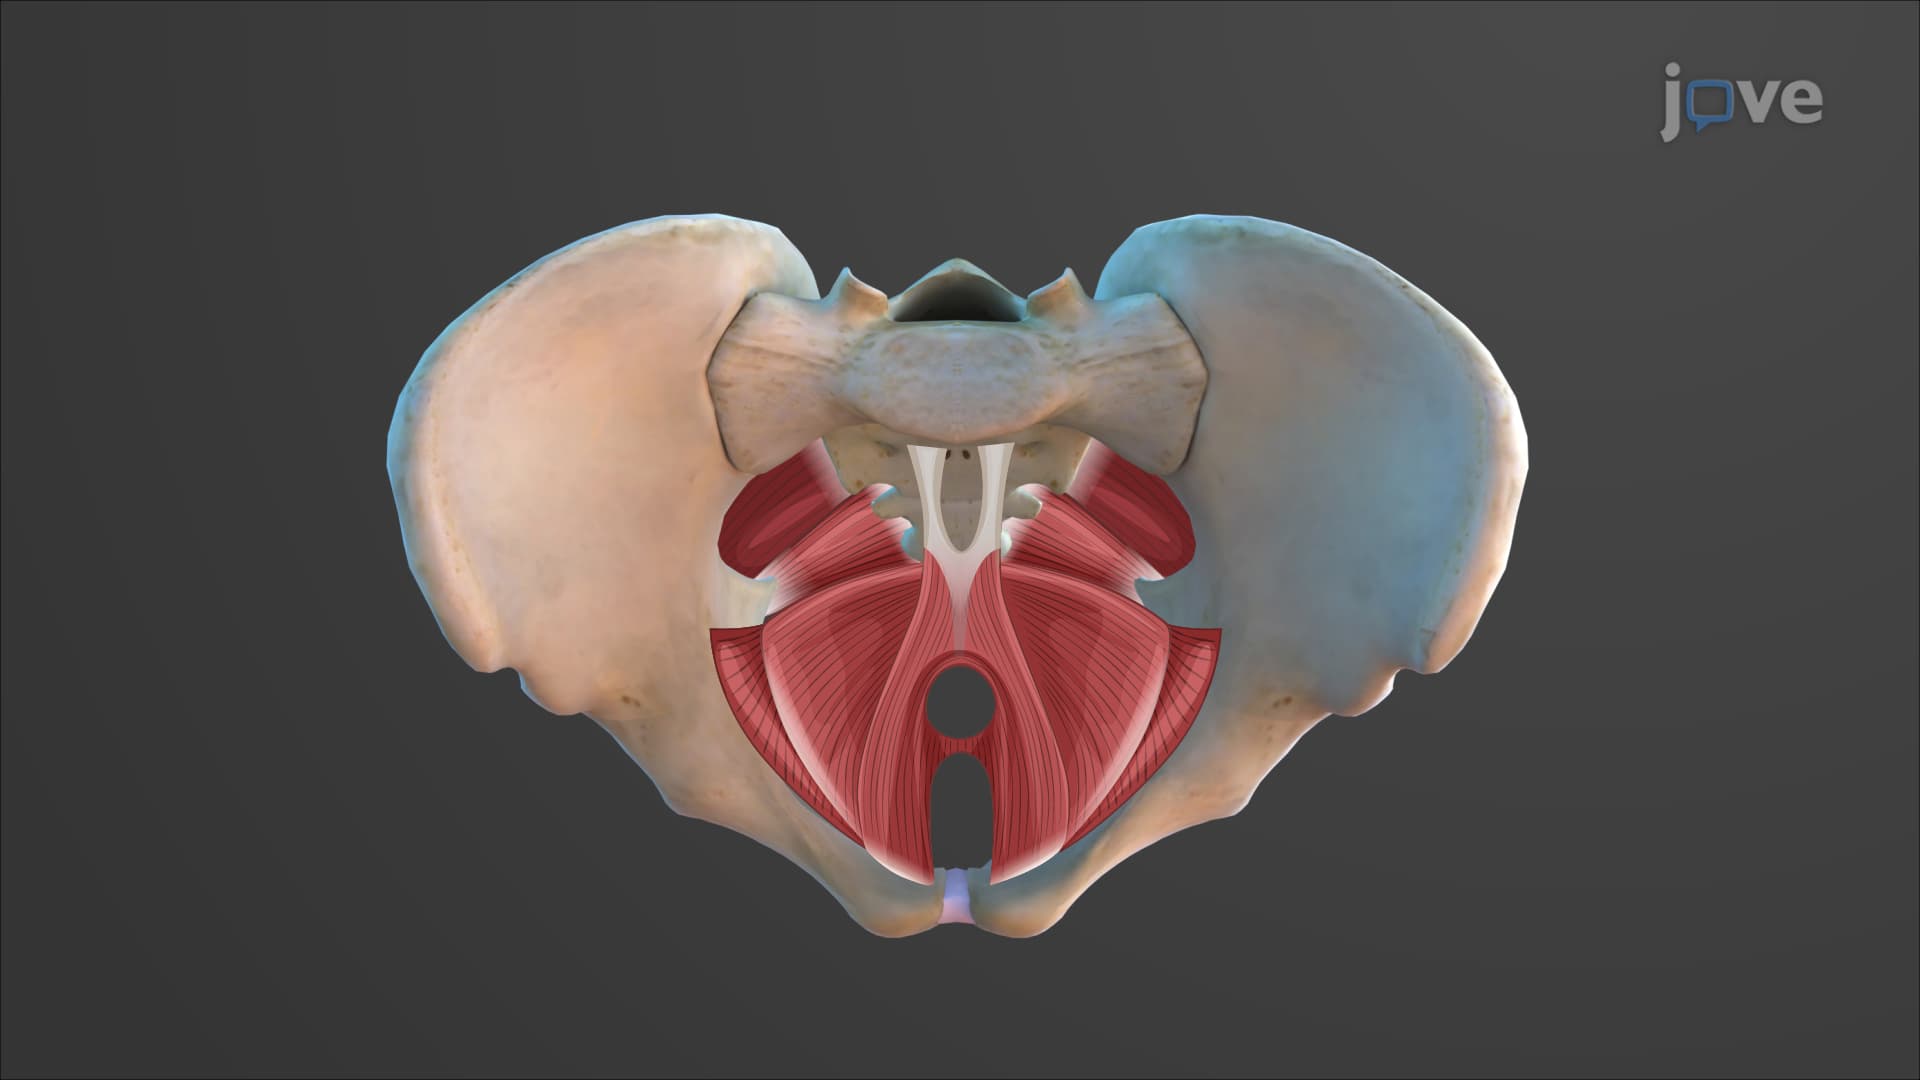
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:26
Vagina
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:25
Urinary Tract Calculi VI: Surgical Management