Related Experiment Video
Updated: Jul 31, 2025
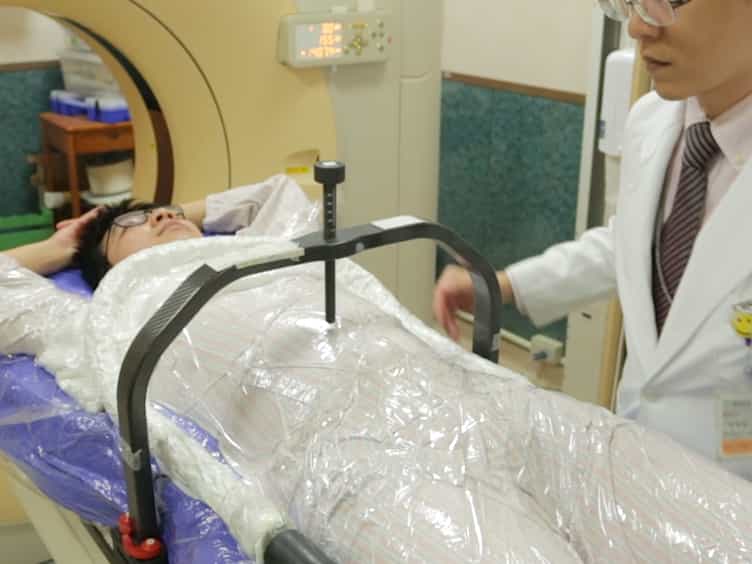

Treatment of Liver Metastases Using an Internal Target Volume Method for Stereotactic Body Radiotherapy
Published on: May 8, 2018
Caution against simultaneous integrated boost radiotherapy for upper thoracic esophageal squamous cell carcinoma:
Yue Zhou1,2,3,4, Li Chu1,2,3,4, Saiquan Lu1,2,3,4
1Department of Radiation Oncology, Fudan University Shanghai Cancer Center, 270 Dongan Road, Shanghai, 200032, China.

Purpose:
To explore the feasibility and safety of simultaneous integrated boost technology (SIB) with elective nodal irradiation (ENI) to the cervical and upper mediastinal lymph node (LN) regions in upper thoracic esophageal squamous cell carcinoma (ESCC).
Material And Methods:
Patients with pathologically proven unresectable upper thoracic ESCC were assigned 50.4 Gy/28 fractions (F) to the clinical target volume (encompassing the ENI area of cervical and upper mediastinal LN regions) and a boost of 63 Gy/28 F to the gross tumor volume. Chemotherapy consisted of courses of concurrent cisplatin (20 mg/m2) and docetaxel (20 mg/m2) weekly for 6 weeks. The primary endpoint was toxicity.
Results:
Between Jan 2017 and Dec 2019, 28 patients were included. The median follow-up time for all patients was 24.6 months (range 1.9-53.5). Radiation-related acute toxicity included esophagitis, pneumonia and radiodermatitis, all of which were well managed and reversed. Late morbidity included esophageal ulcer, stenosis, fistula and pulmonary fibrosis. Grade III esophageal stenosis and fistula was seen in 11% (3/28) and 14% (4/28) patients, respectively. The cumulative incidence rate of late esophageal toxicity was 7.7%, 19.2% and 24.6% at 6, 12 and 18 months, respectively. There was significant difference of the occurrence of severe late esophageal toxicity among the different volume levels of the esophagus, and cervical and upper mediastinal LNs which received ≥ 63 Gy stratified by the tertiles (p = 0.014).
Conclusions:
Despite the acceptably tolerated acute toxicity of SIB in concurrent CRT with ENI to the cervical and upper mediastinal LN regions for upper thoracic ESCC, the incidence of severe late esophageal toxicity was relatively high. Cautions are provided against easy clinical application of SIB (50.4 Gy/28F to the CTV, 63 Gy/28F to the GTV) in upper thoracic ESCC. Further exploration on dose optimization is warranted.
More Related Videos
 04:04
Endobronchial Ultrasound-guided Intratumoral Injection of Cisplatin for the Treatment of Isolated Mediastinal Recurrence of Lung Cancer
Published on: February 12, 2017
 08:34
Proton Therapy Delivery and Its Clinical Application in Select Solid Tumor Malignancies
Published on: February 6, 2019
Related Concept Videos
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 02:56
Treatment Resistant Cancers