Related Experiment Video
Updated: Jul 31, 2025
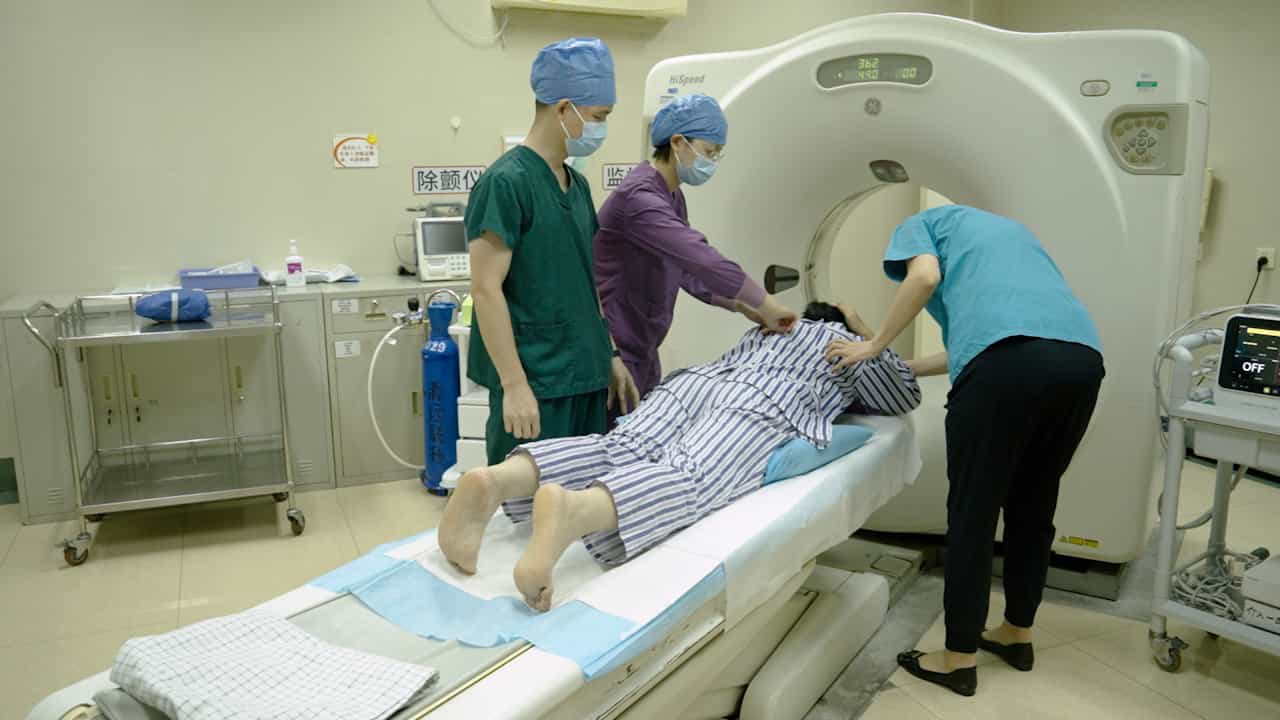

Improved Home Blood Pressure Control by CT-guided Ozone-mediated Renal Denervation for Patients with Resistant Hypertension
Published on: June 6, 2025
The optimal gestational age to deliver patients with chronic hypertension on antihypertensive therapy
Sumithra Jeganathan1, Matthew J Blitz2, Amanda K Makol3
1Department of Obstetrics and Gynecology, North Shore University Hospital-Northwell Health, Manhasset, NY, USA.

Objective:
To identify the optimal gestational age of planned delivery in pregnancies complicated by chronic hypertension requiring antihypertensive medications that minimizes the risk of adverse perinatal events and maternal morbidity.
Methods:
Retrospective cohort study of singleton pregnancies after 37 weeks of gestation complicated by chronic hypertension on antihypertensive medication, delivered at 7 hospitals within an academic health system in New York from 12/1/2015 to 9/3/2020. Two comparisons were made (1) planned deliveries at 37-376/7 weeks versus expectant management, (2) planned deliveries at 38-386/7 weeks versus expectant management. Patients with other maternal or fetal conditions were excluded. The primary outcome was a composite of adverse perinatal outcomes including stillbirth, neonatal death, assisted ventilation, cord pH < 7.0, 5-minute Apgar ≤5, diagnosis of respiratory disorder, and neonatal seizures. The secondary outcomes included preeclampsia, eclampsia, primary cesarean delivery, postpartum readmission, and infant stay greater than 5 days. Odds ratios were estimated with multiple logistic regression and adjusted for confounding effects.
Results:
A total of 555 patients met inclusion criteria. Patients who underwent planned delivery at 37 weeks compared to expectant management did not appear to be at higher risk of adverse perinatal outcomes (14.9% vs 10.4%, aOR 1.49, 95% CI: 0.77-2.88). Similarly, we did not find a difference in the primary outcome in patients who underwent planned delivery at 38 weeks versus those expectantly managed (9.7% vs 10.1%, (aOR 0.84, 95% CI: 0.39-1.76). There were no differences in the rates of primary cesarean or preeclampsia at 37 and 38 weeks.
Conclusion:
Our findings suggest that there is no difference in neonatal or maternal outcomes for chronic hypertensive patients on medication if delivery is planned or expectantly managed at 37 or 38 weeks' gestation.

Related Concept Videos
 01:23
Hypertension V: Nursing Management
 01:28
Hypertension I: Introduction
 01:28
Hypertension IV: Drug Therapy and Lifestyle Modifications
 01:18
Hypertension and Regulation of Blood Pressure
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:30
Hypertension III: Clinical Manifestations and Diagnostic Studies