Related Experiment Video
Updated: Jul 31, 2025
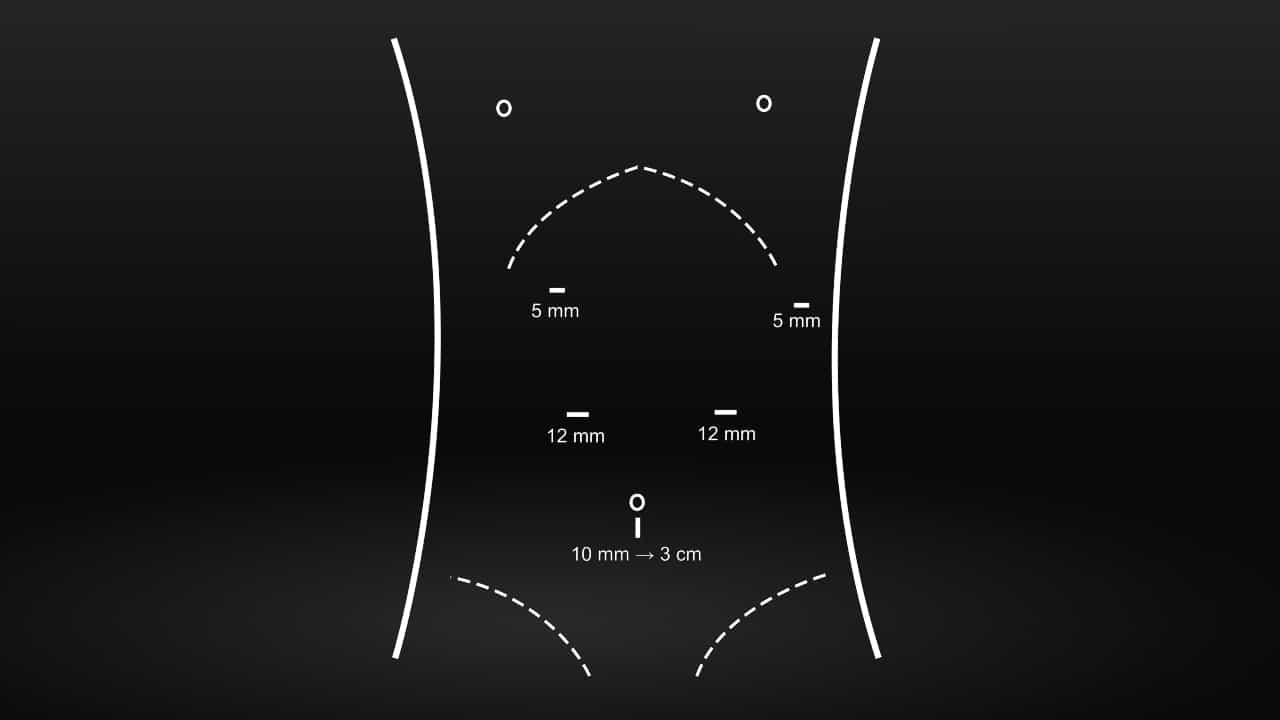
Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Diagnosis and Management of Cirrhosis and Its Complications: A Review
Elliot B Tapper1, Neehar D Parikh1
1Division of Gastroenterology and Hepatology, University of Michigan, Ann Arbor.

Importance:
Cirrhosis affects approximately 2.2 million adults in the US. From 2010 to 2021, the annual age-adjusted mortality of cirrhosis increased from 14.9 per 100 000 to 21.9 per 100 000 people.
Observations:
The most common causes of cirrhosis in the US, which can overlap, include alcohol use disorder (approximately 45% of all cases of cirrhosis), nonalcoholic fatty liver disease (26%), and hepatitis C (41%). Patients with cirrhosis experience symptoms including muscle cramps (approximately 64% prevalence), pruritus (39%), poor-quality sleep (63%), and sexual dysfunction (53%). Cirrhosis can be diagnosed by liver biopsy but may also be diagnosed noninvasively. Elastography, a noninvasive assessment of liver stiffness measured in kilopascals, can typically confirm cirrhosis at levels of 15 kPa or greater. Approximately 40% of people with cirrhosis are diagnosed when they present with complications such as hepatic encephalopathy or ascites. The median survival time following onset of hepatic encephalopathy and ascites is 0.92 and 1.1 years, respectively. Among people with ascites, the annual incidence of spontaneous bacterial peritonitis is 11% and of hepatorenal syndrome is 8%; the latter is associated with a median survival of less than 2 weeks. Approximately 1% to 4% of patients with cirrhosis develop hepatocellular carcinoma each year, which is associated with a 5-year survival of approximately 20%. In a 3-year randomized clinical trial of 201 patients with portal hypertension, nonselective β-blockers (carvedilol or propranolol) reduced the risk of decompensation or death compared with placebo (16% vs 27%). Compared with sequential initiation, combination aldosterone antagonist and loop diuretics were more likely to resolve ascites (76% vs 56%) with lower rates of hyperkalemia (4% vs 18%). In meta-analyses of randomized trials, lactulose was associated with reduced mortality relative to placebo (8.5% vs 14%) in randomized trials involving 705 patients and reduced risk of recurrent overt hepatic encephalopathy (25.5% vs 46.8%) in randomized trials involving 1415 patients. In a randomized clinical trial of 300 patients, terlipressin improved the rate of reversal of hepatorenal syndrome from 39% to 18%. Trials addressing symptoms of cirrhosis have demonstrated efficacy for hydroxyzine in improving sleep dysfunction, pickle brine and taurine for reducing muscle cramps, and tadalafil for improving sexual dysfunction in men.
Conclusions And Relevance:
Approximately 2.2 million US adults have cirrhosis. Many symptoms, such as muscle cramps, poor-quality sleep, pruritus, and sexual dysfunction, are common and treatable. First-line therapies include carvedilol or propranolol to prevent variceal bleeding, lactulose for hepatic encephalopathy, combination aldosterone antagonists and loop diuretics for ascites, and terlipressin for hepatorenal syndrome.

Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:26
Diseases of the Liver and Gallbladder
Cirrhosis is characterized by the scarring of hepatic lobules in the liver, which are replaced by fibrous tissue, affecting the liver's normal functioning. NAFLD, on the other hand, is caused by an excessive build-up of fat in the liver, not...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:24
Esophageal Varices-I: Introduction
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...