Related Experiment Video
Updated: Jul 31, 2025
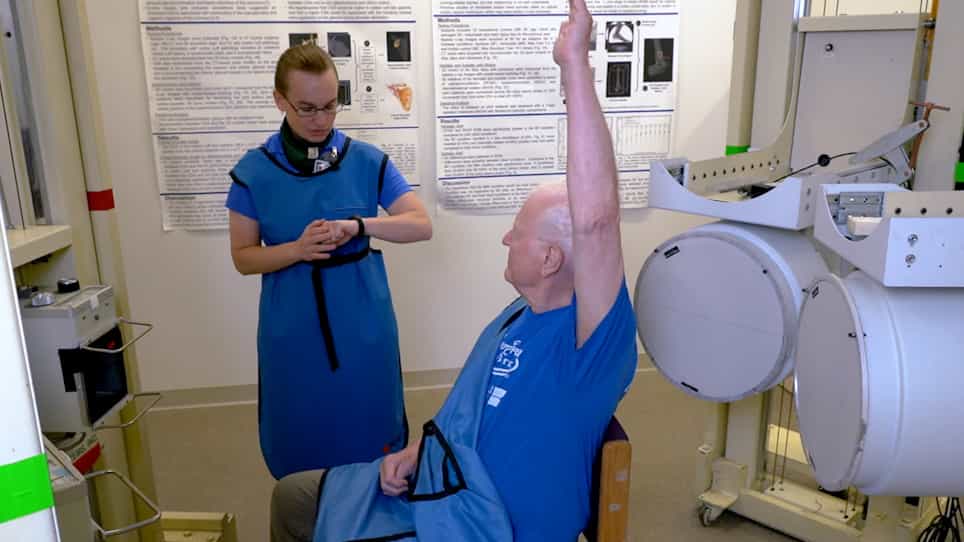

Measuring 3D In-vivo Shoulder Kinematics using Biplanar Videoradiography
Published on: March 12, 2021
The deformities of acute diaphyseal clavicular fractures: a three-dimensional analysis
Yi-Hsuan Chao1,2,3, Ying-Chao Chou4, Chun-Li Lin5,6
1Department of Biomedical Engineering, National Yang Ming Chiao Tung University, No. 155, Sec. 2, Linong Street, Taipei, 112, Taiwan.

Background:
Although minimally invasive surgeries have gained popularity in many orthopaedic fields, minimally invasive approaches for diaphyseal clavicular fracture have not been widely performed, which is attributed to difficulties in performing a closed reduction of fracture deformities of a curved bone in a three-dimensional space. The goal of this study was to investigate the radiographic parameters of fracture deformities in a three-dimensional space and to identify the risk factors for deformities.
Methods:
The computed tomography images of 100 patients who sustained a clavicle fracture were included. Five parameters were used to analyze the deformities: change in clavicle length, fracture displacement, and fragment rotation around the X, Y, Z axes. The change in length was assessed using the length of the endpoint line. The displacement was assessed using the distance between the fracture midpoints. The rotation deformities were assessed using the Euler angles. The correlation between the parameters was evaluated with the Pearson correlation coefficient. The risk factors were evaluated using univariable analysis and multiple regression analysis.
Results:
The average change in length was - 5.3 ± 8.3 mm. The displacement was 11.8 ± 7.1 mm. The Euler angles in the Z-Y-X sequences were -1 ± 8, 1 ± 8, and - 8 ± 13 degrees. The correlation coefficient between the change in length and the displacement was - 0.724 (p < 0.001). The variables found to increase the risk of shortening and displacement were right-sided fracture (p = 0.037), male sex (p = 0.015), and multifragmentary type (p = 0.020). The variables found to increase the risk of rotation deformity were the number of rib fractures (p = 0.001) and scapula fracture (p = 0.025).
Conclusions:
There was a strong correlation between shortening and displacement. The magnitude of anterorotation around the X axis was greater than the magnitude of retraction around the Z axis and depression around the Y axis. The risk factors for shortening and displacement included right-sided fracture, male sex, and multifragmentary type. The risk factor for retraction around the Z axis was the number of rib fractures, and the risk factor for depression around the Y axis was scapula fracture. These results could be useful adjuncts in guiding minimally invasive surgical planning for diaphyseal clavicular fractures.

Related Concept Videos
 01:29
Three-Dimensional Analysis of Strain
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:19
Bones of the Upper Limb: Humerus
 01:09
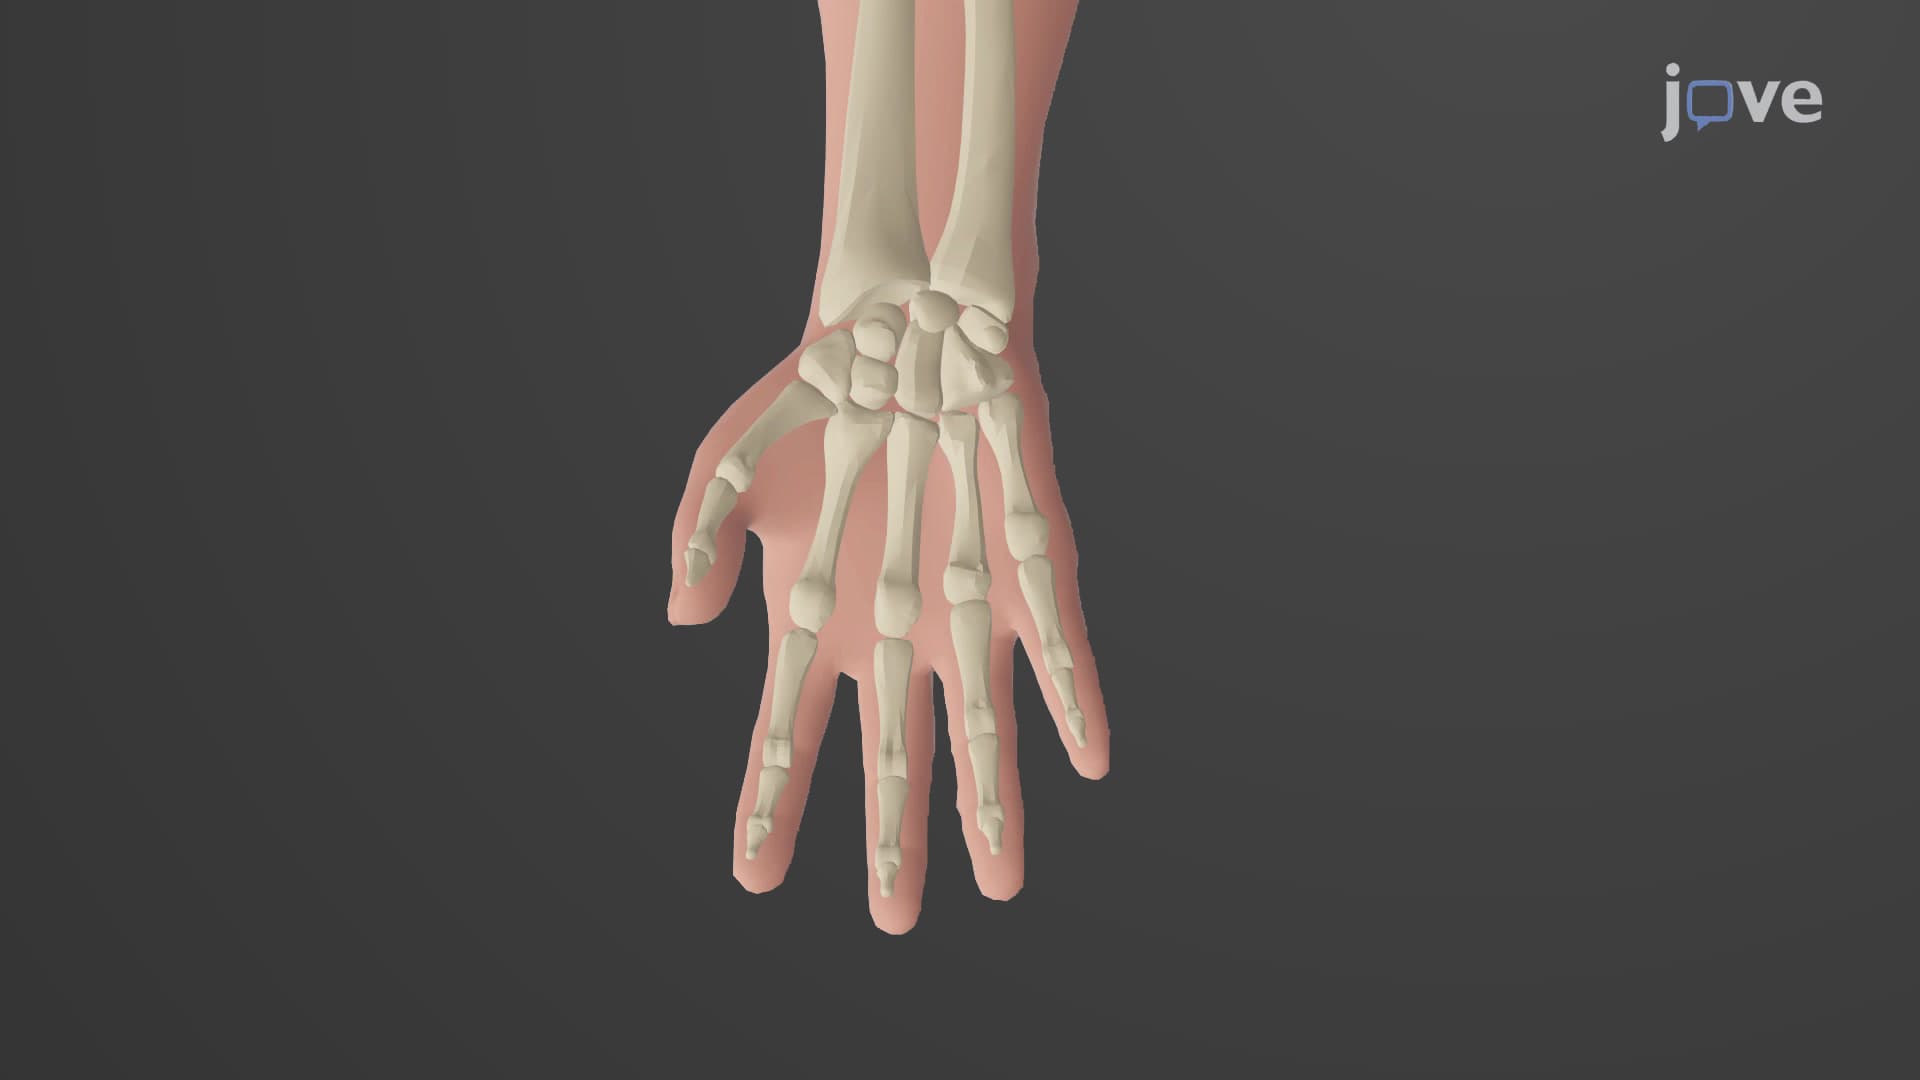
Bones of the Upper Limb: Radius
The radius has a nail-shaped head, and a...
 01:10
Deformation in a Circular Shaft
 01:09
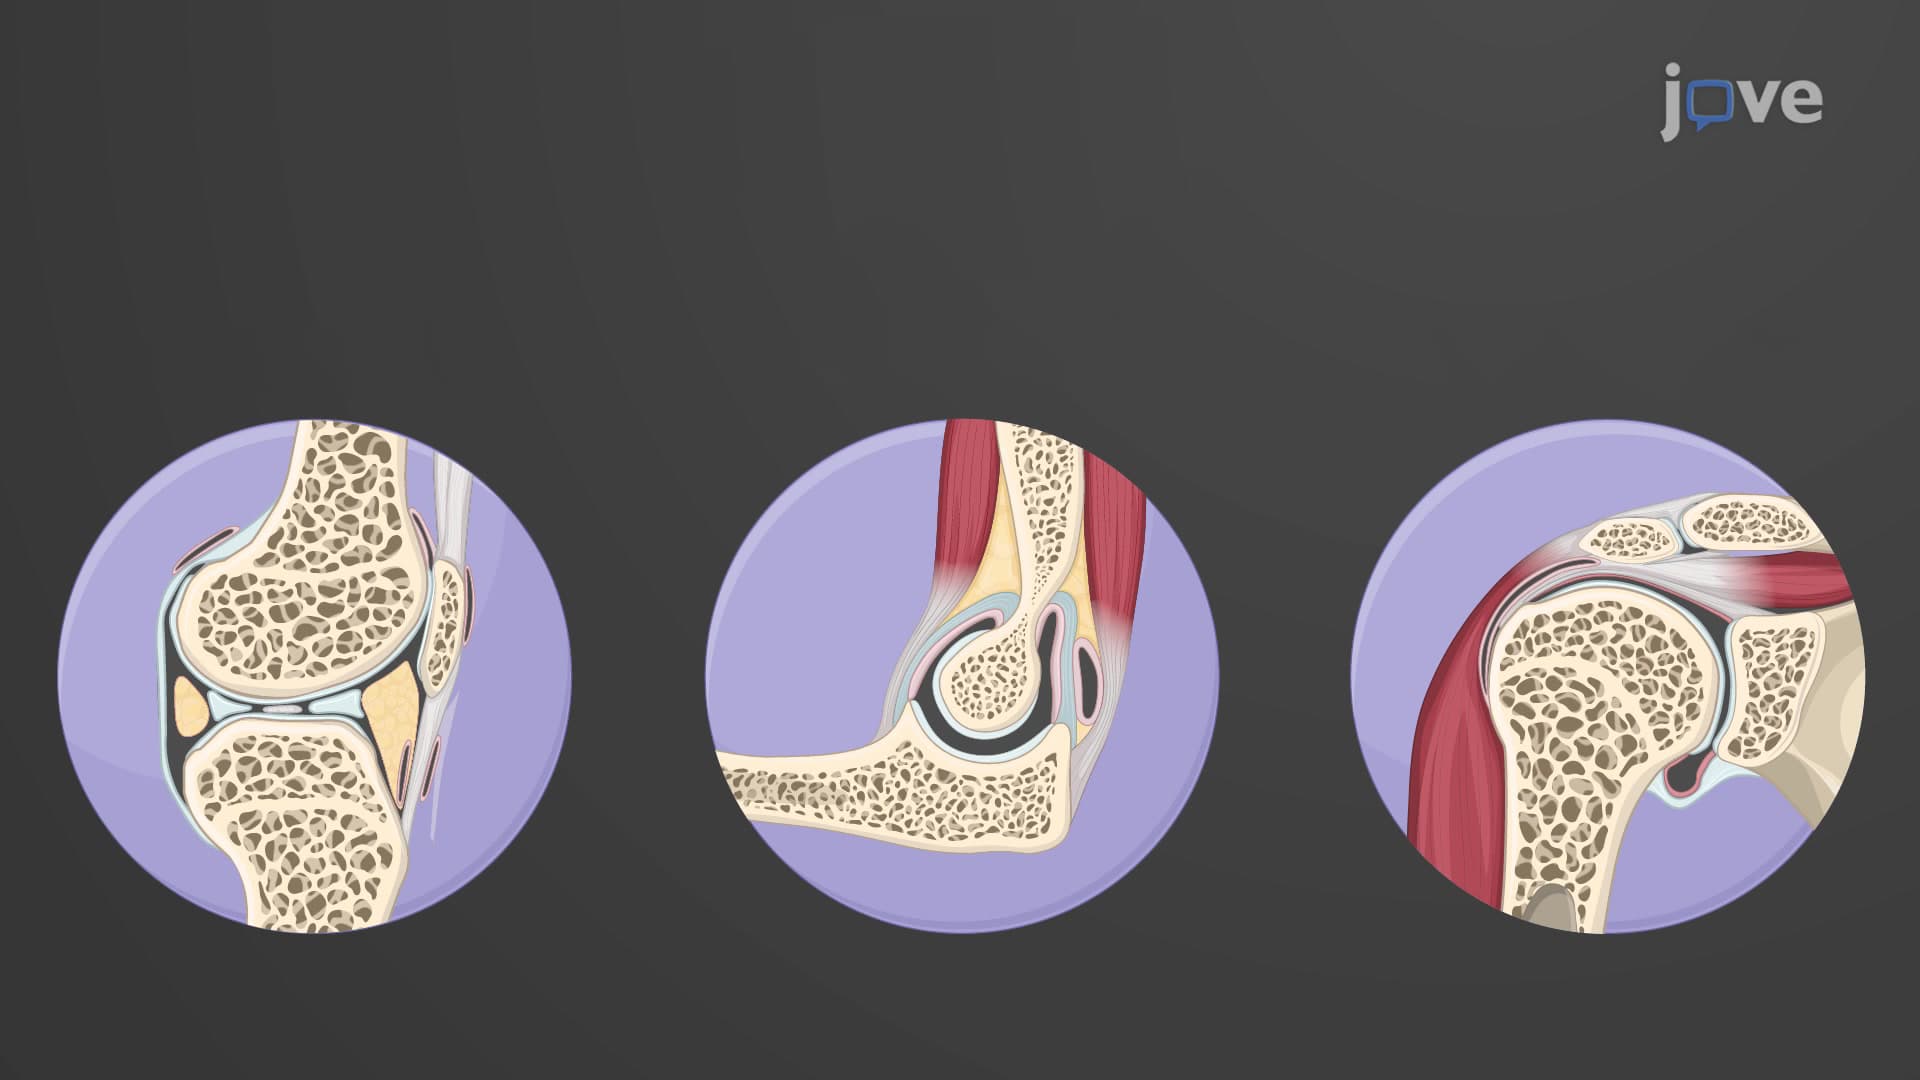
Functional Classification of Joints
The functional classification of joints is determined by the amount of mobility between the adjacent bones. Joints are functionally classified as a synarthrosis or immobile joint, an amphiarthrosis or slightly moveable joint, or as a diarthrosis, a freely moveable joint. Fibrous and cartilaginous joints can be functionally classified as either synarthroses or amphiarthroses, whereas all synovial joints are classified as diarthroses.
Synarthrosis
An...