Related Experiment Video
Updated: Jul 30, 2025
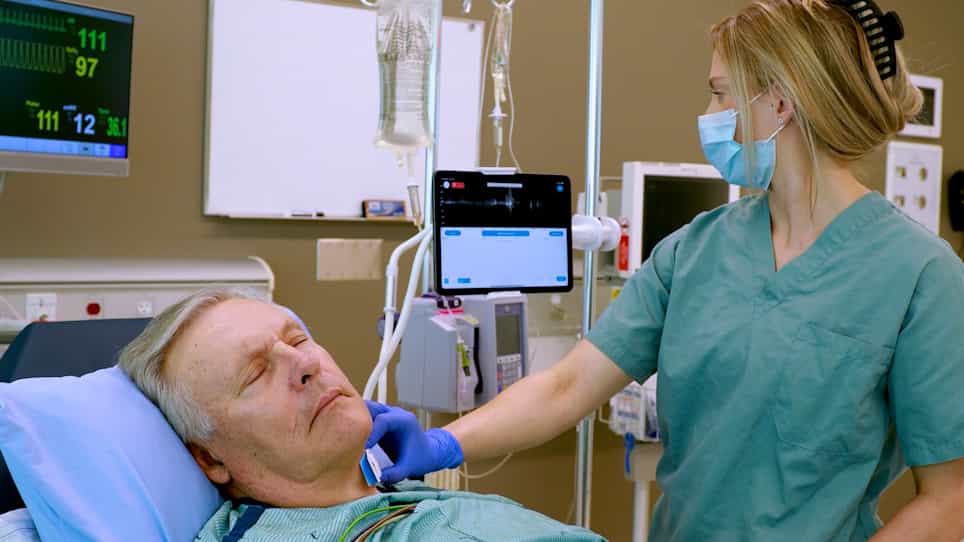

Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
RESPIRATORY VARIABILITY OF VALVULAR PEAK SYSTOLIC VELOCITY AS A NEW INDICATOR OF FLUID RESPONSIVENESS IN PATIENTS
Qiang Ma1, Caiyun Ding2, Feng Jiang1
1Department of Ultrasound, The First Affiliated Hospital of Wannan Medical College, Wuhu, Anhui, China.

Abstract:
Objective: The aim of this study was to evaluate the reliability and feasibility of pulse Doppler measurements of peak velocity respiratory variability of mitral and tricuspid valve rings during systole as new dynamic indicators of fluid responsiveness in patients with septic shock. Methods: Transthoracic echocardiography (TTE) was performed to measure the respiratory variability of aortic velocity-time integral (∆VTI), respiratory variability of tricuspid annulus systolic peak velocity (∆RVS), respiratory variability of mitral annulus systolic peak velocity (∆LVS), and other related indicators. Fluid responsiveness was defined as a 10% increase in cardiac output after fluid expansion, assessed by TTE. Results: A total of 33 patients with septic shock were enrolled in this study. First, there was no significant difference in the population characteristics between the fluid responsiveness positive group (n = 17) and the fluid responsiveness negative group (n = 16) ( P > 0.05). Second, Pearson correlation test showed that ∆RVS, ∆LVS, and TAPSE with the relative increase in cardiac output after fluid expansion ( R = 0.55, P = 0.001; R = 0.40, P = 0.02; R = 0.36, P = 0.041). Third, multiple logistic regression analysis demonstrated that ∆RVS, ∆LVS, and TAPSE were significantly correlated with fluid responsiveness in patients with septic shock. Fourth, receiver operating characteristic (ROC) curve analysis revealed that ∆VTI, ∆LVS, ∆RVS, and TAPSE had good predictive ability for fluid responsiveness in patients with septic shock. The area under the curve (AUC) of ∆VTI, ∆LVS, ∆RVS, and TAPSE for predicting fluid responsiveness was 0.952, 0.802, 0.822, and 0.713, respectively. The sensitivity (Se) values were 1.00, 0.73, 0.81, and 0.83, whereas the specificity (Sp) values were 0.84, 0.91, 0.76, and 0.67, respectively. The optimal thresholds were 0.128, 0.129, 0.130, and 13.9 mm, respectively. Conclusion: Tissue Doppler ultrasound evaluation of respiratory variability of mitral and tricuspid annular peak systolic velocity could be a feasible and reliable method for the simple assessment of fluid responsiveness in patients with septic shock.

Related Concept Videos
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:17
Measurement of Blood Pressure