Related Experiment Video
Updated: Jul 30, 2025


Anogenital Distance and Perineal Measurements of the Pelvic Organ Prolapse POP Quantification System
Published on: September 20, 2018
Risk factors associated with severe perineal lacerations during vaginal delivery: a 10-year propensity score-matched
Valentina Laurita Longo1,2,3, Emmanuel N Odjidja3, Bruno A Zanfini1
1Department of Women and Child Health, Women Health Area, Fondazione Policlinico Universitario Agostino Gemelli, IRCCS, Rome, Italy (Drs Laurita Longo, Zanfini, Catarci, Carducci, Draisci, Lanzone, and Bevilacqua).

Background:
Severe perineal lacerations are rare obstetrical complications in high-income countries. However, the prevention of obstetric anal sphincter injuries is crucial because of their long-term consequences on a woman's digestive function, sexual-mental health, and well-being. The probability of obstetric anal sphincter injuries can be predicted by assessing antenatal and intrapartum risk factors.
Objective:
This study aimed to assess the incidence of obstetric anal sphincter injuries at a single institution for 10 years and to identify women more at risk by evaluating the relationship between antenatal and intrapartum risk factors and severe perineal tears. The main outcome measured in this study was the occurrence of obstetric anal sphincter injuries during vaginal delivery.
Study Design:
This was an observational retrospective cohort study conducted at a University Teaching Hospital in Italy. The study was conducted from 2009 to 2019 using a prospectively maintained database. The study cohort included all women with singleton pregnancy at term who delivered via vaginal delivery in cephalic presentation. Of note, data analysis was performed in 2 stages: a propensity score matching to balance possible differences between patients with obstetric anal sphincter injuries and those without and a stepwise univariate and multivariate logistic regression. A secondary analysis was performed to further evaluate the effect of parity, epidural anesthesia, and duration of the second stage of labor by adjusting for potential confounders.
Results:
Of 41,440 patients screened for eligibility, 22,156 met the inclusion criteria, and 15,992 were balanced after propensity score matching. Obstetric anal sphincter injuries occurred in 81 cases (0.4%), 67 (0.3%) after spontaneous delivery and 14 (0.8%) after vacuum delivery(P=.002). There was an increased odds of severe lacerations of nearly 2-fold for nulliparous women delivering by vacuum delivery (adjusted odds ratio, 2.85; 95% confidence interval, 1.19-6.81; P=.019), with a reciprocal reduction in women with spontaneous vaginal delivery (adjusted odds ratio, 0.35; 95% confidence interval, 0.15-0.84; P=.019) and at least 1 previous delivery (adjusted odds ratio, 0.51; 95% confidence interval, 0.31-0.85; P=.005). Epidural anesthesia was associated with a lower incidence of obstetric anal sphincter injuries (adjusted odds ratio, 0.54; 95% confidence interval, 0.33-0.86; P=.011). The risk of severe lacerations was independent of the duration of the second stage of labor (adjusted odds ratio, 1.00; 95% confidence interval, 0.99-1.00; P=.3), whereas the risk was reduced when mediolateral episiotomy was performed (adjusted odds ratio, 0.20; 95% confidence interval, 0.11-0.36; P<.001). Neonatal risk factors include head circumference (odds ratio, 1.50; 95% confidence interval, 1.18-1.90; P=.001) and vertex malpresentation (adjusted odds ratio, 2.71; 95% confidence interval, 1.08-6.78; P=.033). Induction of labor (adjusted odds ratio, 1.13; 95% confidence interval, 0.72-1.92; P=.6), frequent obstetrical examinations (adjusted odds ratio, 1.17; 95% confidence interval, 0.72-1.90), and women's supine position at birth (adjusted odds ratio, 1.25; 95% confidence interval, 0.61-2.55; P=.5) were further evaluated. Among severe obstetrical complications, shoulder dystocia increased the risk of obstetric anal sphincter injuries by nearly 4 times (adjusted odds ratio, 3.92; 95% confidence interval, 0.50-30.74; P=.2), whereas postpartum hemorrhage occurred 3 times more often in cases of delivery complicated by severe lacerations (adjusted odds ratio, 3.35; 95% confidence interval, 1.76-6.40; P<.001). The relationship among obstetric anal sphincter injuries, parity, and the use of epidural anesthesia was further confirmed in a secondary analysis. We found that primiparas who delivered without epidural anesthesia had the highest risk of obstetric anal sphincter injuries (adjusted odds ratio, 2.53; 95% confidence interval, 1.46-4.39; P=.001).
Conclusion:
Severe perineal lacerations were found to be a rare complication of vaginal delivery. By using a robust statistical model, such as propensity score matching, we were able to investigate a broad range of antenatal and intrapartum risk factors, including use of epidural anesthesia, number of obstetrics examinations, and patient position at birth, which are usually underreported. Moreover, we found that women who delivered for the first time without epidural anesthesia had the highest risk of obstetric anal sphincter injuries.


Related Concept Videos
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:26
Varicose Veins I: Introduction
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin...
 01:26
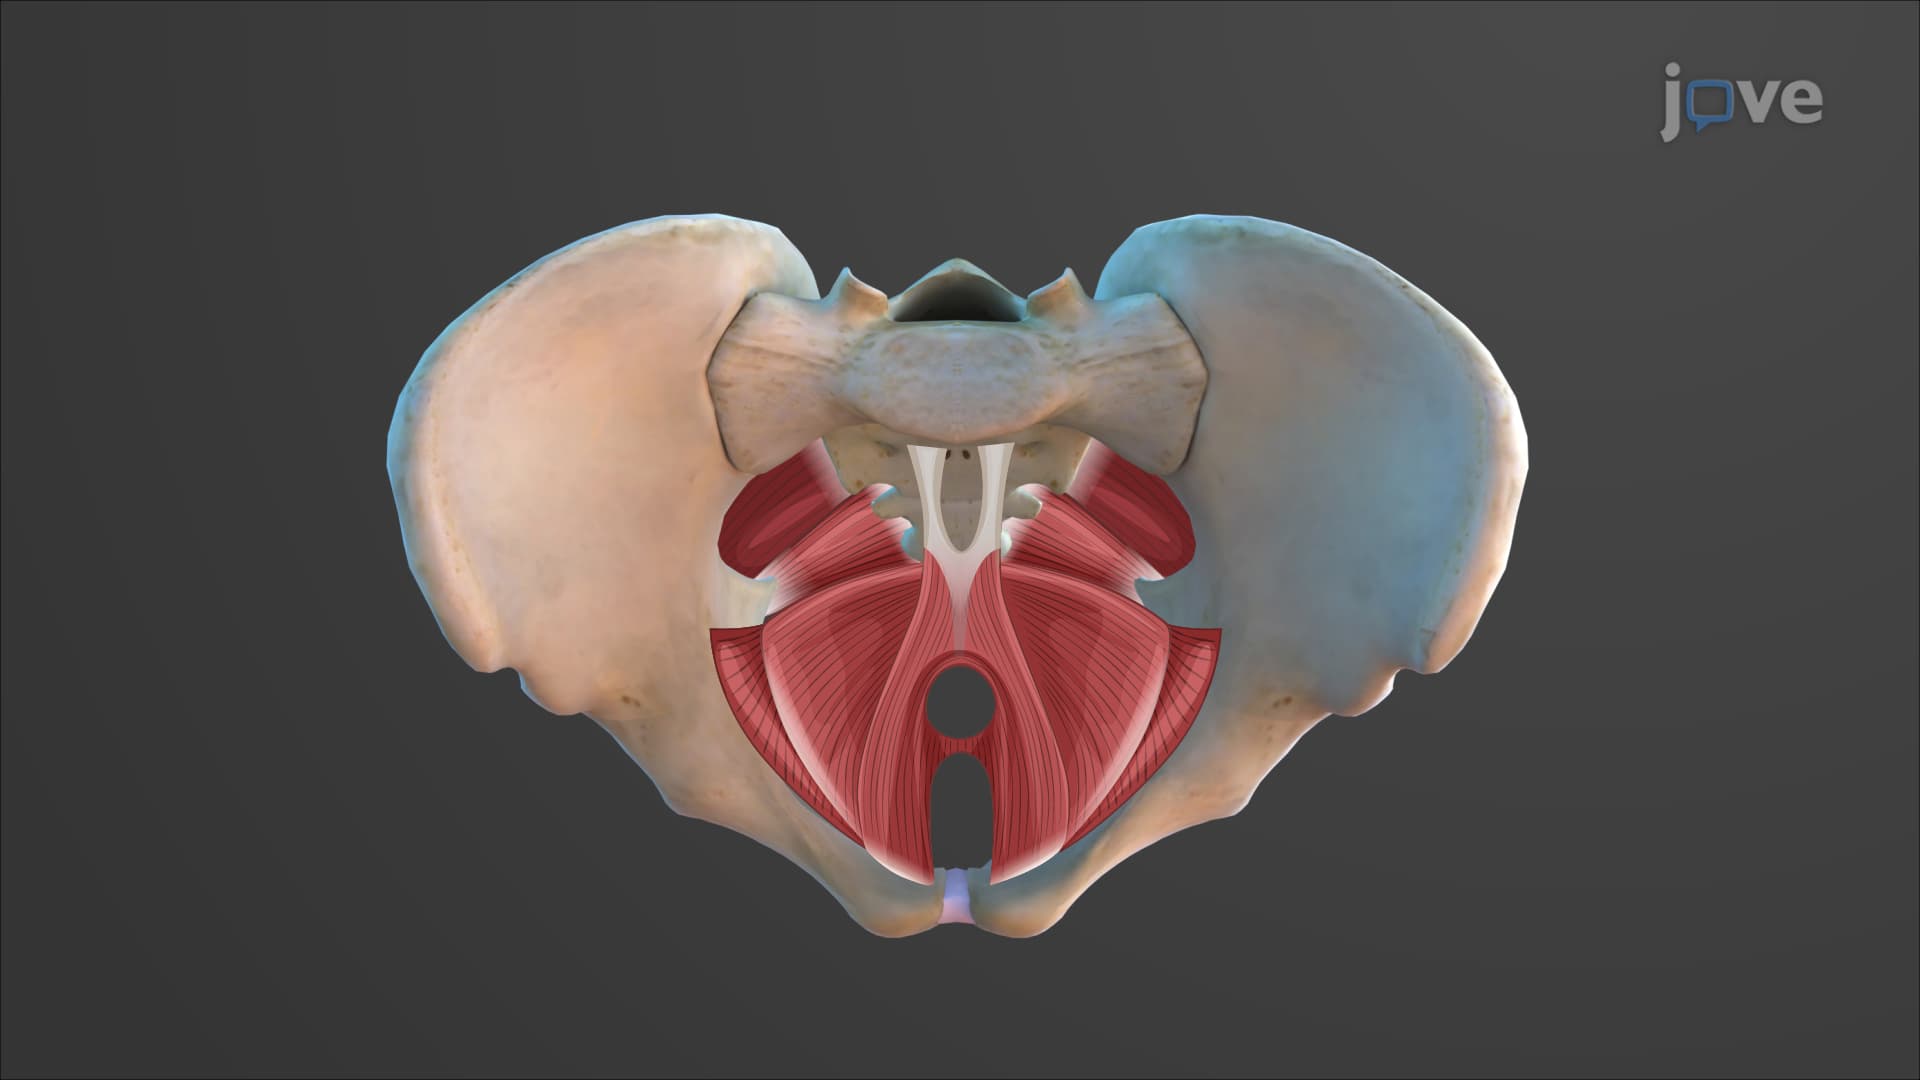
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:22
Aneurysm IV: Nursing Management