Related Experiment Video
Updated: Jul 30, 2025
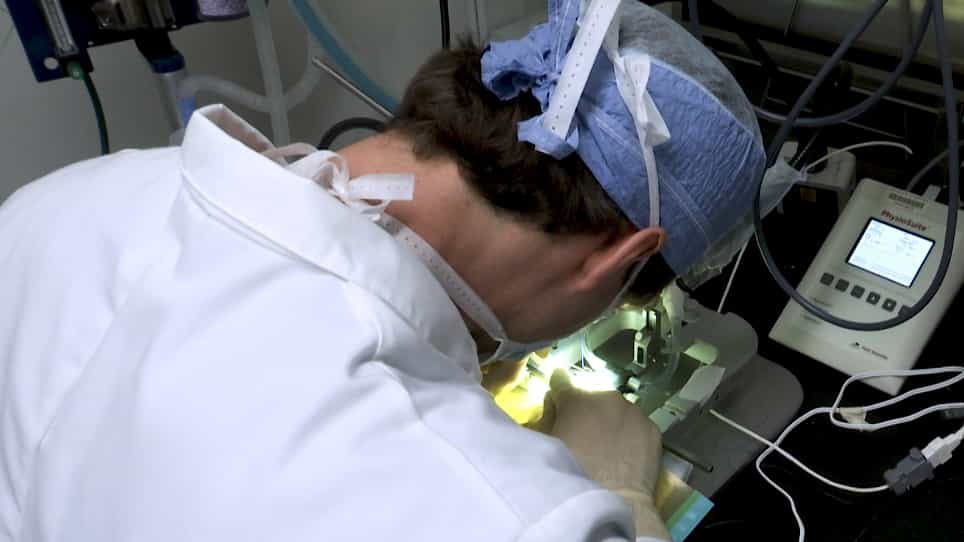

Use of a Wireless Video-EEG System to Monitor Epileptiform Discharges Following Lateral Fluid-Percussion Induced Traumatic Brain Injury
Published on: June 21, 2019
Video-EEG-monitoring to guide antiseizure medication withdrawal
Laurien K L Dhaenens-Meyer1, Elisabeth Schriewer2, Yvonne G Weber2
1Department of Epileptology and Neurology, RWTH Aachen University, Aachen, Germany. laurien_dhaenens@hotmail.com.

Background:
Discontinuing anti-seizure medication (ASM) should be considered in persons with epilepsy with long-term seizure freedom. Clinicians should also pursue ASM withdrawal in persons with one-time seizures without increased recurrence risk and those with suspected non-epileptic events. However, ASM withdrawal is associated with the risk of recurring seizures. Monitored ASM withdrawal in an epilepsy monitoring unit (EMU) could help better evaluate the risk of seizure recurrence. Here, we investigate the practice of EMU-guided ASM withdrawal, assess its indications, and aim to determine positive and negative predictors for successful withdrawal.
Methods:
We screened the medical records of all patients admitted to our EMU between November 1, 2019, and October 31, 2021, and included patients of at least 18 years admitted with the aim of permanent ASM withdrawal. We defined four groups of withdrawal indications: (1) long-term seizure freedom; (2) suspected non-epileptic events; (3) history of epileptic seizures but not fulfilling diagnostic criteria of epilepsy; and (4) seizure-freedom after epilepsy surgery. Successful withdrawal was defined according to the following criteria: no recoding of (sub)clinical seizure activity during VEM (groups 1, 2, and 3), patients did not meet the International League Against Epilepsy (ILAE) definition of epilepsy (groups 2 and 3) [14], and patients were discharged without ongoing ASM treatment (all groups). We also evaluated the prediction model by Lamberink et al. (LPM) for the risk of seizure recurrence in groups 1 and 3.
Results:
55/651 (8.6%) patients fulfilled the inclusion criteria. Withdrawal indications were distributed as follows; group 1: 2/55 (3.6%); group 2: 44/55 (80%); group 3: 9/55 (16,4%); group 4: 0/55. Overall, ASM withdrawal was successful in 90.9%. The sensitivity of the LPM for a 2-year 50% relapse risk threshold was 75%, the specificity 33.3%; for a 5-year relapse risk respectively 12.5% and 33.3%, suggesting that the model is not suitable for risk assessment in patients with one-time seizures or acute-symptomatic seizures, who constituted most of the evaluated patients.
Conclusions:
Our study suggests that EMU-guided ASM withdrawal could be a helpful tool to support clinical decision-making and improve patient safety. Prospective, randomized trials should further evaluate this method in the future.

Related Concept Videos
 01:24
Epilepsy and Seizures: Overview
Various factors can trigger epilepsy, including genetic factors, brain damage, metabolic causes, and unknown etiology. Diagnosis of epilepsy involves electroencephalography (EEG), which...
 01:20
Antiepileptic Drugs: Potassium Channel Activators
Ezogabine has gained approval as an adjunctive treatment...
 01:30
Electroconvulsive Therapy
 01:13
Seizures: Classification
Seizures are typically classified into two main categories: focal and generalized seizures.
Focal Seizures
Focal seizures originate from specific regions of the brain. These seizures are further sub-classified into two types: