Related Experiment Video
Updated: Jul 30, 2025
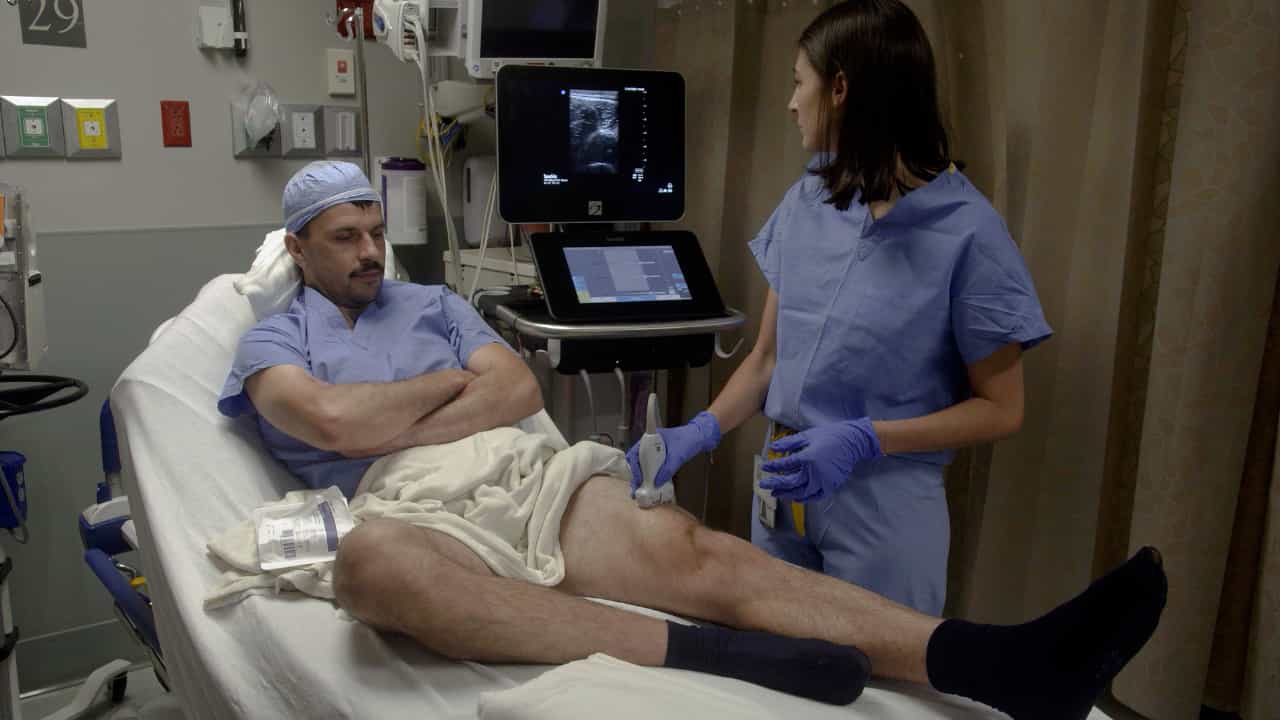
Author Spotlight: Assessing Surgical Frailty with Point-of-Care Ultrasound of Quadriceps Muscles
Published on: July 26, 2024
Impact of Frailty on the Development of Proximal Junctional Failure: Does Frailty Supersede Achieving Optimal
Oscar Krol1, Kimberly McFarland1, Stephane Owusu-Sarpong2
1Departments of Orthopaedic and Neurologic Surgery, NYU Langone Orthopedic Hospital; New York Spine Institute, New York, NY.

Background:
Patients undergoing surgery for adult spinal deformity (ASD) are often elderly, frail, and at elevated risk of adverse events perioperatively, with proximal junctional failure (PJF) occurring relatively frequently. Currently, the specific role of frailty in potentiating this outcome is poorly defined.
Purpose:
To determine if the benefits of optimal realignment in ASD, with respect to the development of PJF, can be offset by increasing frailty.
Study Design:
Retrospective cohort.
Materials And Methods:
Operative ASD patients (scoliosis >20°, SVA>5 cm, pelvic tilt>25°, or TK>60°) fused to the pelvis or below with available baseline and 2-year (2Y) radiographic and HRQL data were included. The Miller Frailty Index (FI) was used to stratify patients into 2 categories: Not Frail (FI <3) and Frail (>3). Proximal Junctional Failure (PJF) was defined using the Lafage criteria. "Matched" and "unmatched" refers to ideal age-adjusted alignment postoperatively. Multivariable regression determined the impact of frailty on the development of PJF.
Results:
Two hundred eighty-four ASD patients met inclusion criteria [62.2yrs±9.9, 81%F, BMI: 27.5 kg/m 2 ±5.3, ASD-FI: 3.4±1.5, Charlson Comorbidity Index (CCI): 1.7±1.6]. Forty-three percent of patients were characterized as Not Frail (NF) and 57% were characterized as Frail (F). PJF development was lower in the NF group compared with the F group (7% vs . 18%; P =0.002). F patients had 3.2 × higher risk of PJF development compared to NF patients (OR: 3.2, 95% CI: 1.3-7.3, P =0.009). Controlling for baseline factors, F unmatched patients had a higher degree of PJF (OR: 1.4, 95% CI:1.02-1.8, P =0.03); however, with prophylaxis, there was no increased risk. Adjusted analysis shows F patients, when matched postoperatively in PI-LL, had no significantly higher risk of PJF.
Conclusions:
An increasingly frail state is significantly associated with the development of PJF after corrective surgery for ASD. Optimal realignment may mitigate the impact of frailty on eventual PJF. Prophylaxis should be considered in frail patients who do not reach ideal alignment goals.
More Related Videos
 07:35
Creating Rigidly Stabilized Fractures for Assessing Intramembranous Ossification, Distraction Osteogenesis, or Healing of Critical Sized Defects
Published on: April 11, 2012
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:22
Mitral Valve Prolapse II: Assessment and Management