Related Experiment Video
Updated: Jul 29, 2025
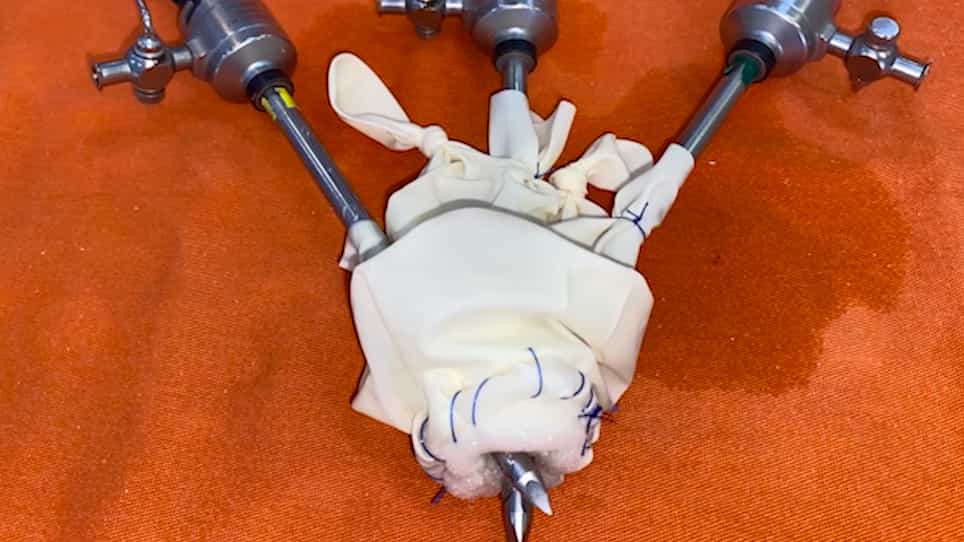
Low-Cost Single-Port LoCoSP Device for a Transcervical Approach in Minimally Invasive Transhiatal Esophagectomy
Published on: September 11, 2021
Non-curative resection for surgical T4b esophageal cancer: esophagectomy or non-esophagectomy?
Yusuke Fujii1,2,3, Hiroyuki Daiko4,5, Kentaro Kubo1
1Department of Esophageal Surgery, National Cancer Center Hospital, 5-1-1 Tsukiji, Chuo-Ku, Tokyo, 104-0045, Japan.

Background:
Recently, with the development of multidisciplinary treatment, the treatment outcomes of esophageal cancer (EC) have improved. However, despite advances in diagnostic imaging modalities, preoperative diagnosis of T4 EC is still difficult, and the prognosis of T4 EC remains very poor. In addition, the prognosis of surgical T4b EC (sT4b EC) after surgery remains unclear. In this study, we retrospectively reviewed sT4b EC.
Methods:
We evaluated the clinical course of sT4b EC and compared palliative esophagectomy with R2 resection (PE group) with other procedures without esophagectomy (NE group) (e.g., only esophagostomy) for sT4b EC.
Results:
Forty-seven patients with thoracic EC underwent R2 resection at our institution between January 2009 and December 2020. Thirty-four patients were in the PE group, and 13 patients were in the NE group. The 2-year overall survival rate was 0% in the PE group and 20.2% in the NE group (p = 0.882). There was one case of long-term survival in the NE group that underwent surgery followed by definitive chemoradiation. Postoperative complications (Clavien-Dindo grade ≥ 3) were observed in 25 patients (73.5%) in the PE group and in three patients (23.1%) in the NE group (p = 0.031). The median time to the initiation of postoperative treatment was 68.1 days in the PE group and 18.6 days in the NE group (p = 0191).
Conclusions:
If EC is diagnosed as sT4b, palliative esophagectomy should be avoided because of the high complication rate and the lack of long-term survival.
More Related Videos
 09:40
An Ivor Lewis Esophagectomy Designed to Minimize Anastomotic Complications and Optimize Conduit Function
Published on: April 17, 2020
 08:26
Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
Related Concept Videos
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...