Related Experiment Video
Updated: Jul 29, 2025

Intracoronary Acetylcholine Provocation Testing for Assessment of Coronary Vasomotor Disorders
Published on: August 18, 2016
Contextual community epinephrine prescribing: Is more always better?
Marcus Shaker1, Elissa M Abrams2, J Wesley Sublett3
1Section of Allergy and Immunology, Dartmouth-Hitchcock Medical Center, Lebanon, New Hampshire; Department of Medicine and Pediatrics, Dartmouth Geisel School of Medicine, Hanover, New Hampshire.

Objective:
Prompt administration of epinephrine is first-line management of anaphylaxis. Although severe anaphylaxis may require more than 1 epinephrine dose, multiple epinephrine device packs may not be necessary for all patients at risk for allergic reactions.
Data Sources:
A narrative review was used to describe key considerations to contextualize community epinephrine prescribing.
Results:
Anaphylaxis has a lifetime prevalence of 1.6% to 5.1%. Meeting diagnostic criteria for anaphylaxis is not required for epinephrine treatment of a severe allergic reaction. A "1-2-3" approach to anaphylaxis treatment is important to clearly relay central management steps: promptly administer a first dose of intramuscular epinephrine with proper positioning, and activate emergency medical services if immediate symptom resolution does not occur; consider a second dose of intramuscular epinephrine with consideration of oxygen administration and intravenous fluid if initial epinephrine response is not adequate; and consider a third intramuscular epinephrine dose together with consideration of intravenous fluid support and oxygen for continued lack of appropriate response. Although multiple epinephrine doses may be required to treat severe anaphylaxis, 90% of anaphylaxis cases do not require more than 1 epinephrine dose. A universal requirement for multiple epinephrine devices in patients without a history of anaphylaxis is not cost-effective. Patients without a history of anaphylaxis may be managed without multiple device prescriptions within a patient-preference sensitive paradigm of care.
Conclusion:
Anaphylaxis prevention involves appropriate education to avoid allergen triggers, recognize symptoms of an allergic reaction, rapidly access and administer intramuscular epinephrine, and appropriately activate emergency medical services when needed. For patients with previous anaphylaxis, particularly those who have required more than 1 dose of epinephrine to treat an allergic reaction, possessing multiple epinephrine devices is an important part of managing community anaphylaxis risk.
Related Concept Videos
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and...
 01:28
Adrenergic Agonists: Mixed-Action Agents
Ephedrine and pseudoephedrine lack a catecholamine group, making them less susceptible to degradation by metabolic enzymes. They have increased oral bioavailability and lipophilicity, resulting in a longer duration of action. Their response is reduced by...
 01:30
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:18
Adrenergic Agonists: Therapeutic Classification
Vasopressor or pressor agents: They increase blood pressure and function as cardiac stimulants. Examples include endogenous catecholamines (norepinephrine and dopamine) and synthetic agents (phenylephrine).
Bronchodilators: β2-agonists can relax bronchial muscles and widen airways. They are commonly used for treating obstructive pulmonary...
 01:26
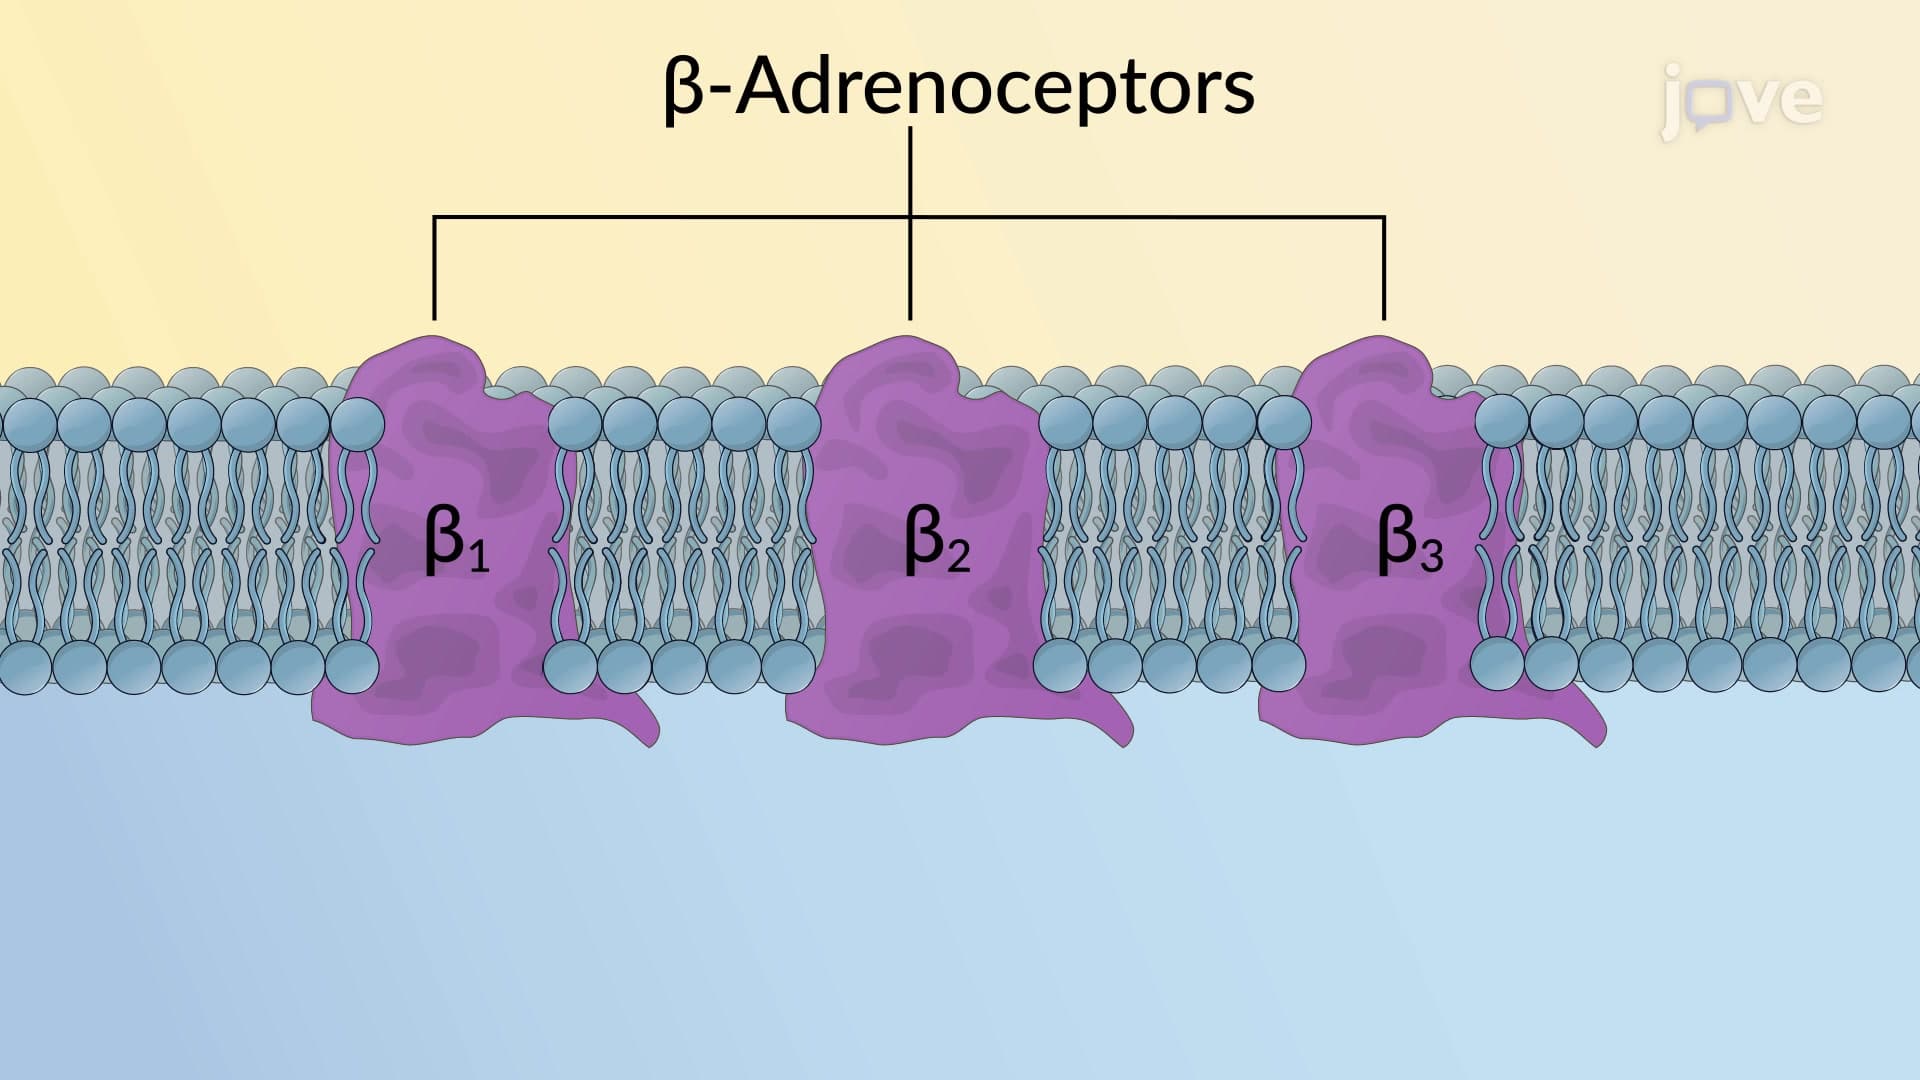
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
 01:16
Adrenergic Agonists: Chemistry and Structure-Activity Relationship
Aromatic ring substitutions: Substituting the aromatic ring with –OH groups at positions 3 and 4 yields catecholamines (e.g., epinephrine), which have a high affinity for adrenoceptors. Hydrogen bonding between –OH groups and receptors enhances adrenergic activity.
Separation of...