Related Experiment Video
Updated: Jul 29, 2025


Isolation of Human Islets from Partially Pancreatectomized Patients
Published on: July 30, 2011
Systematic Review of Treatment of Beta-Cell Monogenic Diabetes
Rochelle N Naylor1, Kashyap A Patel2, Jarno L T Kettunen3
1Departments of Pediatrics and Medicine, University of Chicago, Chicago, Illinois, USA.

Background:
Beta-cell monogenic forms of diabetes are the area of diabetes care with the strongest support for precision medicine. We reviewed treatment of hyperglycemia in GCK-related hyperglycemia, HNF1A-HNF4A- and HNF1B-diabetes, Mitochondrial diabetes (MD) due to m.3243A>G variant, 6q24-transient neonatal diabetes (TND) and SLC19A2-diabetes.
Methods:
Systematic reviews with data from PubMed, MEDLINE and Embase were performed for the different subtypes. Individual and group level data was extracted for glycemic outcomes in individuals with genetically confirmed monogenic diabetes.
Results:
147 studies met inclusion criteria with only six experimental studies and the rest being single case reports or cohort studies. Most studies had moderate or serious risk of bias.For GCK-related hyperglycemia, six studies (N=35) showed no deterioration in HbA1c on discontinuing glucose lowering therapy. A randomized trial (n=18 per group) showed that sulfonylureas (SU) were more effective in HNF1A-diabetes than in type 2 diabetes, and cohort and case studies supported SU effectiveness in lowering HbA1c. Two crossover trials (n=15 and n=16) suggested glinides and GLP-1 receptor agonists might be used in place of SU. Evidence for HNF4A-diabetes was limited. While some patients with HNF1B-diabetes (n=301) and MD (n=250) were treated with oral agents, most were on insulin. There was some support for the use of oral agents after relapse in 6q24-TND, and for thiamine improving glycemic control and reducing insulin requirement in SLC19A2-diabetes (less than half achieved insulin-independency).
Conclusion:
There is limited evidence to guide the treatment in monogenic diabetes with most studies being non-randomized and small. The data supports: no treatment in GCK-related hyperglycemia; SU for HNF1A-diabetes. Further evidence is needed to examine the optimum treatment in monogenic subtypes.
More Related Videos
 09:31
Sustained Administration of β-cell Mitogens to Intact Mouse Islets Ex Vivo Using Biodegradable Poly(lactic-co-glycolic acid) Microspheres
Published on: November 5, 2016
 10:03
Bioluminescent Monitoring of Graft Survival in an Adoptive Transfer Model of Autoimmune Diabetes in Mice
Published on: November 18, 2022
Related Concept Videos
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility,...
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:25
Insulin: Biosynthesis, Chemistry, and Preparation
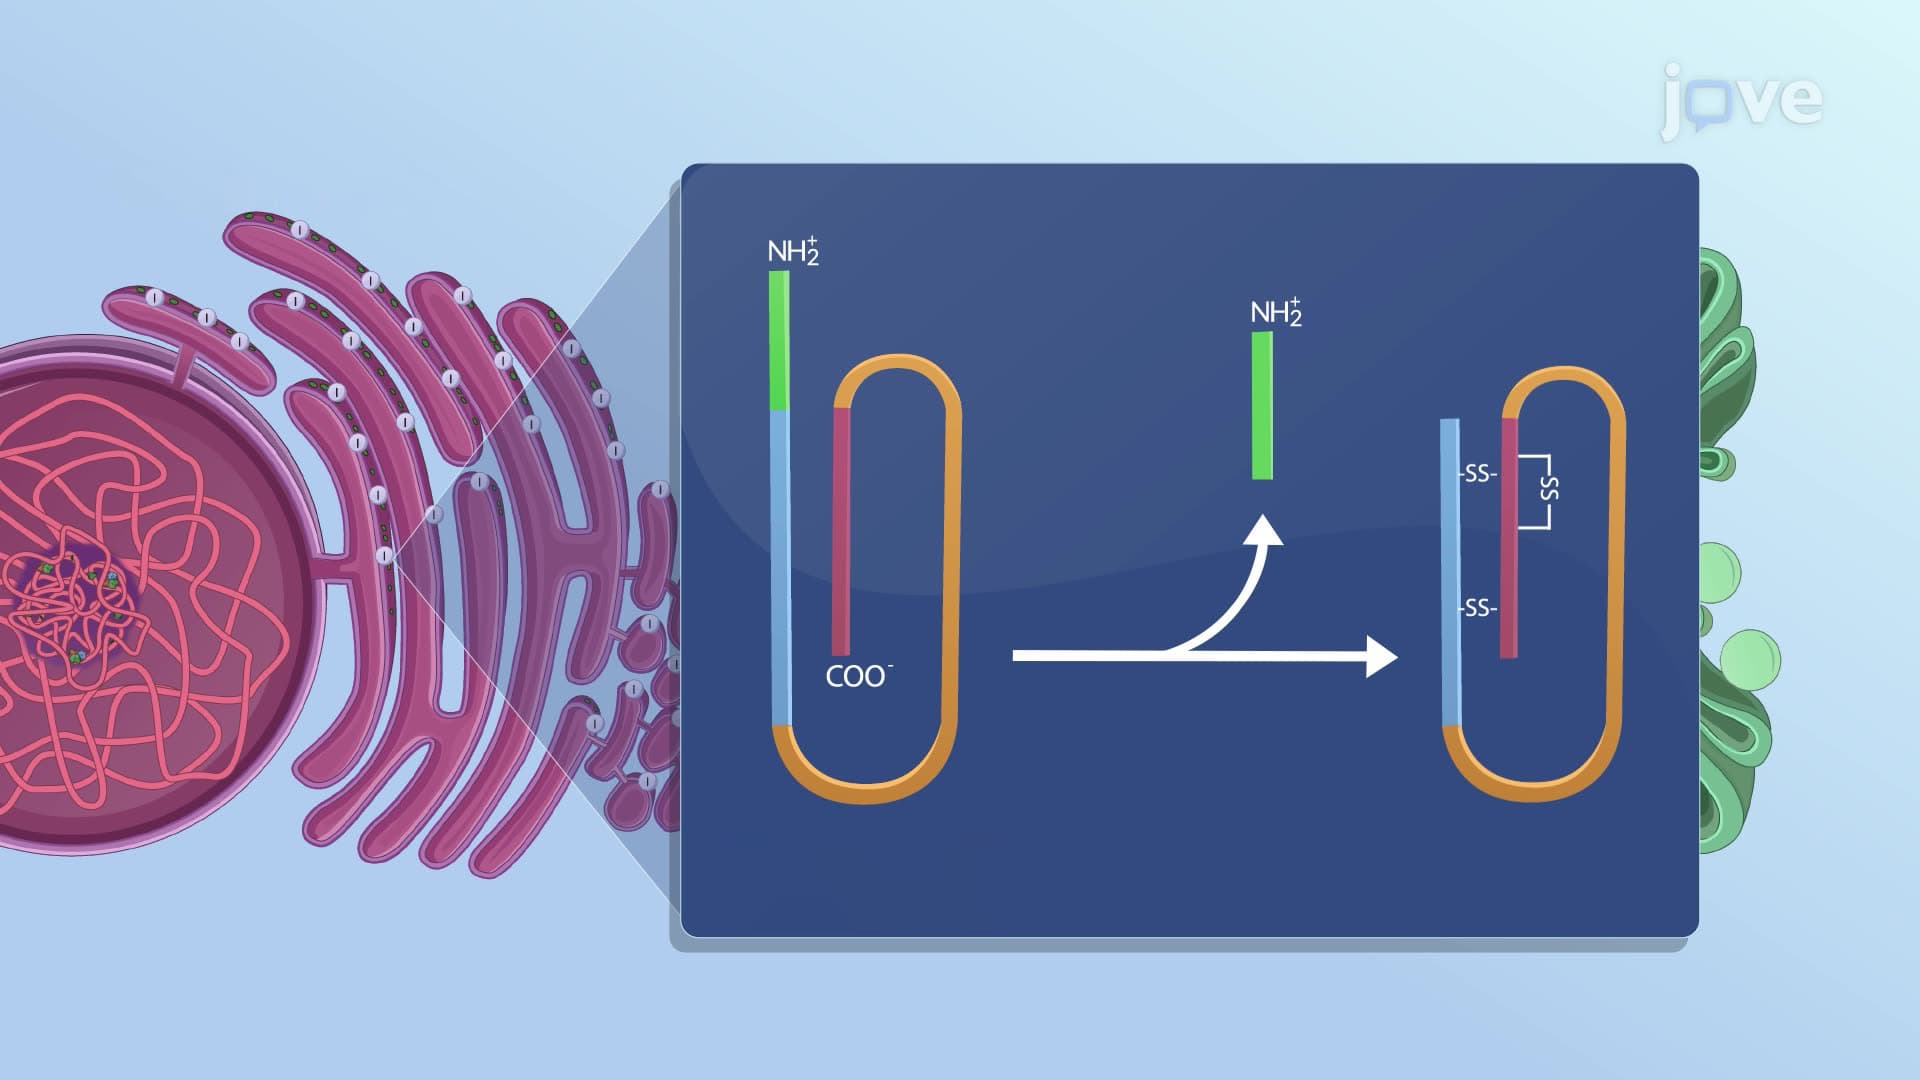
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment...
 01:36
Carbohydrate Metabolism
Starch accounts for approximately 60% of the carbohydrates consumed by humans. Since amylase enzymes cannot function in the stomach's acidic environment, starch can only be digested in the mouth and small intestine. Simple sugars are found naturally in milk and fruits in...