Related Experiment Video
Updated: Jul 29, 2025


Effects of Blast-induced Neurotrauma on Pressurized Rodent Middle Cerebral Arteries
Published on: April 1, 2019
Effect of driving pressure on early postoperative lung gas distribution in supratentorial craniotomy: a randomized
Feifei Liu1,2, Wei Zhang1, Zhanqi Zhao3
1Department of Anesthesiology, Beijing Tiantan Hospital, Capital Medical University, No. 119, Southwest 4th Ring Road, Fengtai District, Beijing, 100070, China.

Background:
Neurosurgical patients represent a high-risk population for postoperative pulmonary complications (PPCs). A lower intraoperative driving pressure (DP) is related to a reduction in postoperative pulmonary complications. We hypothesized that driving pressure-guided ventilation during supratentorial craniotomy might lead to a more homogeneous gas distribution in the lung postoperatively.
Methods:
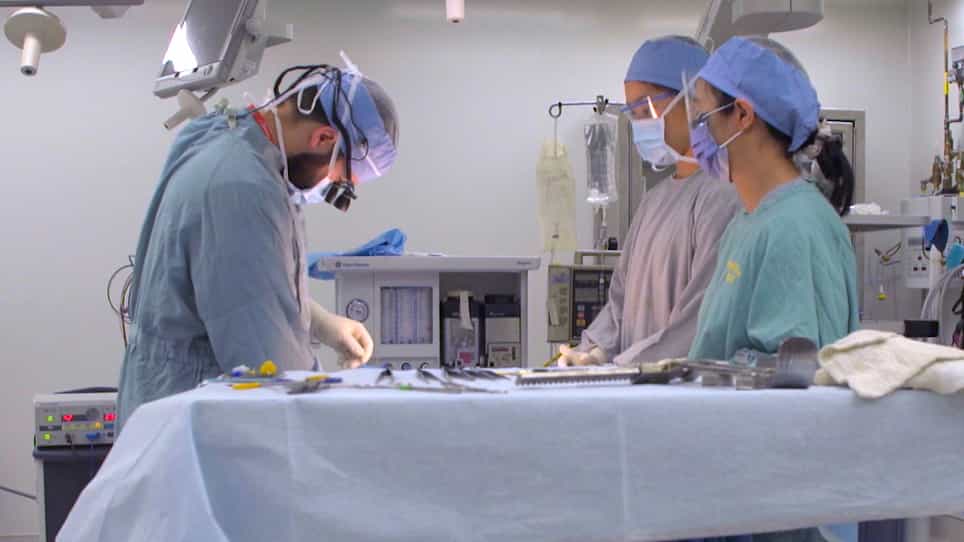
This was a randomized trial conducted between June 2020 and July 2021 at Beijing Tiantan Hospital. Fifty-three patients undergoing supratentorial craniotomy were randomly divided into the titration group or control group at a ratio of 1 to 1. The control group received 5 cmH2O PEEP, and the titration group received individualized PEEP targeting the lowest DP. The primary outcome was the global inhomogeneity index (GI) immediately after extubation obtained by electrical impedance tomography (EIT). The secondary outcomes were lung ultrasonography scores (LUSs), respiratory system compliance, the ratio of the partial pressure of arterial oxygen to the fraction of inspired oxygen (PaO2/FiO2) and PPCs within 3 days postoperatively.
Results:
Fifty-one patients were included in the analysis. The median (IQR [range]) DP in the titration group versus the control group was 10 (9-12 [7-13]) cmH2O vs. 11 (10-12 [7-13]) cmH2O, respectively (P = 0.040). The GI tract did not differ between groups immediately after extubation (P = 0.080). The LUSS was significantly lower in the titration group than in the control group immediately after tracheal extubation (1 [0-3] vs. 3 [1-6], P = 0.045). The compliance in the titration group was higher than that in the control group at 1 h after intubation (48 [42-54] vs. 41 [37-46] ml·cmH2O-1, P = 0.011) and at the end of surgery (46 [42-51] vs. 41 [37-44] ml·cmH2O-1, P = 0.029). The PaO2/FiO2 ratio was not significantly different between groups in terms of the ventilation protocol (P = 0.117). At the 3-day follow-up, no postoperative pulmonary complications occurred in either group.
Conclusions:
Driving pressure-guided ventilation during supratentorial craniotomy did not contribute to postoperative homogeneous aeration, but it may lead to improved respiratory compliance and lower lung ultrasonography scores.
Clinical Trial Registration:
ClinicalTrials.gov NCT04421976.

Related Concept Videos
 01:24
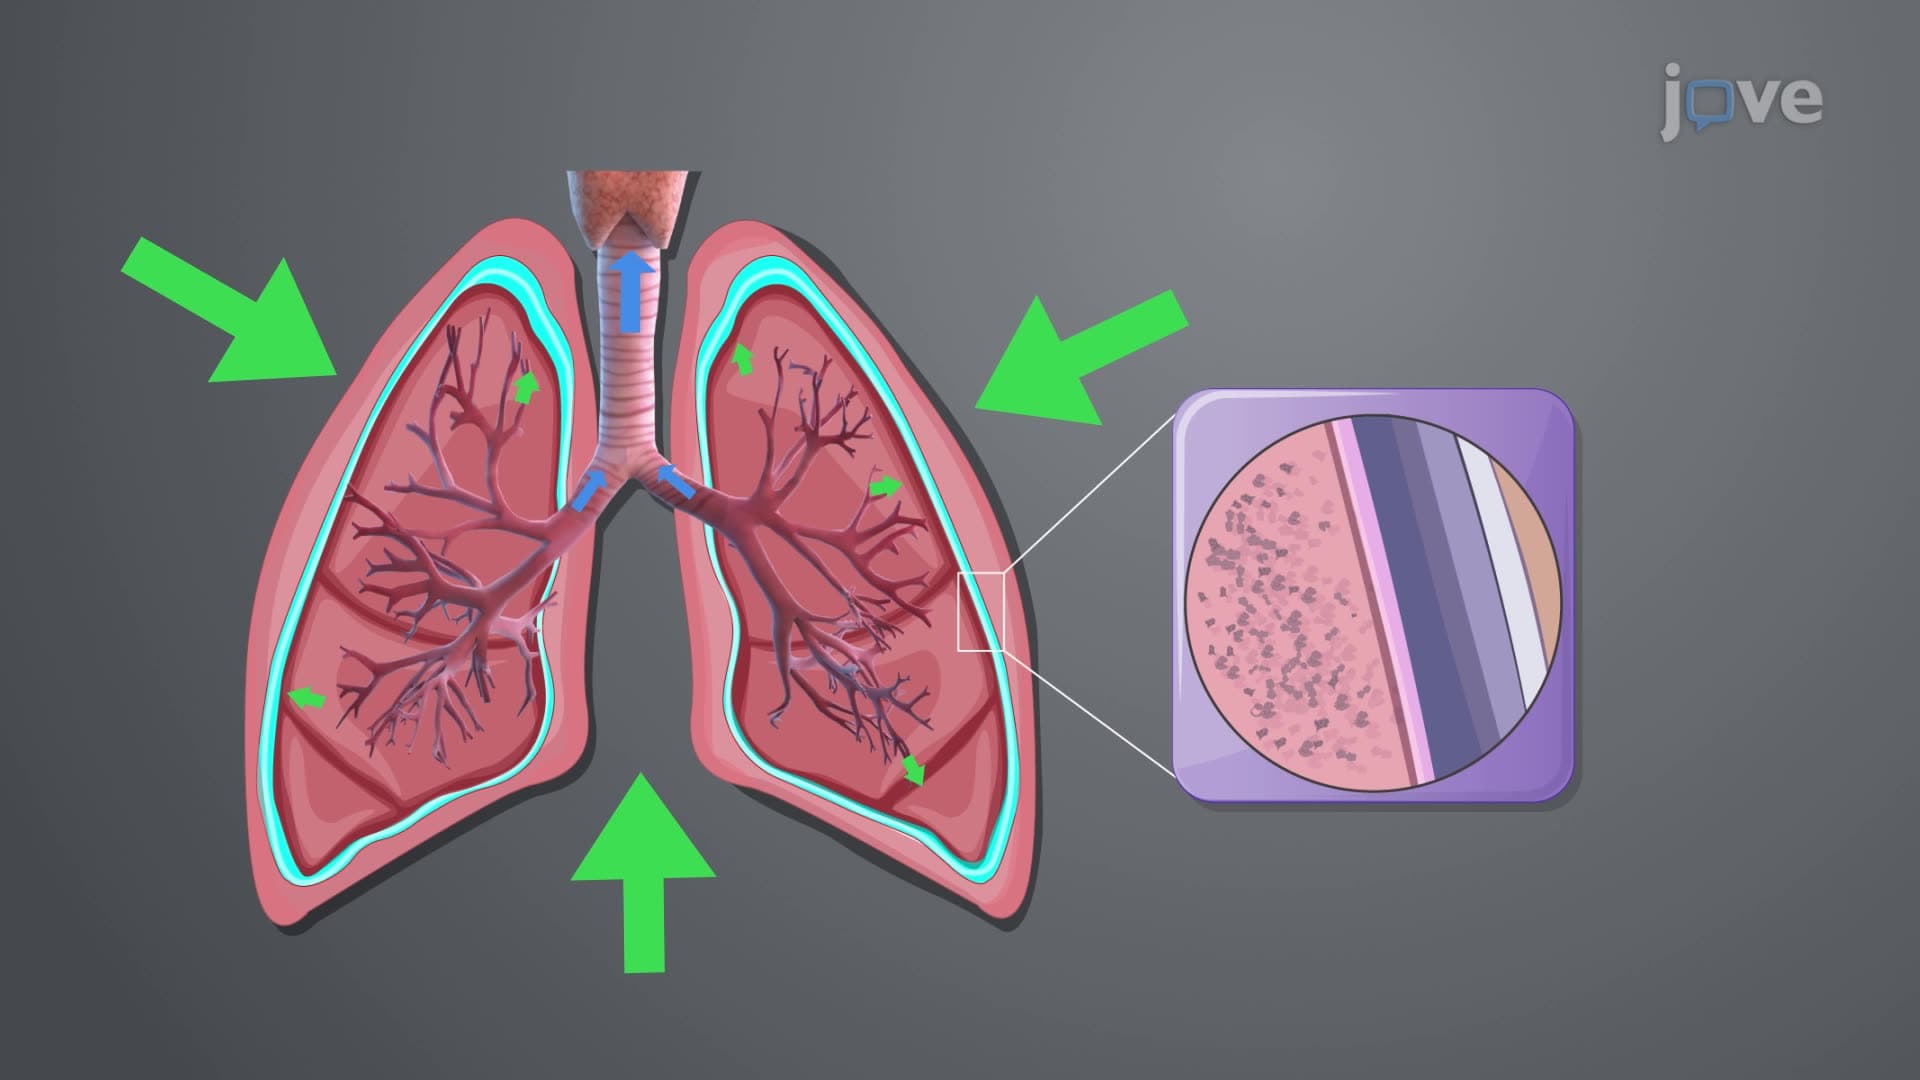
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs...
 01:24
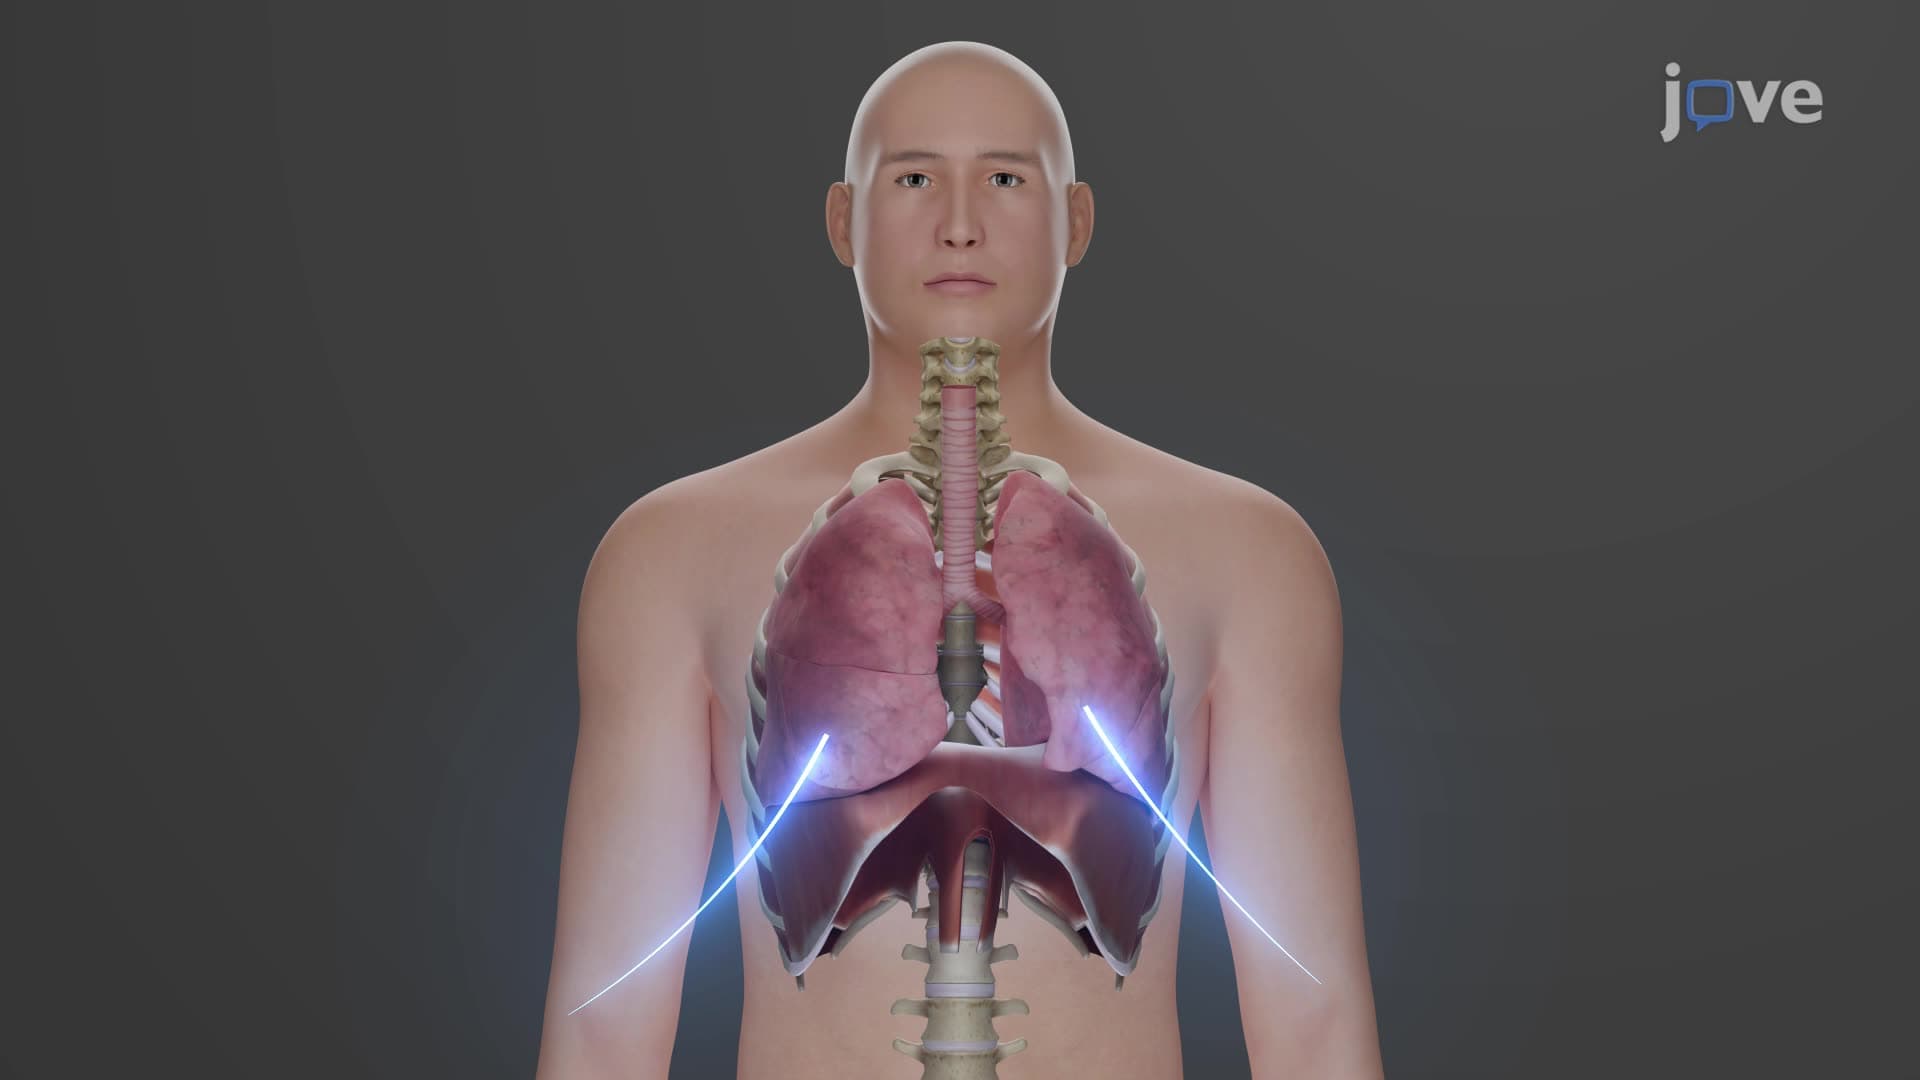
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...