Related Experiment Video
Updated: Jul 29, 2025
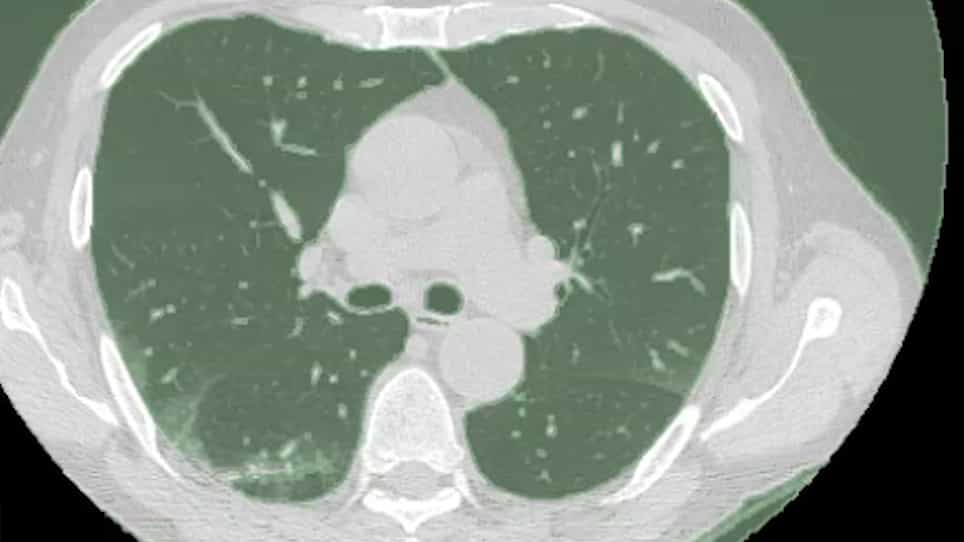

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Critical Damage of Lung Parenchyma Complicated with Massive Pneumothorax in COVID-19 Pneumonia
Maria Iuliana Ghenu1,2, Maria Mirabela Manea1,3, Delia Timofte4
1"Carol Davila" University of Medicine and Pharmacy, Bucharest, Romania [Faculty of Medicine, Medical Semiology Department (MIG, DI, DD), Faculty of Medicine, Functional Sciences Department, Physiology Discipline (MCC), Faculty of Medicine, Clinical Neurosciences Department (MM), Faculty of Dental Medicine, Physiology Discipline (AEBS), Faculty of Medicine, Embryology Department (RT)].

Abstract:
It is already known that Coronavirus disease 2019 (COVID-19) may lead to various degrees and forms of lung parenchyma damage, but some cases take a strikingly severe course that is difficult to manage. We report the case of a 62-year old male, non-obese, non-smoker, and non-diabetic, who presented with fever, chills, and shortness of breath. The infection with severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) was diagnosed by real-time Polymerase Chain Reaction. Although the patient had been vaccinated with 2 doses of Pfizer-BioNTech COVID-19 vaccine 7 months earlier and had no risk factors for a severe outcome, serial computed tomography (CT) scan revealed lung involvement progressively extending from an initial 30% to 40% to almost 100% 2.5 months later. The spectrum of lung lesions included at first only ground-glass opacities and some tiny emphysema bullae, but later also bronchiectasis, pulmonary fibrosis, and large emphysema bullae as post-COVID-19 pulmonary sequelae. For fear of severe evolution of superimposed bacterial infection (Clostridoides difficile enterocolits and possibly bacterial pneumonia) the administration of corticosteroids was intermittent. Massive right pneumothorax secondary to bulla rupture, possibly favored by the indispensable high flow oxygen therapy, led to respiratory failure compounded by hemodynamic instability, and ultimately to the patient's final demise. COVID-19 pneumonia may cause severe lung parenchyma damage which requires long-term supplemental oxygen therapy. Beneficial or even lifesaving as it might be, high flow oxygen therapy may nonetheless have deleterious effects too, including the development of bullae that may rupture engendering pneumothorax. Corticosteroid treatment should probably be pursued despite superimposed bacterial infection to limit the viral induced damage to lung parenchyma.
More Related Videos
 09:28
Intravital Widefield Fluorescence Microscopy of Pulmonary Microcirculation in Experimental Acute Lung Injury Using a Vacuum-Stabilized Imaging System
Published on: April 6, 2022
 14:48
Visualizing Lung Cellular Adaptations during Combined Ozone and LPS Induced Murine Acute Lung Injury
Published on: March 21, 2021
Related Concept Videos
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:13
Pleura of the Lungs
 01:29
Pneumonia II: Pathophysiology
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...
 01:30
Pneumonia III: Complications and Assessment