Related Experiment Video
Updated: Jul 29, 2025

A Mouse 5/6th Nephrectomy Model That Induces Experimental Uremic Cardiomyopathy
Published on: November 7, 2017
Sex differences in Cardiorenal Syndrome: Insights from CARDIOREN Registry
Marta Cobo Marcos1,2, Rafael de la Espriella3, Jara Gayán Ordás4
1Department of Cardiology, Hospital Universitario Puerta de Hierro Majadahonda (IDIPHISA), Madrid, Spain.

Insights
Women with heart and kidney disease show higher rates of heart failure with preserved ejection fraction (HFpEF) and advanced chronic kidney disease (CKD). Men present more often with heart failure with reduced ejection fraction (HFrEF) and ischemic causes.
Area of Science:
- Cardiology
- Nephrology
- Sex-Based Medicine
Background:
- Sex-specific differences in heart failure (HF) and kidney disease (KD) are well-documented individually.
- The distinct cardiorenal syndrome (CRS) phenotypes by sex remain underexplored in contemporary patient cohorts.
Purpose of the Study:
- To investigate sex-related differences in cardiorenal syndrome (CRS) among outpatients with heart failure (HF).
Main Methods:
- Analysis of the prospective, multicenter Cardiorenal Spanish registry (CARDIOREN).
- Inclusion of 1107 chronic ambulatory HF patients, assessing estimated glomerular filtration rate (eGFR) and clinical characteristics.
- Statistical analysis to determine odds ratios (OR) and confidence intervals (CI) for sex-specific differences in CRS phenotypes.
Main Results:
- Women with kidney dysfunction showed higher odds of HF with preserved ejection fraction (HFpEF), valvular heart disease, anemia, advanced CKD, and congestion.
- Men with cardiorenal disease had higher odds of HF with reduced ejection fraction (HFrEF), ischemic cardiomyopathy, hypertension, atrial fibrillation, and hyperkalemia.
- Significant sex-related differences in cardiorenal phenotypes were observed in this HF cohort.
Conclusions:
- Distinct cardiorenal phenotypes exist between sexes in patients with combined heart and kidney disease.
- Women predominantly exhibit a cardiorenal phenotype characterized by advanced CKD, congestion, and HFpEF.
- Men are more frequently associated with HFrEF, ischemic etiology, hypertension, hyperkalemia, and atrial fibrillation.
Purpose Of The Work:
Although sex-specific differences in heart failure (HF) or kidney disease (KD) have been analyzed separately, the predominant cardiorenal phenotype by sex has not been described. This study aims to explore the sex-related differences in cardiorenal syndrome (CRS) in a contemporary cohort of outpatients with HF.
Findings:
An analysis of the Cardiorenal Spanish registry (CARDIOREN) was performed. CARDIOREN Registry is a prospective multicenter observational registry including 1107 chronic ambulatory HF patients (37% females) from 13 Spanish HF clinics. Estimated Glomerular Filtration Rate (eGFR) < 60 ml/min/1.73 m2 was present in 59.1% of the overall HF population, being this prevalence higher in the female population (63.2% vs. 56.6%, p = 0.032, median age: 81 years old, IQR:74-86). Among those with kidney dysfunction, women displayed higher odds of showing HF with preserved ejection fraction (HFpEF) (odds ratio [OR] = 4.07; confidence interval [CI] 95%: 2.65-6.25, p < 0.001), prior valvular heart disease (OR = 1.76; CI 95%:1.13-2.75, p = 0.014), anemia (OR: 2.02; CI 95%:1.30-3.14, p = 0.002), more advanced kidney disease (OR for CKD stage 3: 1.81; CI 95%:1.04-3.13, p = 0.034; OR for CKD stage 4: 2.49, CI 95%:1.31-4.70, p = 0.004) and clinical features of congestion (OR:1.51; CI 95%: 1.02-2.25, p = 0.039). On the contrary, males with cardiorenal disease showed higher odds of presenting HF with reduced ejection fraction (HFrEF) (OR:3.13; CI 95%: 1.90-5.16, p < 0.005), ischemic cardiomyopathy (OR:2.17; CI 95%: 1.31-3.61, p = 0.003), hypertension (OR = 2.11; CI 95%:1.18-3.78, p = 0.009), atrial fibrillation (OR:1.71; CI 95%: 1.06-2.75, p = 0.025), and hyperkalemia (OR:2.43, CI 95%: 1.31-4.50, p = 0.005). In this contemporary registry of chronic ambulatory HF patients, we observed sex-related differences in patients with combined heart and kidney disease. The emerging cardiorenal phenotype characterized by advanced CKD, congestion, and HFpEF was predominantly observed in women, whereas HFrEF, ischemic etiology, hypertension, hyperkalemia, and atrial fibrillation were more frequently observed in men.


Related Concept Videos
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:29
Heart Failure II: Pathophysiology
 01:22
Heart Failure Drugs: Diuretics
 01:29
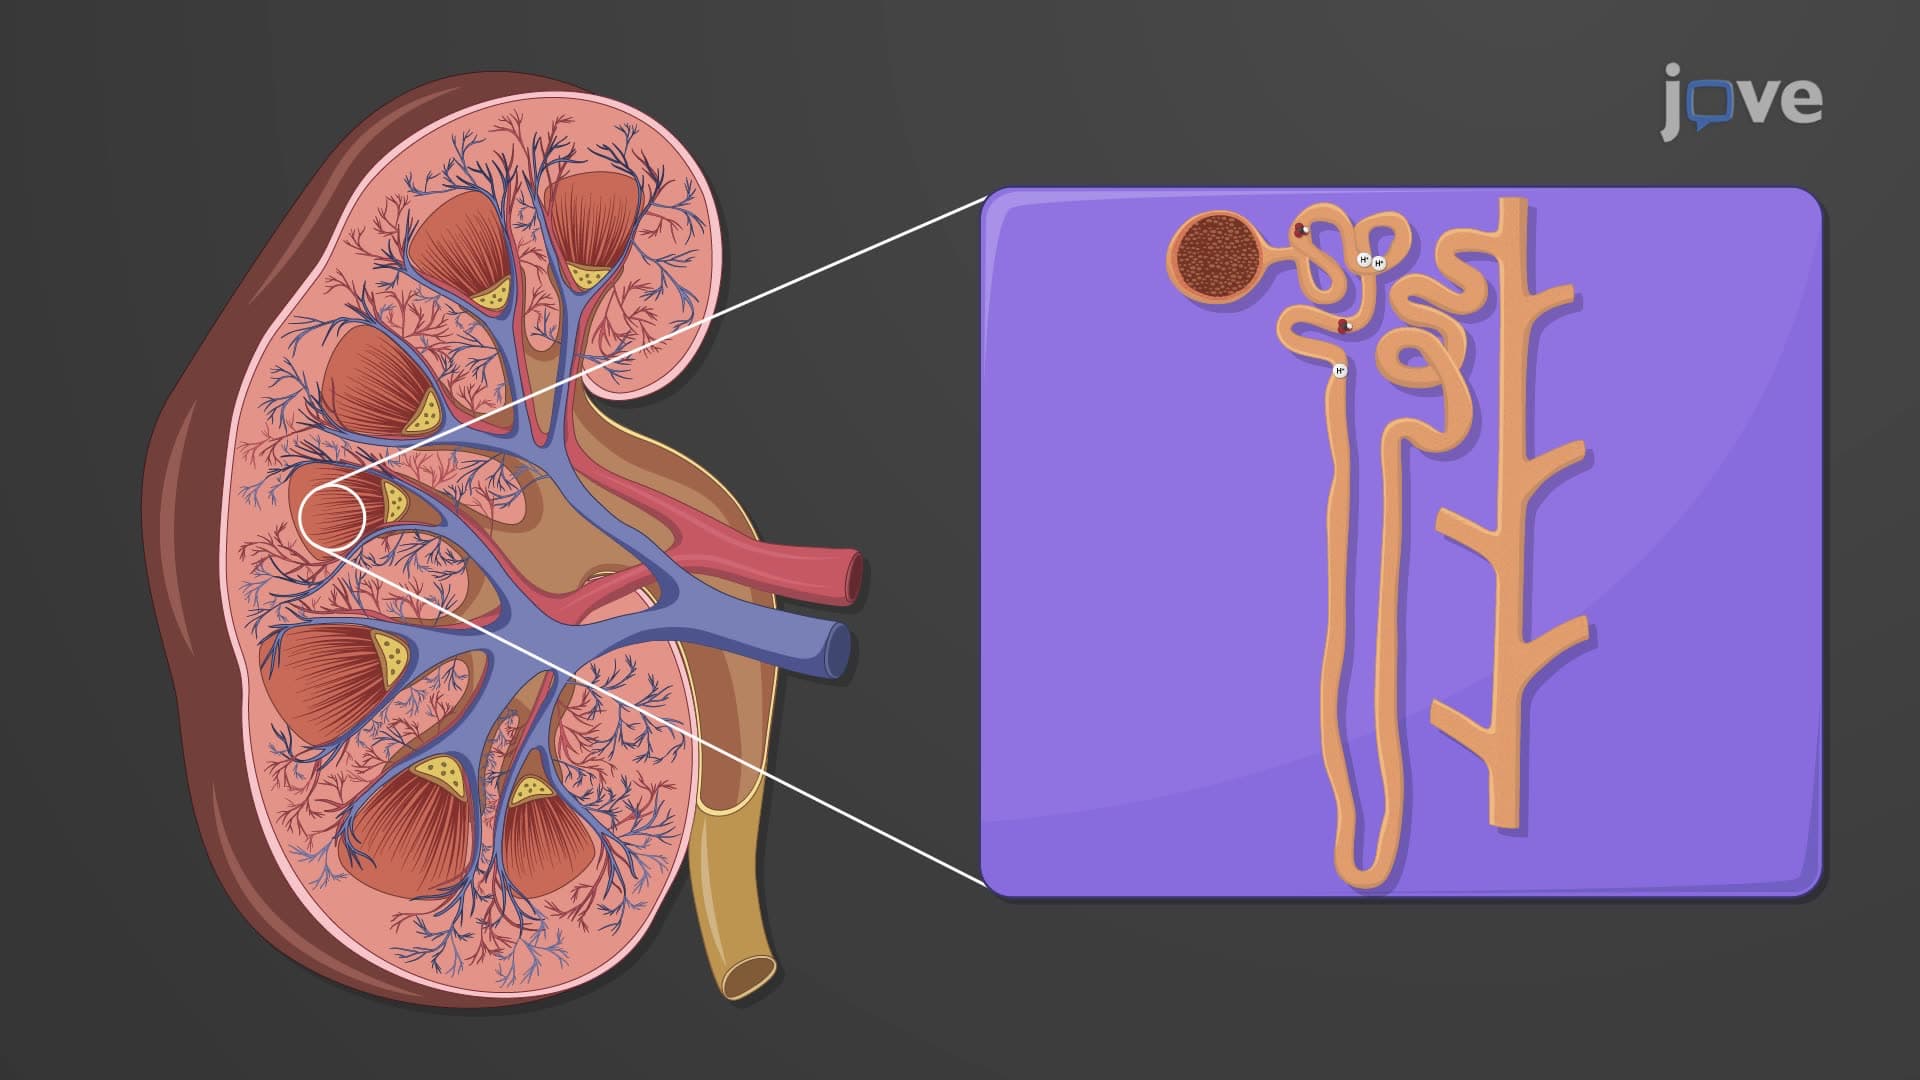
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:29
Cardiomyopathy V: Interprofessional Care
 01:29
Hypertension II: Pathophysiology