Related Experiment Video
Updated: Jul 29, 2025
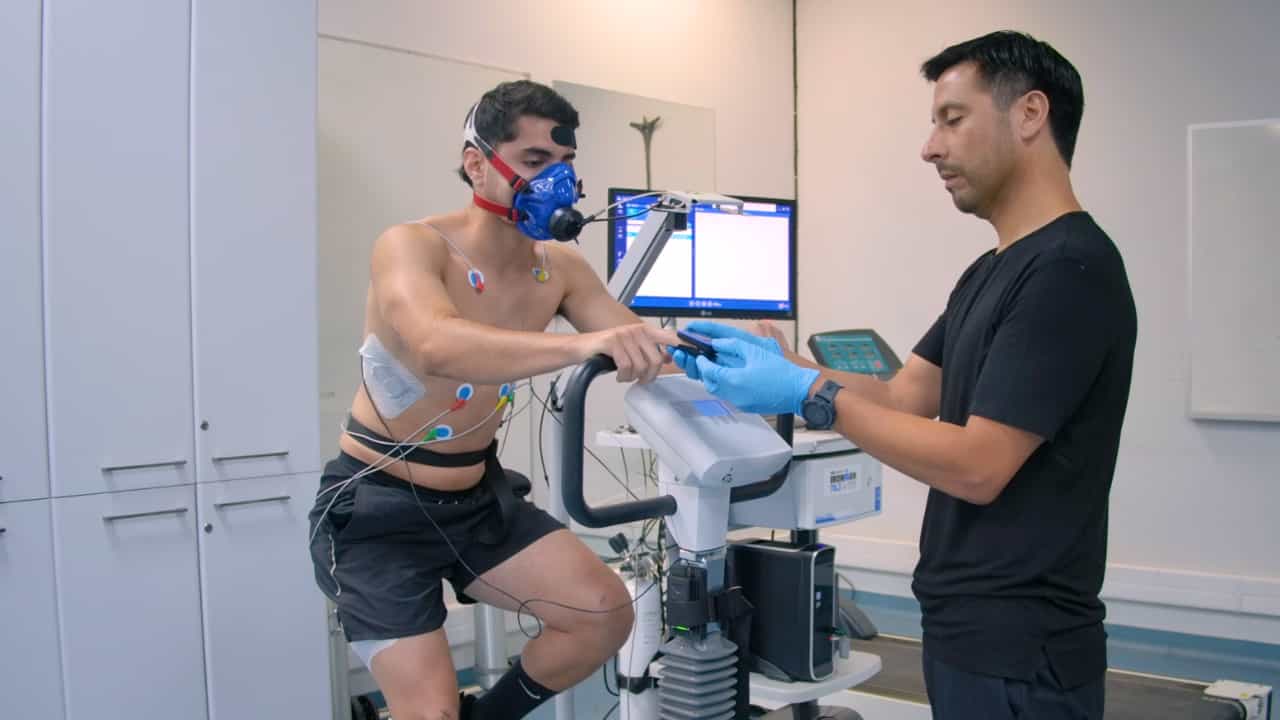
Using Near-Infrared Spectroscopy Wearable Devices to Identify Central Versus Peripheral Limitations During Exercise
Published on: December 19, 2024
Anticipatory central command on standing decreases cerebral blood velocity causing hypocapnia in hyperpneic postural
Julian M Stewart1,2, Marvin S Medow1,2
1Department of Pediatrics, New York Medical College, Valhalla, New York, United States.

Abstract:
Fifty percent of patients with postural tachycardia syndrome (POTS) are hypocapnic during orthostasis related to initial orthostatic hypotension (iOH). We determined whether iOH drives hypocapnia in POTS by low BP or decreased cerebral blood velocity (CBv). We studied three groups; healthy volunteers (n = 32, 18 ± 3 yr) were compared with POTS, grouped by presence [POTS-low end-tidal CO2 (↓ETCO2), n = 26, 19 ± 2 yr] or absence [POTS-normal upright end-tidal carbon dioxide (nlCO2), n = 28, 19 ± 3 yr] of standing hypocapnia defined by end-tidal CO2 (ETCO2) ≤ 30 mmHg at steady-state, measuring middle cerebral artery CBv, heart rate (HR), and beat-to-beat blood pressure (BP). After 30 min supine, subjects stood for 5 min. Quantities were measured prestanding, at minimum CBv, minimum BP, peak HR, CBv recovery, BP recovery, minimum HR, steady-state, and 5 min. Baroreflex gain was estimated by α index. iOH occurred with similar frequency and minimum BP in POTS-↓ETCO2 and POTS-nlCO2. Minimum CBv was reduced significantly (P < 0.05) in POTS-↓ETCO2 (48 ± 3 cm/s) preceding hypocapnia compared with POTS-nlCO2 (61 ± 3 cm/s) or Control (60 ± 2 cm/s). The anticipatory increased BP was significantly larger (P < 0.05) in POTS (8 ± 1 mmHg vs. 2 ± 1) and began ∼8 s prestanding. HR increased in all subjects, CBv increased significantly (P < 0.05) in both POTS-nlCO2 (76 ± 2 to 85 ± 2 cm/s) and Control (75 ± 2 to 80 ± 2 cm/s) consistent with central command. CBv decreased in POTS-↓ETCO2 (76 ± 3 to 64 ± 3 cm/s) correlating with decreased baroreflex gain. Cerebral conductance [meanCBv/mean arterial blood pressure (MAP)] was reduced in POTS-↓ETCO2 throughout. Data support the hypothesis that excessively reduced CBv during iOH may intermittently reduce carotid body blood flow, sensitizing that organ and producing postural hyperventilation in POTS-↓ETCO2. Excessive fall in CBv occurs in part during prestanding central command and is a facet of defective parasympathetic regulation in POTS.NEW & NOTEWORTHY Dyspnea is frequent in postural tachycardia syndrome (POTS) and is associated with upright hyperpnea and hypocapnia that drives sinus tachycardia. It is initiated by an exaggerated reduction in cerebral conductance and decreased cerebral blood flow (CBF) that precedes the act of standing. This is a form of autonomically mediated "central command." Cerebral blood flow is further reduced by initial orthostatic hypotension common in POTS. Hypocapnia is maintained during the standing response and might account for persistent postural tachycardia.
More Related Videos
 14:09
Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
 04:20
Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Related Concept Videos
 01:25
Hyperpnea and Hyperventilation
 01:31
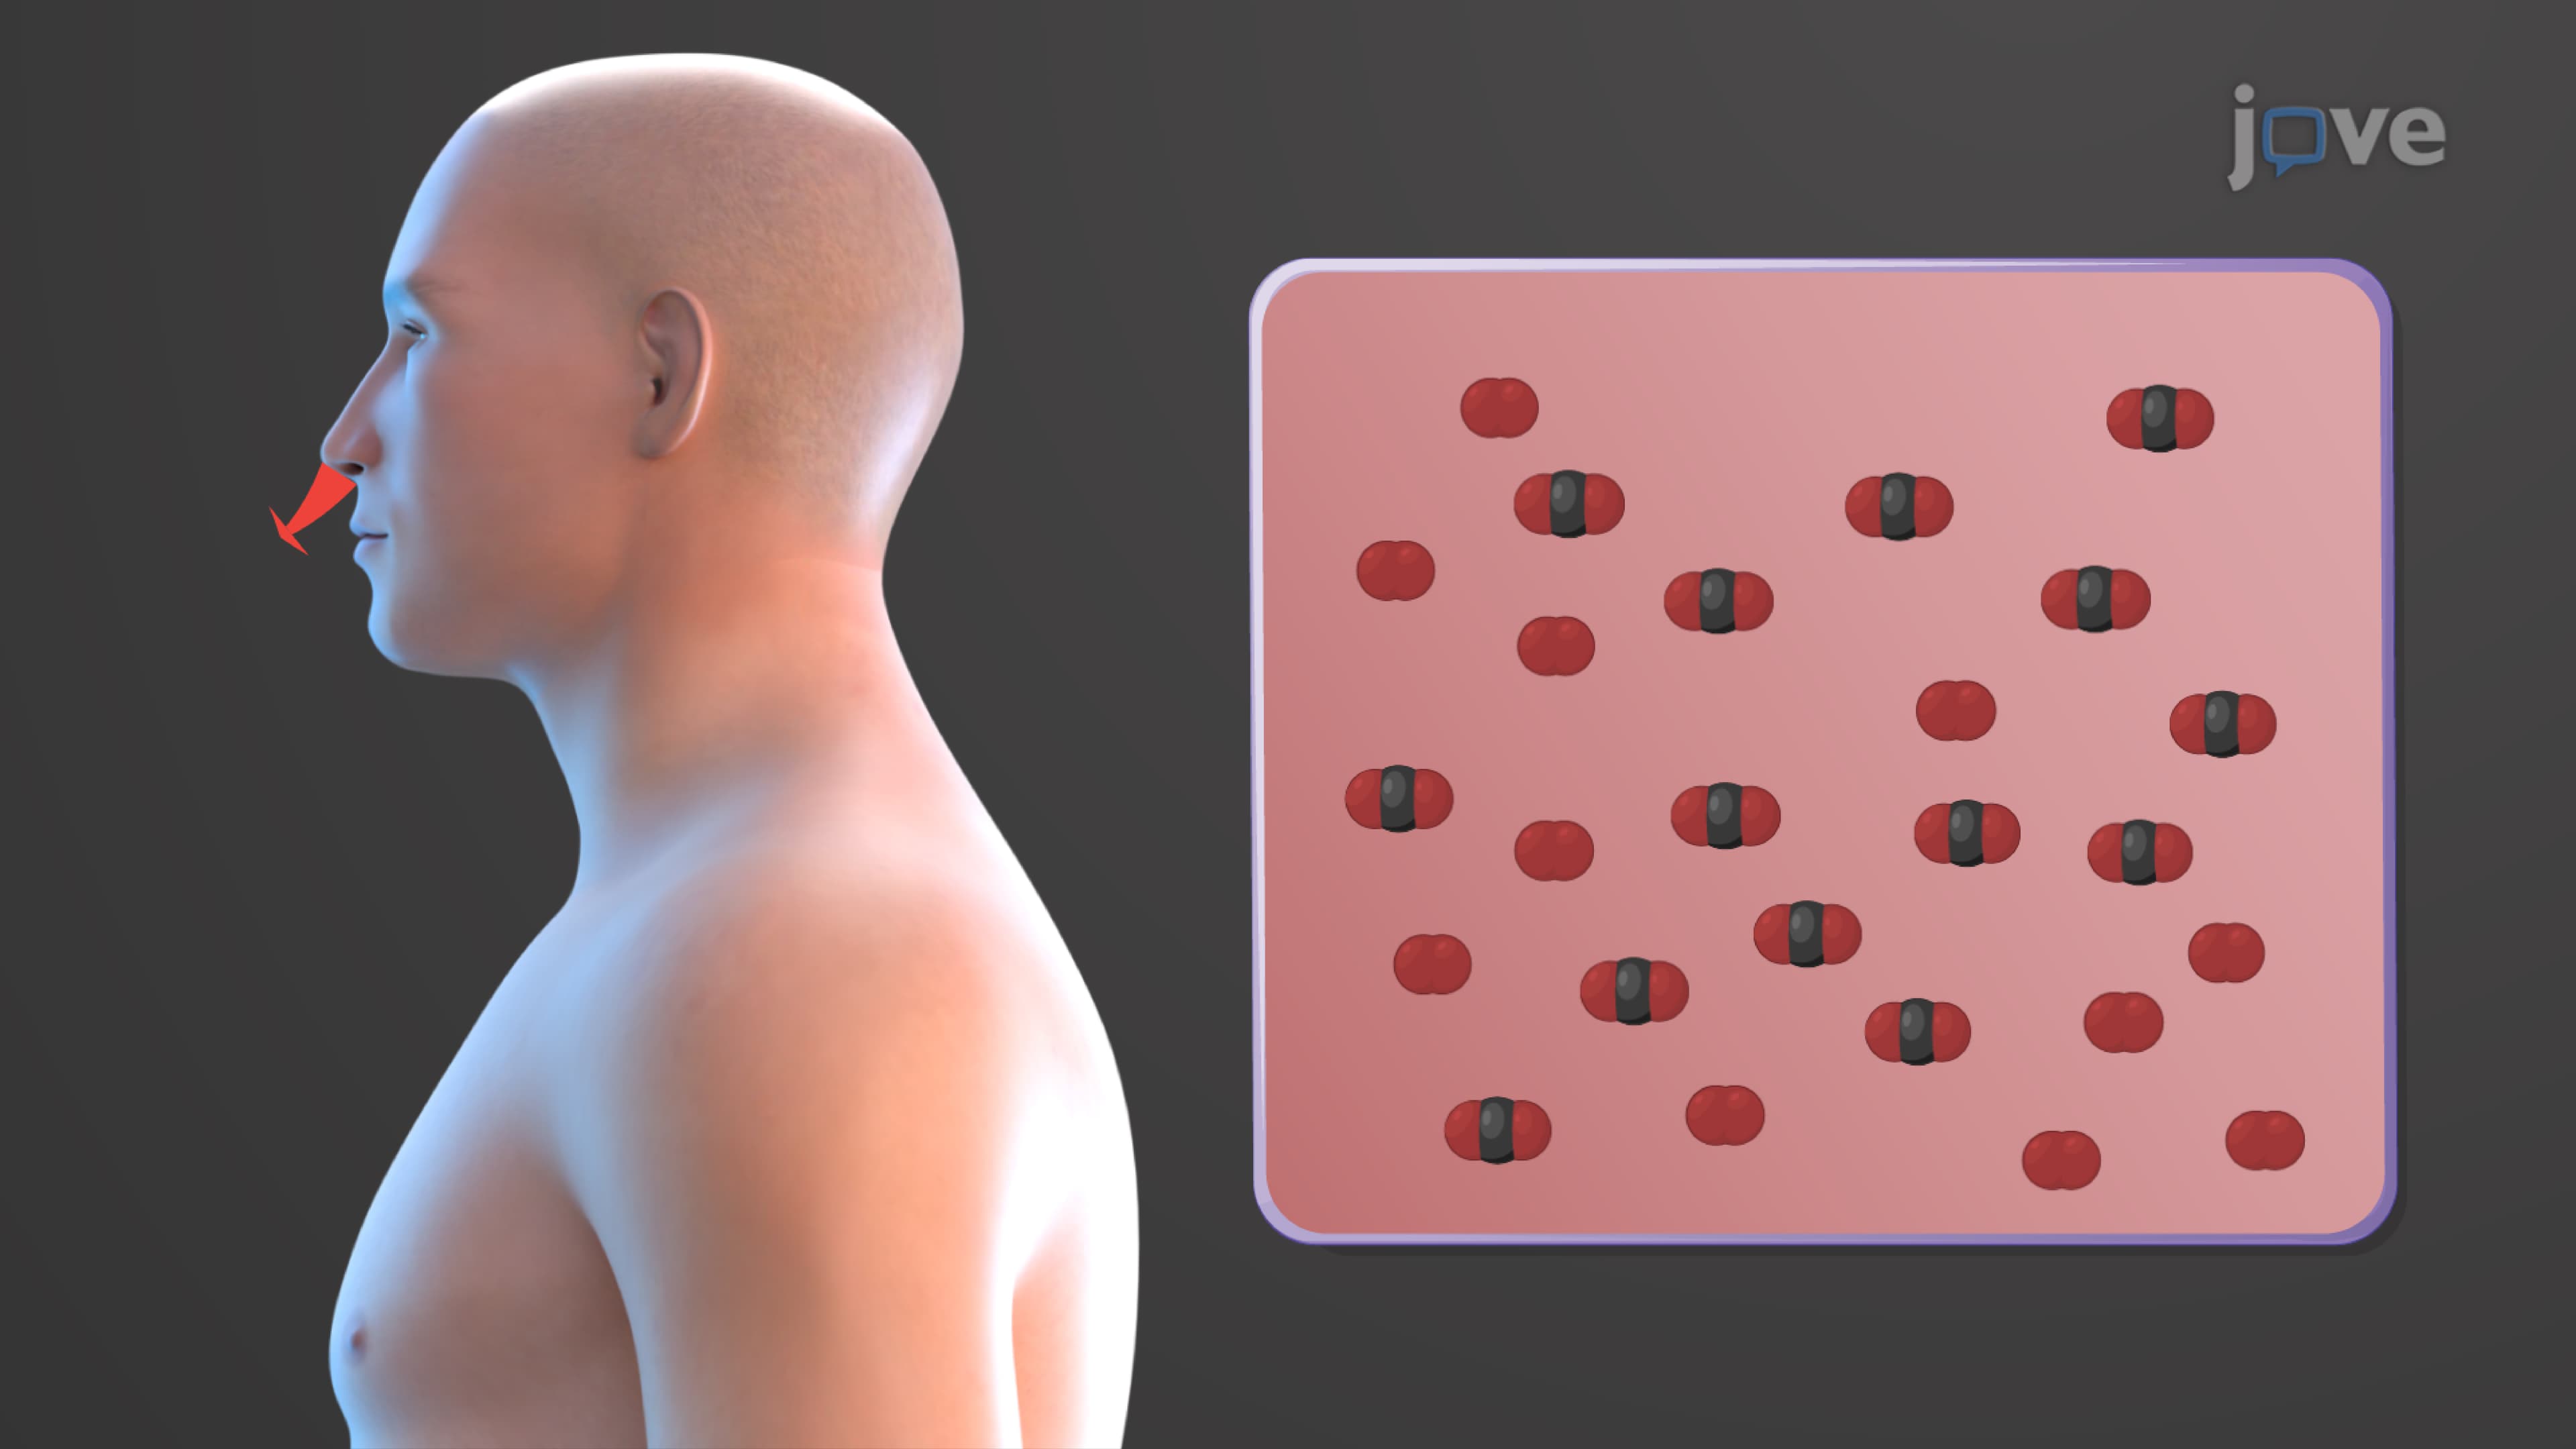
Chemical Factors Affecting Respiration Centers
CO2 has a potent influence on respiration and is strictly regulated....
 01:23
Acute Respiratory Failure-IV
 01:30
Acute Respiratory Failure-III
 01:30
Alterations in Respiration II
In Biot's breathing, the respiratory rate and depth are irregular, alternating between periods of deep gasping and apnea. Common causes...
 01:17
Measurement of Blood Pressure