Related Experiment Video
Updated: Jul 28, 2025
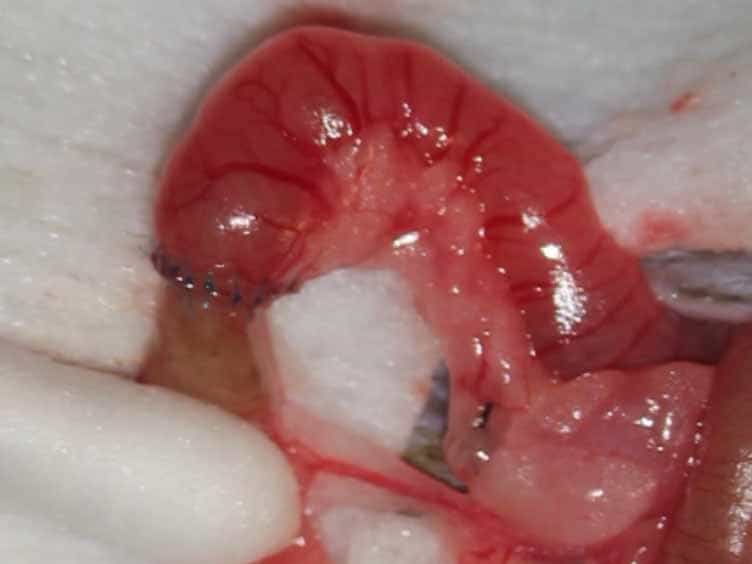
Murine Ileocolic Bowel Resection with Primary Anastomosis
Published on: October 29, 2014
Primary defect of ileal mesentery presenting as internal herniation and strangulation of the small bowel: Case report
Marya Saleem1, Muhammad Haris Janjua1, Muhammad Zeeshan Sarwar1
1Department of Surgery, Mayo Hospital, Lahore, Pakistan.

Insights
Primary internal hernia, a rare cause of intestinal obstruction, can lead to bowel gangrene if diagnosis and treatment are delayed. Prompt surgical intervention, including bowel resection and anastomosis, is crucial for managing this condition.
Area of Science:
- Gastroenterology
- Surgical Pathology
- Abdominal Imaging
Background:
- Primary internal hernia is an uncommon cause of small bowel obstruction.
- Delayed diagnosis and treatment of internal hernias can lead to severe complications like bowel ischemia and gangrene.
- This condition carries significant morbidity and mortality rates if not managed promptly.
Observation:
- A 14-year-old male presented with symptoms of acute intestinal obstruction.
- Surgical exploration revealed a 3-4 cm mesenteric defect in the ileal region.
- Strangulated small bowel loops were found incarcerated within the mesenteric defect.
Findings:
- The patient underwent surgical intervention for the internal hernia.
- Resection of the gangrenous segment of the small bowel was necessary.
- A primary anastomosis was performed following the resection.
Implications:
- Early recognition and surgical management of primary internal hernias are vital to prevent bowel necrosis.
- This case highlights the importance of considering rare causes of intestinal obstruction in pediatric patients.
- Timely surgical repair can significantly reduce the risk of life-threatening complications associated with internal hernias.
Abstract:
Primary internal hernia is a rare entity of acute intestinal obstruction. Delay in diagnosis and surgical intervention can cause ischaemia or gangrene of the small bowel and result in high morbidity and mortality. A 14-year-old boy presented to the emergency department with acute intestinal obstruction. On exploration, 3-4cm mesenteric defect was noted in the ileal region. Strangulated loops of the small bowel had gone through the mesenteric defect in a complicated way. Primary anastomosis was done after resection of the gangrenous small bowel.

Related Concept Videos
 01:27
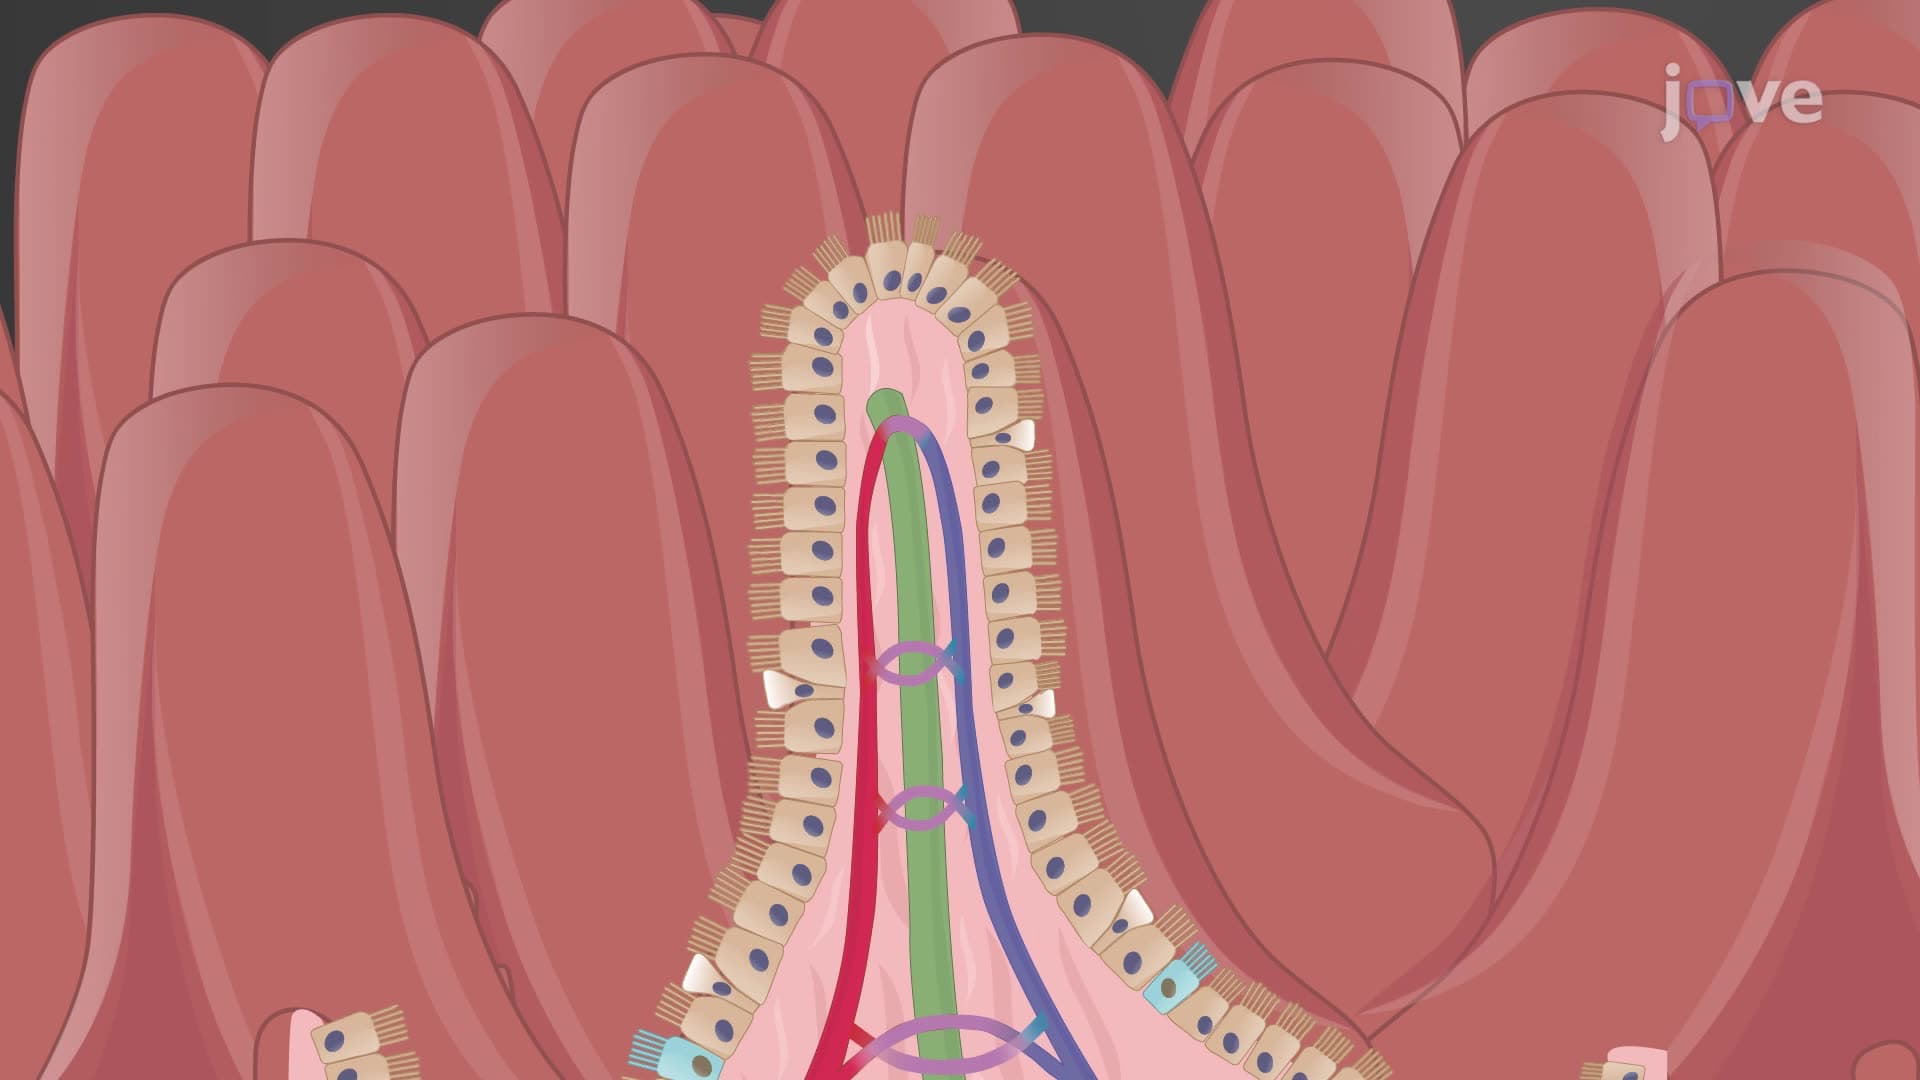
Histology of the Small Intestine
The intestinal lining features transverse folds called circular folds, each housing fingerlike projections known as intestinal villi. These villi are covered by a layer of simple columnar epithelium, also referred to as...
 01:26
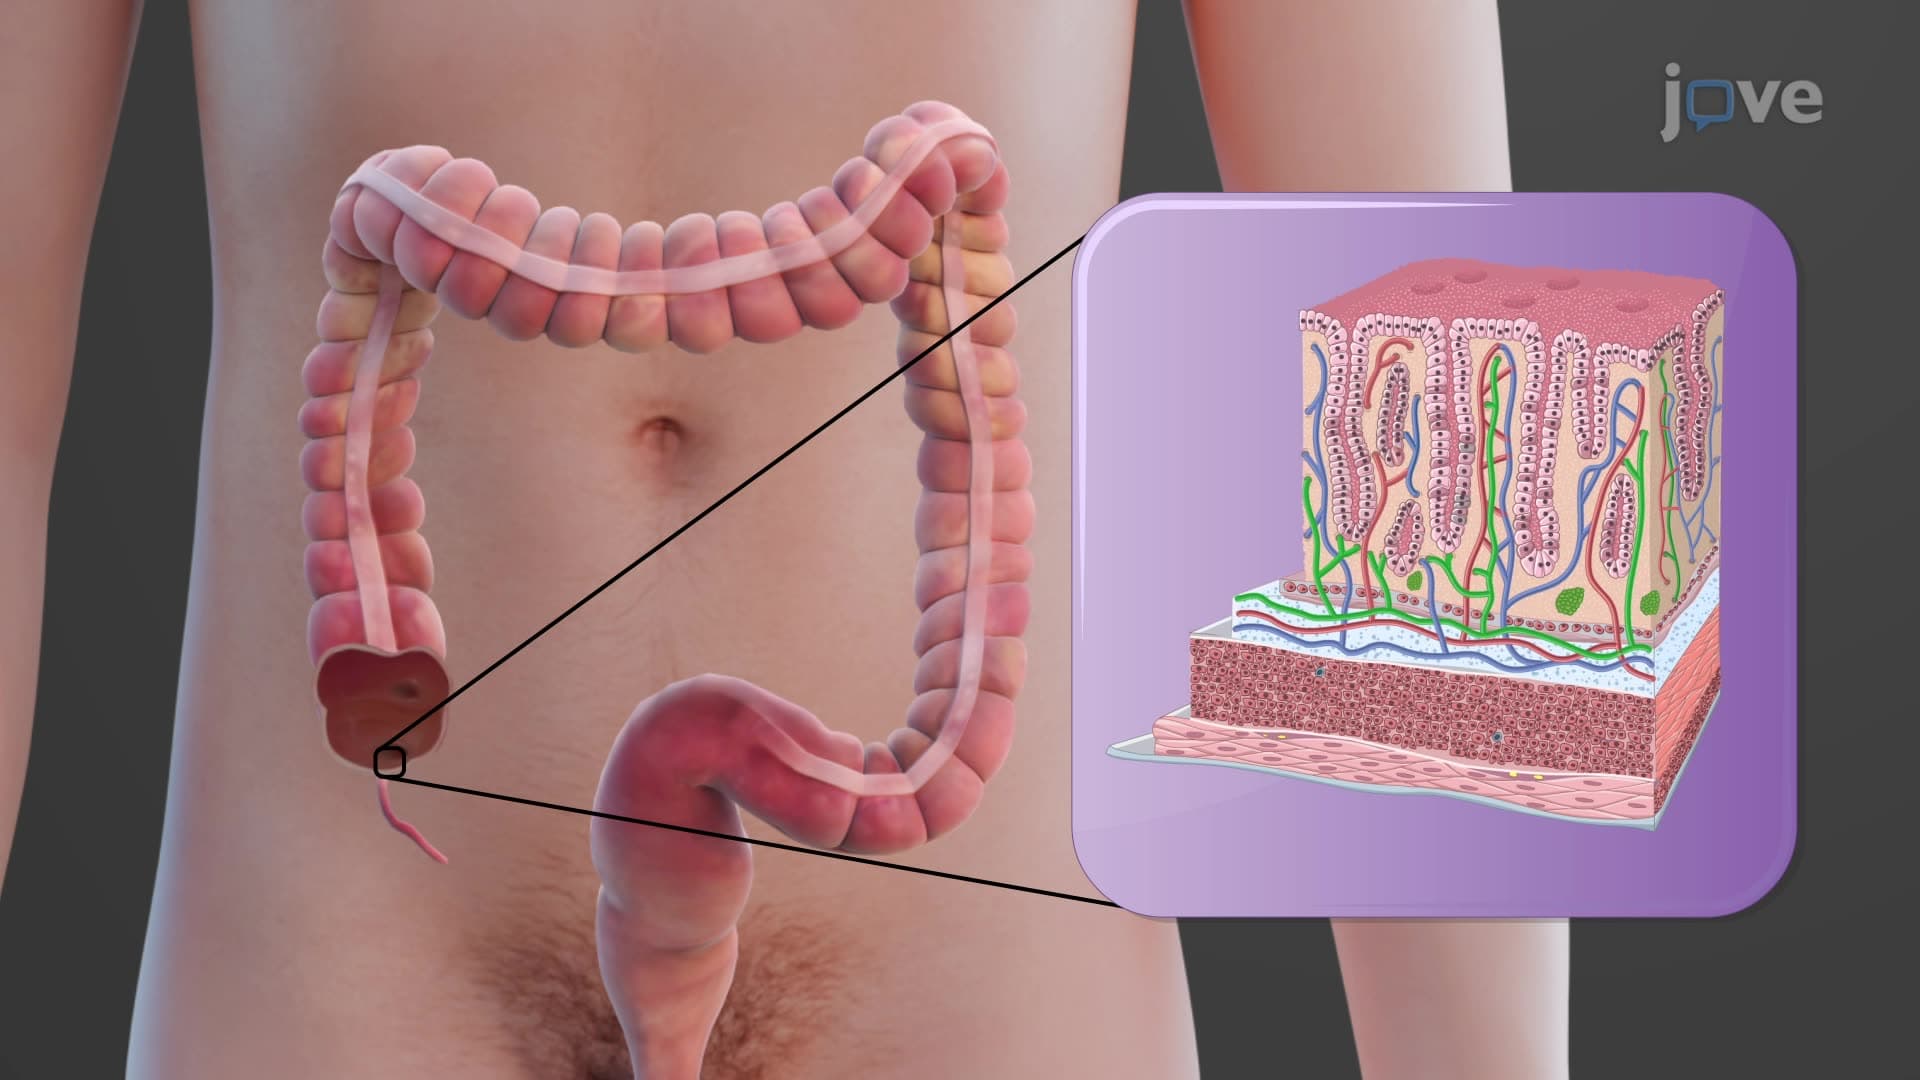
Histology of the Large Intestine
The innermost mucosa layer comprises simple columnar epithelium, lamina propria, and muscularis mucosae. This layer is primarily populated with absorptive cells, tasked with water absorption, and goblet cells, responsible for secreting mucus to...
 01:15
Small Intestine
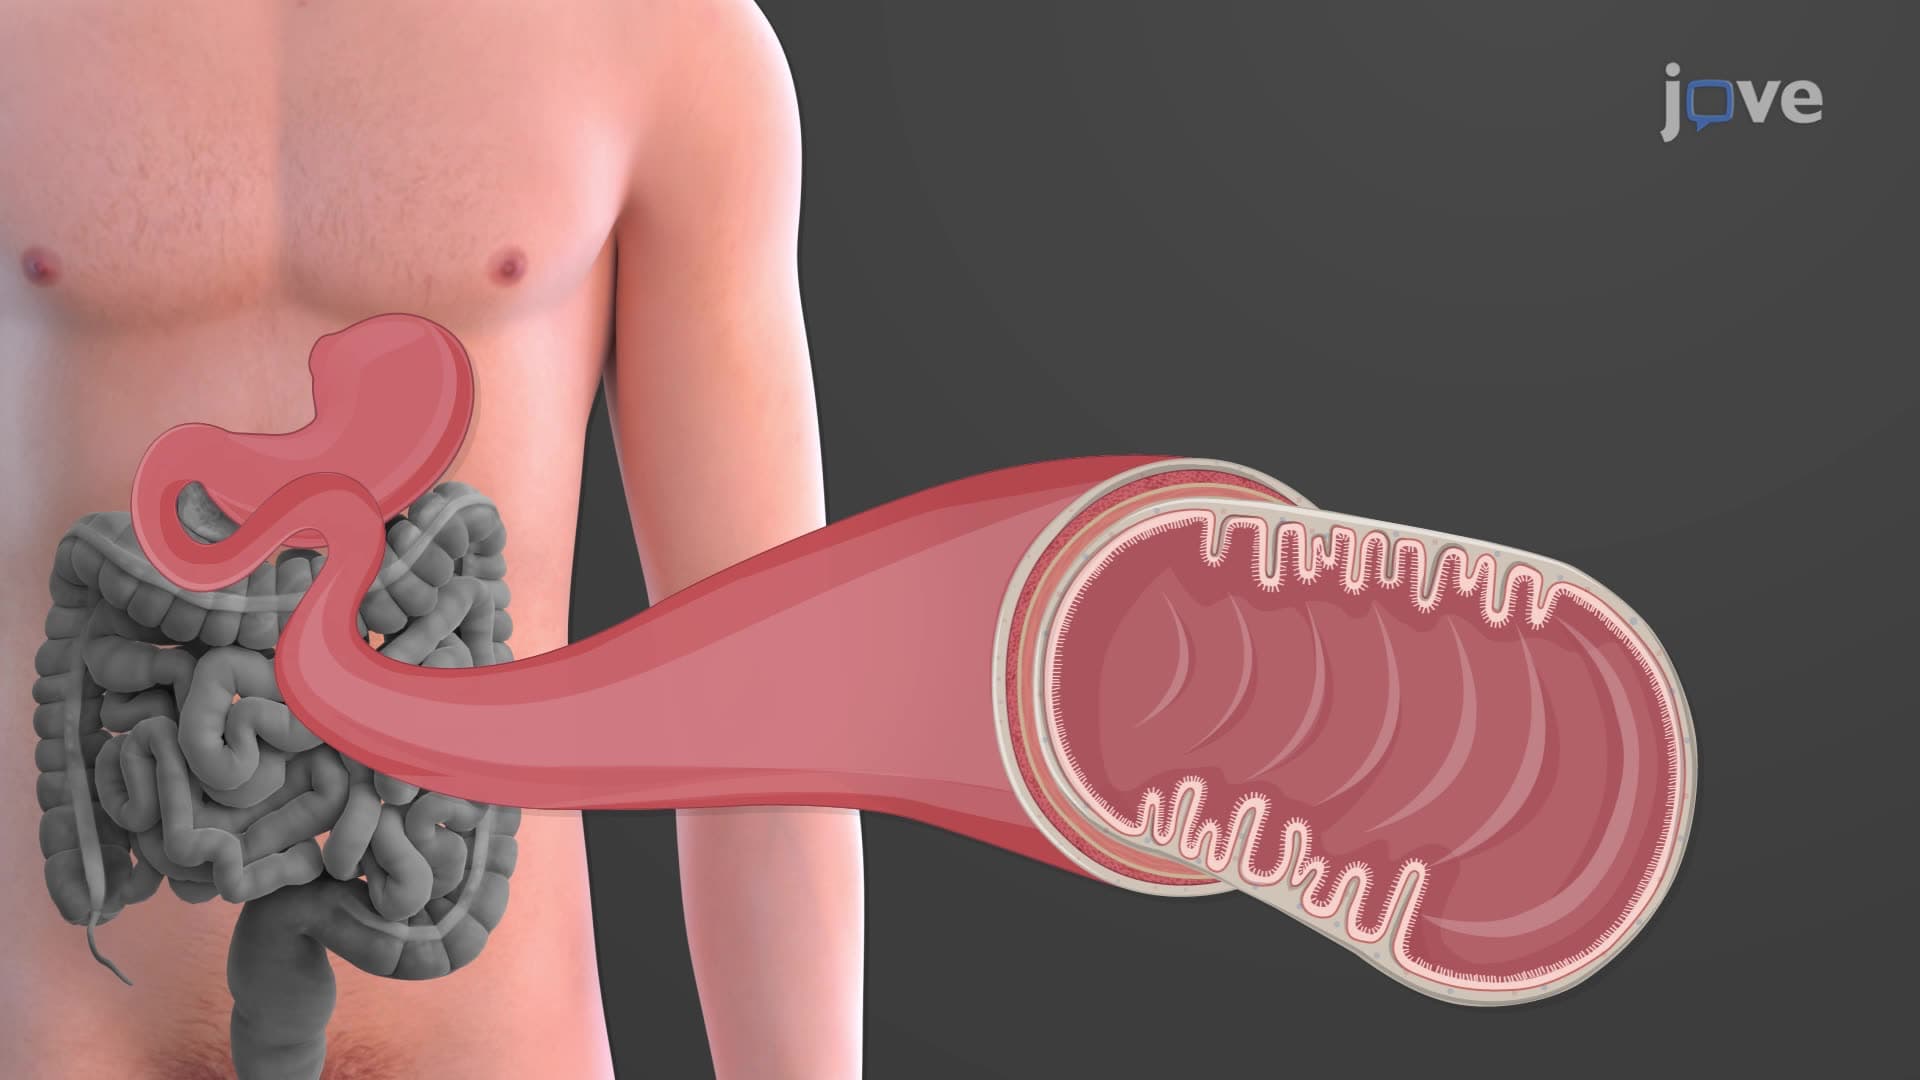
The small intestine is divided into three main sections - the duodenum, jejunum, and ileum. The duodenum, approximately 25 cm long, is nearest the stomach. It acts as a 'mixing bowl,' where chyme (partially digested food) blends with digestive enzymes from the pancreas and liver. The duodenum's unique...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:09
Large Intestine
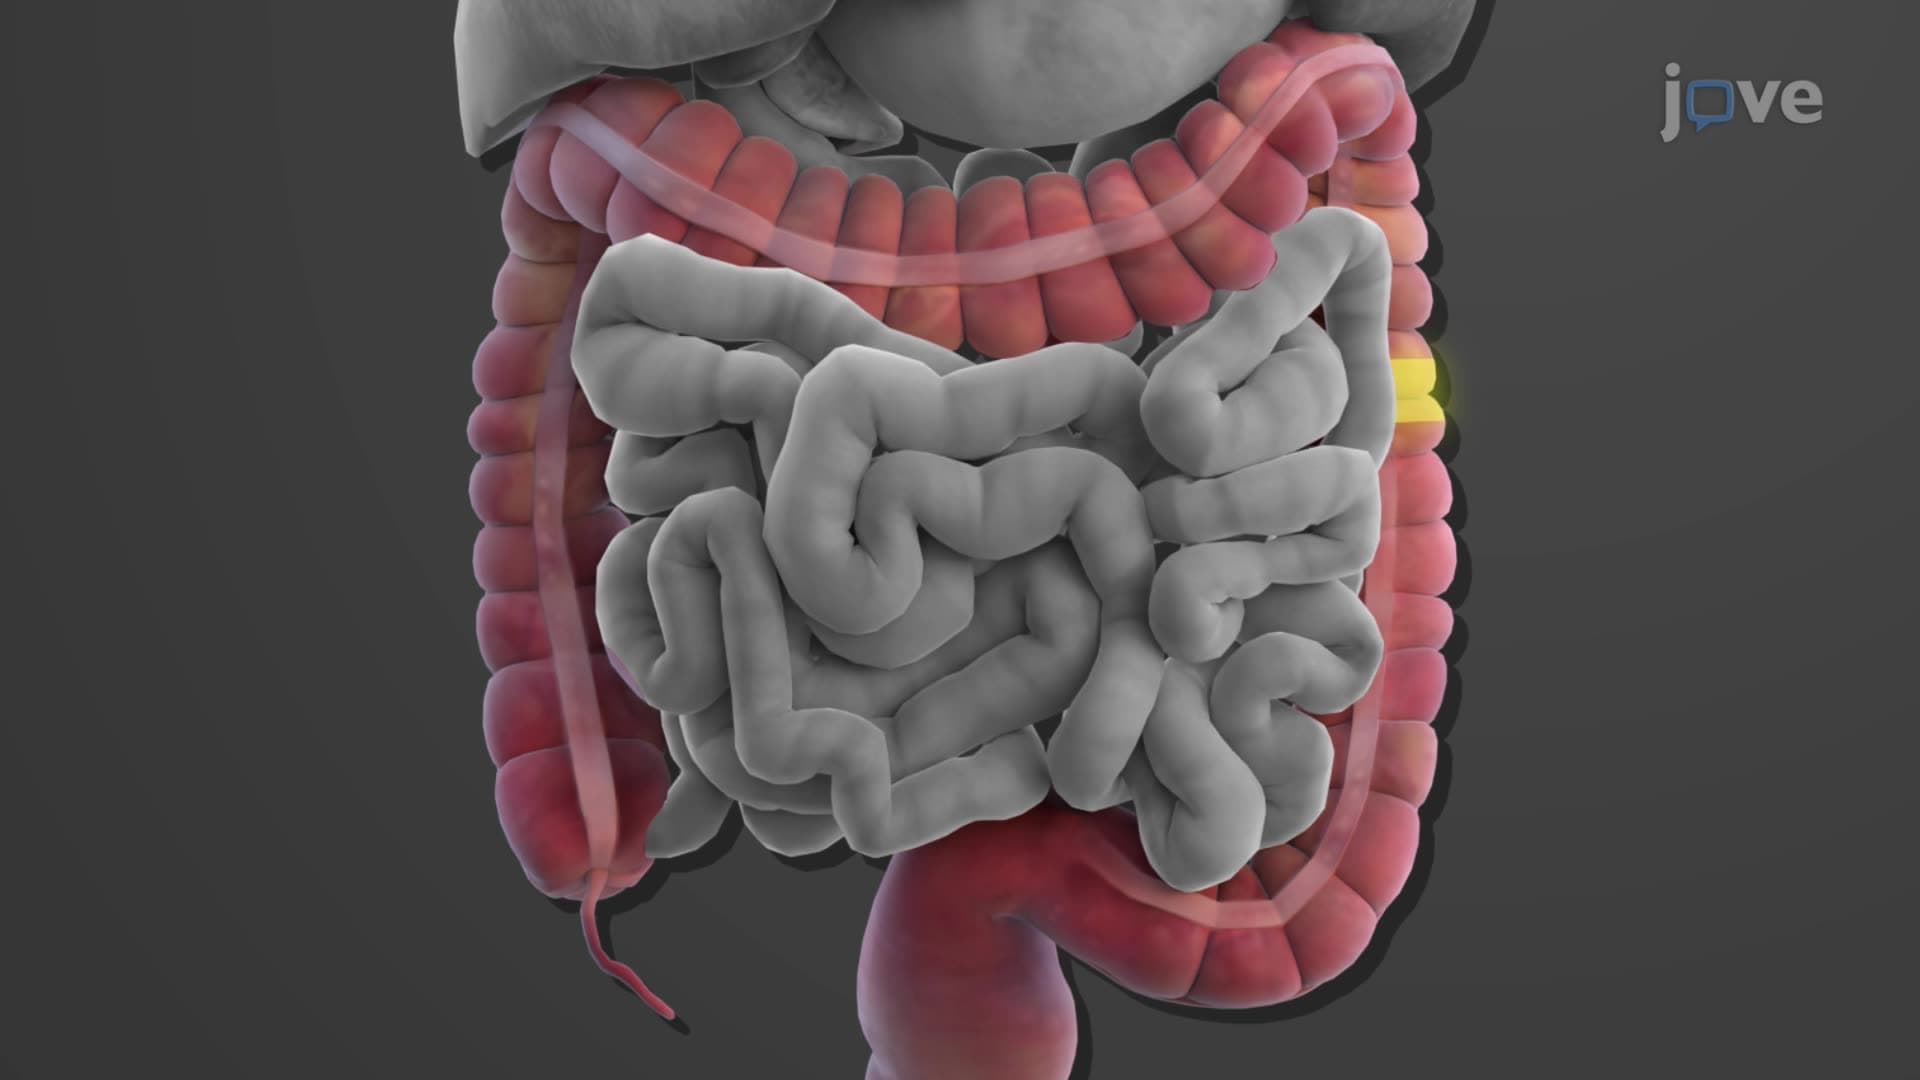
The ileocecal sphincter, a mucous membrane fold, guards the opening from the ileum to the large intestine. This valve permits material from the small intestine to pass into the large intestine. Attached to the ileocecal valve is the cecum. This small pouch, approximately 6 cm long, has a twisted, coiled tube known as...
 01:23
Anatomy of the Intestines
Small Intestines
The small intestine is an ~7 meter-long tube with an inner diameter of just 2.5 cm. Since most nutrients are absorbed here, the inner lining of the...