Related Experiment Video
Updated: Jun 18, 2026

Role of Diffusion MRI Tractography in Endoscopic Endonasal Skull Base Surgery
Published on: July 5, 2021
Cranio-cervical growth collision: another explanation of the Arnold-Chiari malformation and of basilar impression

Abstract:
Analysis of neuro-cranio-spinal development suggests a cranio-cervical growth conflict as the cause of the Arnold-Chiari malformation and of basilar impression. The ascending course and elongation of the upper cervical nerves associated with the Arnold-Chiari malformation reflects the abnormal, caudo-cranially proceeding growth of the cervical spine. This is the opposite of the normal cranio-caudal direction of growth (which includes the brain) with downward slanting of the cervical nerve roots. The cervical growth reversal is a compensatory event related to the impairment of distal spinal growth at the level of the coexistent myelomeningocele. With the reversal of the cerical growth, the initial descent (uncoiling) of the primordial brain curvatures is compromised owing to the growth-collision with the ascending cervical spine. Their subsequent growth proceeds into the upper cervical spinal canal. The contents of the posterior cranial fossa are actively "sucked up", "devoured" by the latter. In contrast to the adaptively enhanced growth of the early cranio-cervical nervous structures in the Arnold-Chiari malformation, as an answer to the growth-shifts of the encasing skeleton, basilar impression is a postembryonic adaptation of the cervico-cranial skeleton to the inadequate growth of the nervous structures after the latter have lost their growth adaptability. Arnold-Chiari malformation and basilar impression are just two representatives of "osteo-neural growth pathology" encompassing some "dysplastic" disorders of the axial as well as of the limb skeleton such as platyspondyly, scoliosis, Scheuermann's kyphosis, achondroplasia-like conditions, congenital dysplasia of the hip etc.(ABSTRACT TRUNCATED AT 250 WORDS)
More Related Videos
 08:27
Development of an Uncomplicated Mild Traumatic Brain Injury Model Modified by Weight-Drop Method and Evidenced by Magnetic Resonance Imaging
Published on: April 11, 2025
 08:03
Midface Hypoplasia and Cranial Base Morphology in Syndromic Craniosynostosis: A Comparative Analysis Study Using a Predictive Regression Model
Published on: November 4, 2025
Related Concept Videos
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:27
Cranial Bones: Lateral View
The temporal bone forms the lower lateral side of the skull. The temporal bone is subdivided into several regions. The flattened upper portion is the squamous portion of the temporal bone. Below this area and projecting anteriorly is the zygomatic process of the temporal bone, which forms the posterior portion of the zygomatic arch. Posteriorly is the mastoid portion of the temporal bone. Projecting...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:19
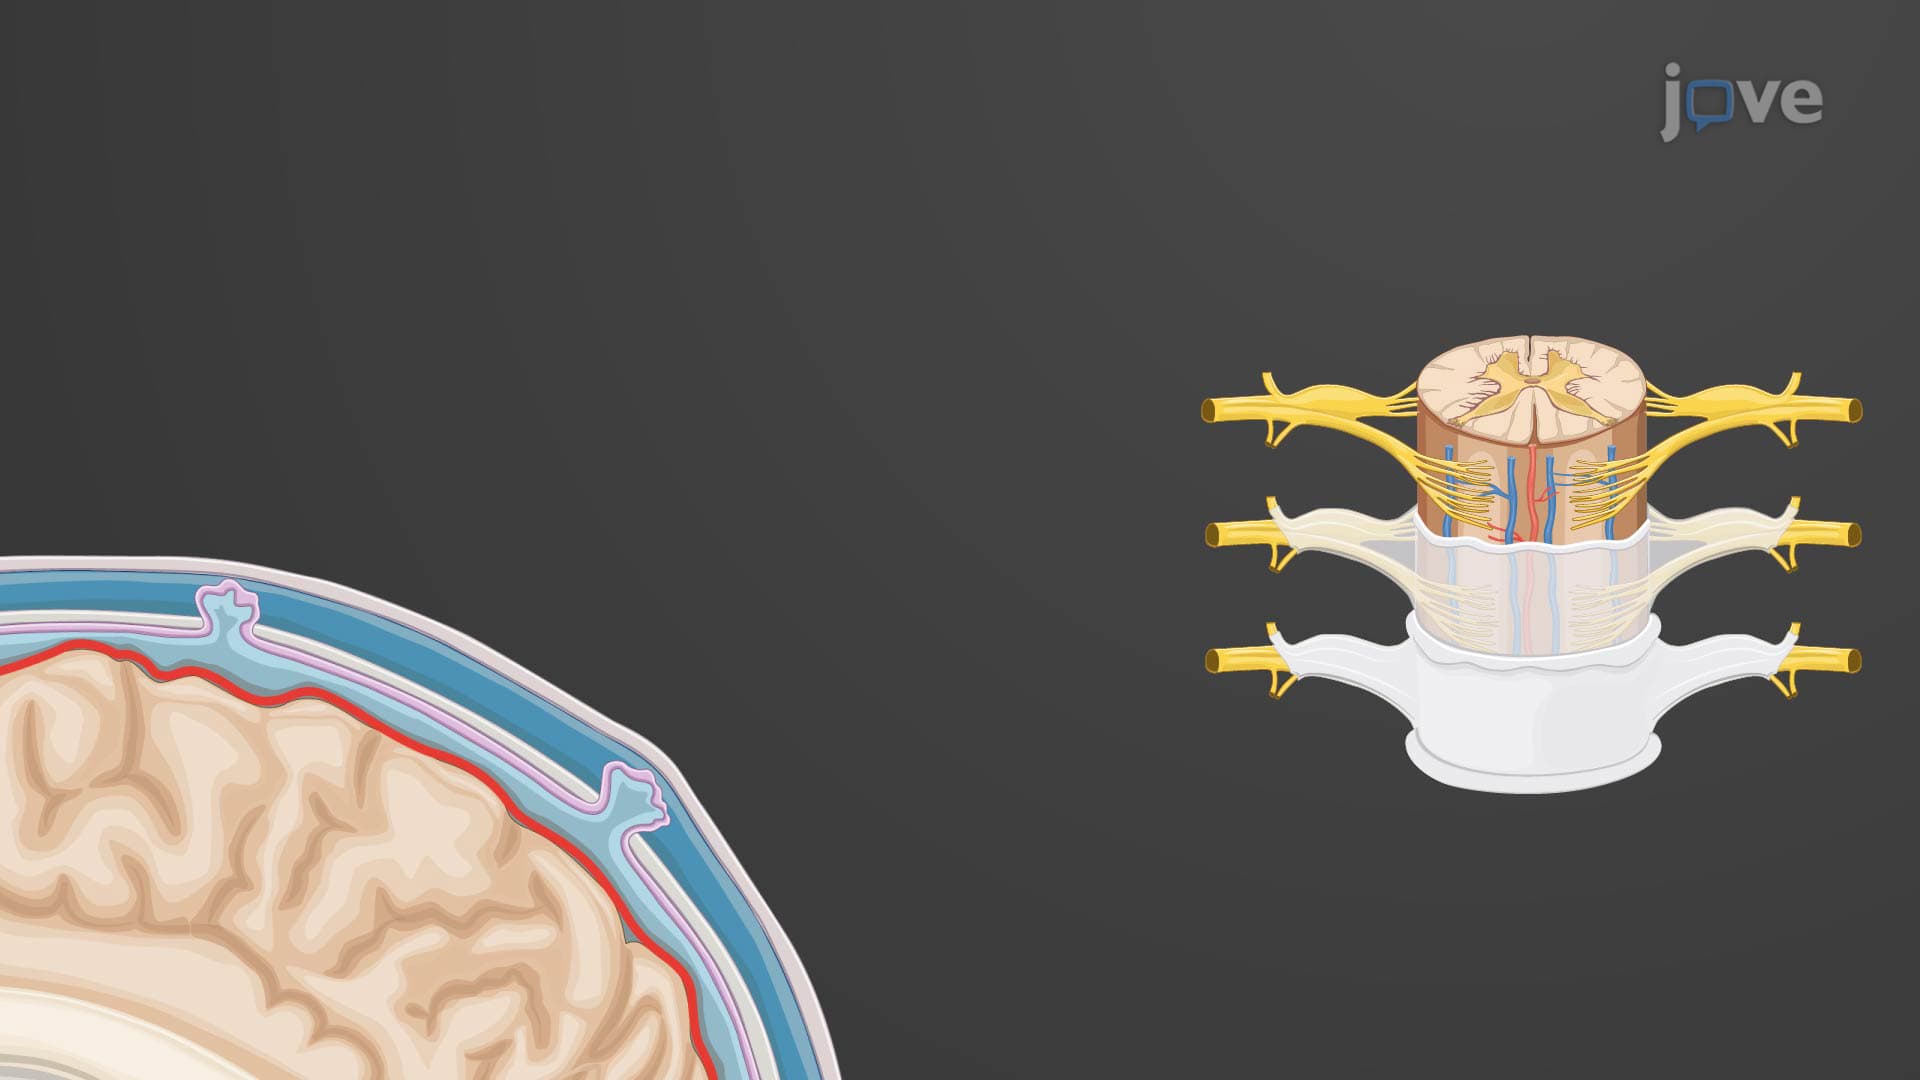
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:14
Increased Intracranial Pressure l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology