Related Experiment Video
Updated: Jul 28, 2025


Primary Outcome Assessment in a Pig Model of Acute Myocardial Infarction
Published on: October 14, 2016
Performance of a prehospital HEART score in patients with possible myocardial infarction: a prospective evaluation
Jamie G Cooper1,2, James Ferguson3, Lorna A Donaldson4
1Emergency Department, Aberdeen Royal Infirmary, Aberdeen, UK jamie.cooper2@nhs.scot.

Insights
Paramedic-derived HEART scores for myocardial infarction risk stratification are not reliable for ruling out the condition. Cardiac troponin testing alone offers better diagnostic accuracy in prehospital settings.
Area of Science:
- Cardiology
- Emergency Medicine
- Prehospital Care
Background:
- The HEART score aids risk stratification for myocardial infarction in the Emergency Department.
- Its utility by paramedics in prehospital settings with high-sensitivity troponin testing remains uncertain.
Purpose of the Study:
- To evaluate the effectiveness of a paramedic-derived HEART score for risk stratification of suspected myocardial infarction.
- To assess its performance in conjunction with prehospital high-sensitivity cardiac troponin testing.
Main Methods:
- A secondary analysis of a prospective cohort study involving paramedics assessing patients with suspected myocardial infarction.
- Paramedic HEAR scores and prehospital blood samples were collected for troponin analysis.
- HEART scores were calculated using contemporary and high-sensitivity troponin assays to define low-risk (≤3) and high-risk (≥7) patients.
Main Results:
- A HEART score of ≤3 had a negative predictive value ranging from 91.4% to 95.9% for major adverse cardiac events (MACEs) at 30 days.
- A modified HEART score using high-sensitivity troponin showed a negative predictive value of 95.9% for low-risk patients.
- A HEART score of ≥7 demonstrated lower positive predictive value compared to troponin assays alone.
Conclusions:
- Paramedic-derived HEART scores, even with modifications for high-sensitivity troponin, do not safely rule out myocardial infarction.
- These scores do not improve rule-in of myocardial infarction compared to troponin testing alone in the prehospital setting.
Introduction:
The History, Electrocardiogram (ECG), Age, Risk Factors and Troponin (HEART) score is commonly used to risk stratify patients with possible myocardial infarction as low risk or high risk in the Emergency Department (ED). Whether the HEART score can be used by paramedics to guide care were high-sensitivity cardiac troponin testing available in a prehospital setting is uncertain.
Methods:
In a prespecified secondary analysis of a prospective cohort study where paramedics enrolled patients with suspected myocardial infarction, a paramedic Heart, ECG, Age, Risk Factors (HEAR) score was recorded contemporaneously, and a prehospital blood sample was obtained for subsequent cardiac troponin testing. HEART and modified HEART scores were derived using laboratory contemporary and high-sensitivity cardiac troponin I assays. HEART and modified HEART scores of ≤3 and ≥7 were applied to define low-risk and high-risk patients, and performance was evaluated for an outcome of major adverse cardiac events (MACEs) at 30 days.
Results:
Between November 2014 and April 2018, 1054 patients were recruited, of whom 960 (mean 64 (SD 15) years, 42% women) were eligible for analysis and 255 (26%) experienced a MACE at 30 days. A HEART score of ≤3 identified 279 (29%) as low risk with a negative predictive value of 93.5% (95% CI 90.0% to 95.9%) for the contemporary assay and 91.4% (95% CI 87.5% to 94.2%) for the high-sensitivity assay. A modified HEART score of ≤3 using the limit of detection of the high-sensitivity assay identified 194 (20%) patients as low risk with a negative predictive value of 95.9% (95% CI 92.1% to 97.9%). A HEART score of ≥7 using either assay gave a lower positive predictive value than using the upper reference limit of either cardiac troponin assay alone.
Conclusions:
A HEART score derived by paramedics in the prehospital setting, even when modified to harness the precision of a high-sensitivity assay, does not allow safe rule-out of myocardial infarction or enhanced rule-in compared with cardiac troponin testing alone.
More Related Videos
 18:11
A Research Method For Detecting Transient Myocardial Ischemia In Patients With Suspected Acute Coronary Syndrome Using Continuous ST-segment Analysis
Published on: December 28, 2012
 08:19
Transthoracic Echocardiography to Assess Post-Resuscitation Left Ventricular Dysfunction After Acute Myocardial Infarction and Cardiac Arrest in Pigs
Published on: July 12, 2022
Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:26
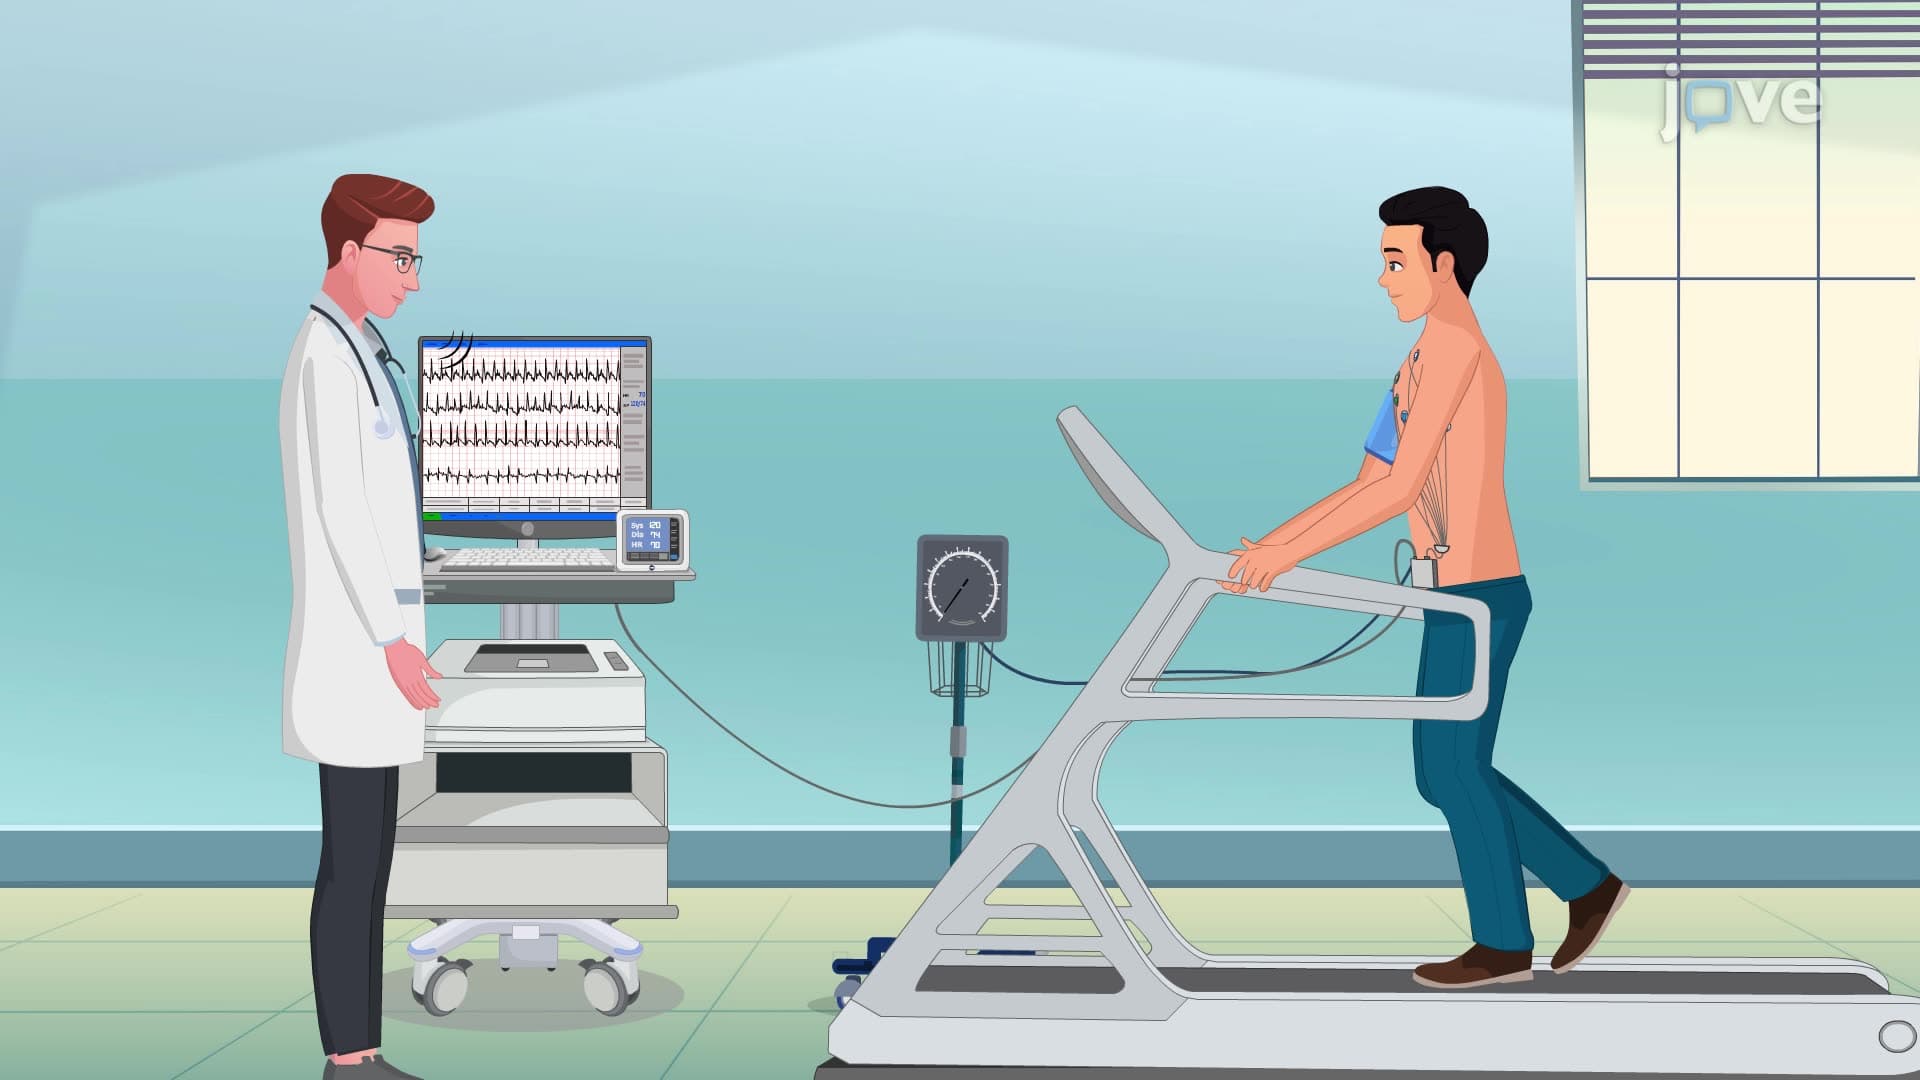
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:30
Acute Coronary Syndrome I: Introduction
 01:20
Blood Studies for Cardiovascular System I: Cardiac Biomarkers
The essential diagnostic tools for detecting myocardial necrosis and monitoring individuals suspected of having acute coronary syndrome (ACS) include:
Troponins
Troponins, particularly cardiac troponins I and T, are the most precise and sensitive markers of myocardial injury. They are detectable within 4-6 hours of myocardial injury and remain...
 01:21
Cardiopulmonary Resuscitation I: Adult