Related Experiment Video
Updated: Jul 27, 2025
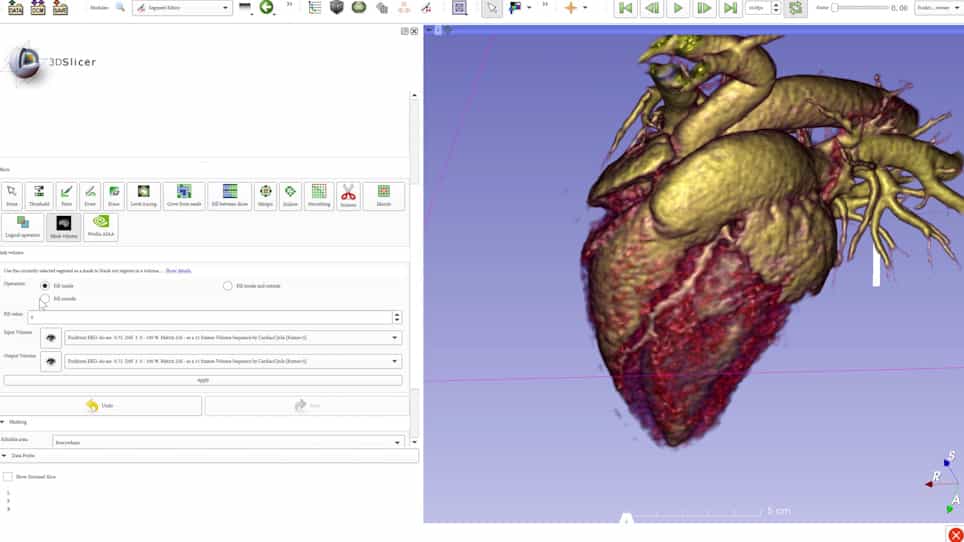
Four-Dimensional Computed Tomography-Guided Valve Sizing for Transcatheter Pulmonary Valve Replacement
Published on: January 20, 2022
Analysis of Cardiac Computed Tomography Anatomy in Patients With Severe Tricuspid Regurgitation Considered for
Brenden S Ingraham1, Kathleen A Young1, Prajwal Reddy1
1Department of Cardiovascular Medicine, Mayo Clinic, Rochester, Minnesota, USA.

Background:
Severe tricuspid regurgitation (TR) is associated with considerable morbidity/mortality in an elderly population with multiple comorbidities. There is interest in transcatheter interventions to manage severe TR. Understanding complex right heart (RH) geometry and tricuspid valve shape and size has implications for patient/device selection for transcatheter intervention. We characterized RH anatomy by computed tomography in patients with symptomatic severe TR considered for intervention.
Methods:
The retrospective Mayo Clinic study included 29 patients with an echocardiogram and cardiac computed tomography angiogram considered for intervention of severe TR from March 01, 2016 to December 15, 2020. Patients were divided into 2 groups: intervention (surgical or transcatheter; n = 17) and medical management alone (n = 12).
Results:
Mean age was 83 ± 8 (83% female), 100% had atrial fibrillation, and 62% had chronic kidney disease ≥3a. Ninety-seven percent were symptomatic, 93% had been prescribed loop diuretics, and 24% had device leads. Mean tricuspid annular plane systolic excursion was 16.8 ± 4.5 mm, effective regurgitant orifice area was 81 ± 33 mm2, and cardiac index was 2.6 ± 0.6 L/min/m2. Forty-one percent had at least moderate right ventricular (RV) dysfunction with a mean RV systolic pressure of 46 ± 16 mmHg. Patients receiving intervention had significantly larger effective regurgitant orifice area (101 ± 33 vs. 63 ± 22 mm2, p = 0.033), shorter tricuspid leaflet tenting length (6.5 ± 3.0 vs. 8.9 ± 2.7 mm, p = 0.042), and smaller annuloplasty diagnostic perimeter during diastole (120.1 ± 16.6 vs. 131.1 ± 7.4 mm, p = 0.041). Intervention patients tended to have better right ventricular function, smaller RV and inferior vena cava size, and more severe symptoms. The maximal tricuspid annulus diameter in systole and diastole was 51 ± 5 and 53 ± 7 mm, respectively.
Conclusions:
Severe TR patients referred for transcatheter intervention present with severe RH enlargement with a large proportion having tricuspid annulus dimensions outside the range for current devices available in clinical trials. The presented data have implications for device development/selection and procedural feasibility.
More Related Videos

Related Concept Videos
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:25
Mitral Regurgitation III: Medical Management
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:15
Aortic Regurgitation I: Introduction
 01:25
Aortic Regurgitation III: Medical Management