Related Experiment Video
Updated: Jul 27, 2025
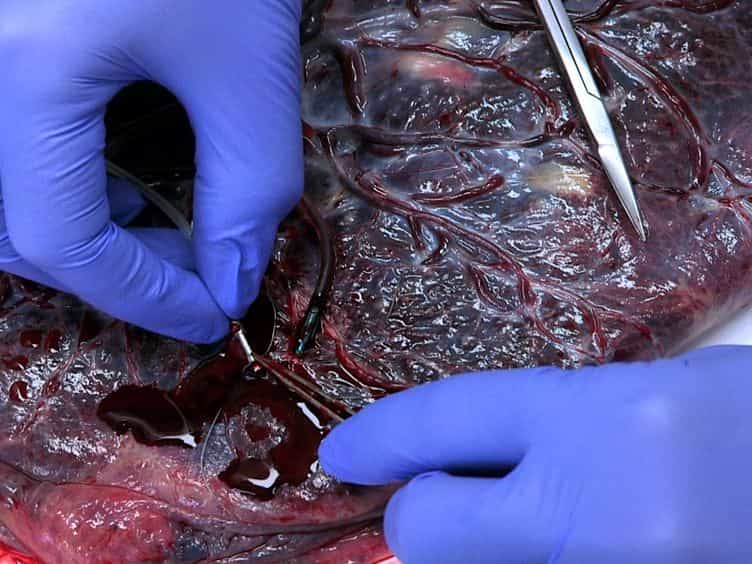

Determination of the Transport Rate of Xenobiotics and Nanomaterials Across the Placenta using the ex vivo Human Placental Perfusion Model
Published on: June 18, 2013
Understanding the Mechanism and Extent of Transplacental Transfer of (-)-∆
Aditya R Kumar1, Emily D Sheikh2, Joshua W Monson2
1Department of Pharmaceutics, University of Washington, Seattle, Washington, USA.

Cannabis use during pregnancy may cause fetal toxicity driven by in utero exposure to (-)-∆9 -tetrahydrocannabinol (THC) and its psychoactive metabolite, (±)-11-hydroxy-∆9 -THC (11-OH-THC). THC concentrations in the human term fetal plasma appear to be lower than the corresponding maternal concentrations. Therefore, we investigated whether THC and its metabolites are effluxed by placental transporters using the dual cotyledon, dual perfusion, term human placenta. The perfusates contained THC alone (5 μM) or in combination (100-250 nM) with its metabolites (100 nM or 250 nM 11-OH-THC, 100 nM COOH-THC), plus a marker of P-glycoprotein (P-gp) efflux (1 or 10 μM saquinavir), and a passive diffusion marker (106 μM antipyrine). All perfusions were conducted with (n = 7) or without (n = 16) a P-gp/BCRP (breast-cancer resistance protein) inhibitor, 4 μM valspodar. The maternal-fetal and fetal-maternal unbound cotyledon clearance indexes (m-f-CLu,c,i and f-m-CLu,c,i ) were normalized for transplacental antipyrine clearance. At 5 μM THC, the m-f-CLu,c,i , 5.1 ± 2.1, was significantly lower than the f-m-CLu,c,i , 13 ± 6.1 (P = 0.004). This difference remained in the presence of valspodar or when the lower THC concentrations were perfused. In contrast, neither metabolite, 11-OH-THC/COOH-THC, had significantly different m-f-CLu,c,i vs. f-m-CLu,c,i . Therefore, THC appears to be effluxed by placental transporter(s) not inhibitable by the P-gp/BCRP antagonist, valspodar, while 11-OH-THC and COOH-THC appear to passively diffuse across the placenta. These findings plus our previously quantified human fetal liver clearance, extrapolated to in vivo, yielded a THC fetal/maternal steady-state plasma concentration ratio of 0.28 ± 0.09, comparable to that observed in vivo, 0.26 ± 0.10.
Cannabis use during pregnancy may cause fetal toxicity driven by in utero exposure to (-)-∆9 -tetrahydrocannabinol (THC) and its psychoactive metabolite, (±)-11-hydroxy-∆9 -THC (11-OH-THC). THC concentrations in the human term fetal plasma appear to be lower than the corresponding maternal concentrations. Therefore, we investigated whether THC and its metabolites are effluxed by placental transporters using the dual cotyledon, dual perfusion, term human placenta. The perfusates contained THC alone (5 μM) or in combination (100-250 nM) with its metabolites (100 nM or 250 nM 11-OH-THC, 100 nM COOH-THC), plus a marker of P-glycoprotein (P-gp) efflux (1 or 10 μM saquinavir), and a passive diffusion marker (106 μM antipyrine). All perfusions were conducted with (n = 7) or without (n = 16) a P-gp/BCRP (breast-cancer resistance protein) inhibitor, 4 μM valspodar. The maternal-fetal and fetal-maternal unbound cotyledon clearance indexes (m-f-CLu,c,i and f-m-CLu,c,i ) were normalized for transplacental antipyrine clearance. At 5 μM THC, the m-f-CLu,c,i , 5.1 ± 2.1, was significantly lower than the f-m-CLu,c,i , 13 ± 6.1 (P = 0.004). This difference remained in the presence of valspodar or when the lower THC concentrations were perfused. In contrast, neither metabolite, 11-OH-THC/COOH-THC, had significantly different m-f-CLu,c,i vs. f-m-CLu,c,i . Therefore, THC appears to be effluxed by placental transporter(s) not inhibitable by the P-gp/BCRP antagonist, valspodar, while 11-OH-THC and COOH-THC appear to passively diffuse across the placenta. These findings plus our previously quantified human fetal liver clearance, extrapolated to in vivo, yielded a THC fetal/maternal steady-state plasma concentration ratio of 0.28 ± 0.09, comparable to that observed in vivo, 0.26 ± 0.10.

Related Concept Videos
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:25
Physiological Barriers
The blood endothelial barrier is the most porous of these. It allows all small ionized, un-ionized, and lipophilic molecules to pass through the endothelial lining into the interstitial space...
 01:23
Factors Affecting Drug Distribution: Physiological Barriers
The capillary endothelial barrier allows only smaller molecules below 600 Da (Daltons) to pass through. It also restricts drugs like heparin that are bound to blood components, limiting their movement within the bloodstream.
The...