Related Experiment Video
Updated: Jul 27, 2025
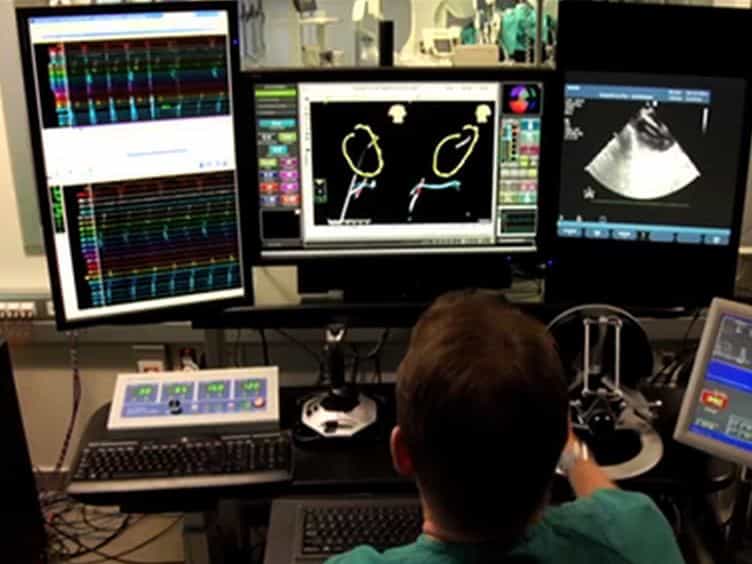

Remote Magnetic Navigation for Accurate, Real-time Catheter Positioning and Ablation in Cardiac Electrophysiology Procedures
Published on: April 21, 2013
Worldwide Experience With an Irrigated Needle Catheter for Ablation of Refractory Ventricular Arrhythmias: Final
Usha B Tedrow1, Masaaki Kurata2, Iwanari Kawamura3
1Cardiovascular Division, Department of Medicine, Brigham and Women's Hospital, Boston, Massachusetts, USA.

Background:
We previously reported feasibility of irrigated needle ablation (INA) with a retractable 27-G end-hole needle catheter to treat nonendocardial ventricular arrhythmia substrate, an important cause of ablation failure.
Objectives:
The purpose of this study was to report outcomes and complications in our entire INA-treated population.
Methods:
Patients with recurrent sustained monomorphic ventricular tachycardia (VT) or high-density premature ventricular contractions (PVCs) despite radiofrequency ablation were prospectively enrolled at 4 centers. Endpoints included a 70% decrease in VT frequency or PVC burden decrease to <5,000/24 h at 6 months.
Results:
INA was performed in 111 patients (median: 2 failed prior ablations, 71% nonischemic heart disease, and left ventricular ejection fraction 36% ± 14%). INA acutely abolished targeted PVCs in 33 of 37 patients (89%), and PVCs were reduced to <5,000/day in 29 patients (78%). During 6-month follow-up, freedom from hospitalization was observed in 50 of 72 patients with VT (69%), and improvement or abolition of VT occurred in 47%. All patients received multiple INA applications, with more in the VT group than in the PVC group (median: 12 [IQR: 7-19] vs 7 [5-15]; P < 0.01). After INA, additional endocardial standard radiofrequency ablation was required in 23% of patients. Adverse events included 4 pericardial effusions (3.5%), 3 cases of (anticipated) atrioventricular block (2.6%), and 3 heart failure exacerbations (2.6%). During 6-month follow-up, 5 deaths occurred; none were procedure-related.
Conclusions:
INA achieves improved arrhythmia control in 78% of patients with PVCs and avoids hospitalization in 69% of patients with VT refractory to standard ablation at 6-month follow-up. Procedural risks are acceptable. (Intramural Needle Ablation for Ablation of Recurrent Ventricular Tachycardia, NCT01791543; Intramural Needle Ablation for the Treatment of Refractory Ventricular Arrhythmias, NCT03204981).
More Related Videos
 28:13
Catheter Ablation in Combination With Left Atrial Appendage Closure for Atrial Fibrillation
Published on: February 26, 2013
 06:57
Ablation of Ischemic Ventricular Tachycardia Using a Multipolar Catheter and 3-dimensional Mapping System for High-density Electro-anatomical Reconstruction
Published on: January 31, 2019
Related Concept Videos
 01:24
Cardiac Catheterization III: Left Heart Catheterization
 01:28
Cardiac Catheterization I: Pre-Procedure Overview
 01:21
Cardiac Catheterization II: Right Heart Catheterization
 01:26
Cardiac Catheterization IV: Nursing Management
 01:25
Hemodialysis I: Introduction