Related Experiment Video
Updated: Jul 27, 2025
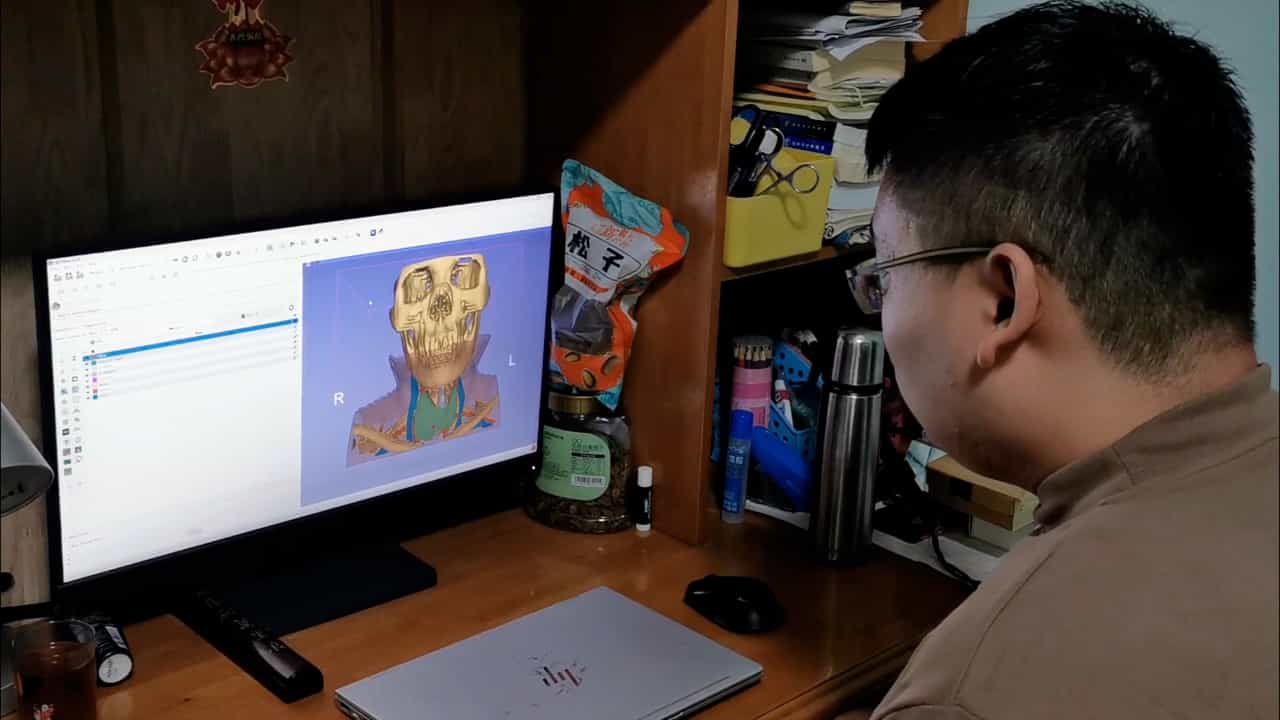

Mixed Reality Assisted Radical Endoscopic Thyroidectomy
Published on: January 31, 2025
Delayed respiratory distress after thyroidectomy-another challenge for us: a case report
Maya Belitova1, Todor Popov2, Tsvetomir Marinov1
1Department of Anesthesiology and ICU, University Hospital "Queen Giovanna-ISUL", Medical University of Sofia, Sofia, Bulgaria.

Background:
Delayed airway obstruction and the resulting severe dyspnea with acute distress are rare but life-threatening postoperative thyroidectomy complications. Unfortunately, if not adequately attended to on time, they could cost a patient's life.
Case Description:
A 47-year-old female patient who underwent thyroidectomy was left at the end of surgery with a tracheostomy, because of tracheomalacia and recurrent laryngeal nerve injury. Within the next ten days, her health condition gradually worsened. She complained of unexpected symptoms of shortness of breath, airway compromize and neck inflammation even with the existing tracheostomy tube. In face of new onset dyspnea, without giving proper attention to the postoperative course of this complicated patient, the consulting otorhinolaryngologist decided to decannulate the patient on the sixth postoperative day. This precipitated the presentation of an extensive neck infection with resultant total bilateral vocal fold immobility, followed by life-threatening airway obstruction, due to an unintentionally forgotten gauze in peritracheal space during thyroidectomy. In critical condition, the patient was successfully intubated with Rapid Sequence Induction, which enabled ventilation, oxygenation and saved the patient's life. After definitively securing the airway, she underwent tracheostomy with tracheal re-cannulation. After a prolonged antimicrobial course and achieving voice rehabilitation, the patient was decannulated.
Conclusions:
Post thyroidectomy dyspnea is possible even with tracheostomy in place. The decision-making in the management of a thyroidectomy patient is of paramount importance not only intraoperatively, but also in the postoperative period and the gland surgeon expertise is of supreme value for avoiding life-threatening complications. In case of postoperative complaints, the patient should be referred first to the gland surgeon and only thereafter to other medical consultants. Disregarding a variety of factors like patient characteristics, risk factors and comorbidity, available diagnostic tools and specific recovery profile could cost the patient's life.

Related Concept Videos
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals....
 01:23
Acute Respiratory Failure-IV
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:17
Endotracheal Intubation II: Nursing Management
1. Nursing Care of Patients Before Intubation
Before the endotracheal intubation procedure, nurses play an essential role in ensuring the process goes smoothly. The nurses must be familiar with intubation...
 01:15
Endotracheal Intubation I: Procedure
The ET tube comprises various components, including a standard adaptor to attach a bag-valve-mask (BVM) or ventilator, a cuff, a pilot balloon, and radiopaque markings along its length to measure the insertion distance. The tube sizes...