Related Experiment Video
Updated: Jul 27, 2025
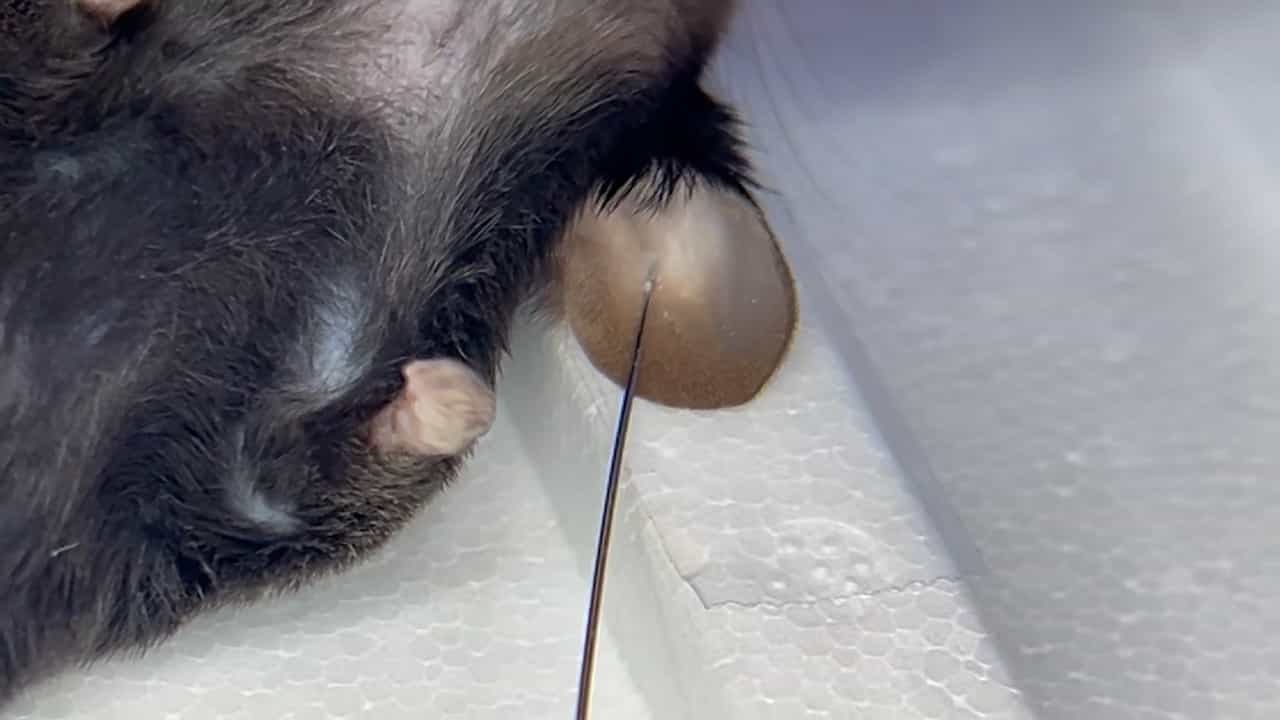

Intradermal Inoculation of Mycobacterium avium in the Mouse Ear
Published on: July 3, 2025
Risk factors for clinical progression in patients with pulmonary Mycobacterium avium complex disease without
Mizu Nonaka1,2, Masashi Matsuyama3,4, Chio Sakai2
1Department of Respiratory Medicine, National Hospital Organization Ibarakihigashi National Hospital, Ibaraki, Japan.

Objectives:
Limited data are available on the progression of pulmonary Mycobacterium avium complex (MAC) disease without culture-positive sputum. The aim of this study was to identify the risk factors associated with clinical progression of pulmonary MAC disease diagnosed by bronchoscopy.
Methods:
A single-center, retrospective, observational study was conducted. Pulmonary MAC patients diagnosed by bronchoscopy without culture-positive sputum from January 1, 2013, to December 31, 2017 were analyzed. Clinical progression after diagnosis was defined as having culture-positive sputum at least once or initiation of guideline-based therapy. Then, clinical characteristics were compared between clinically progressed patients and stable patients.
Results:
Ninety-three pulmonary MAC patients diagnosed by bronchoscopy were included in the analysis. During the 4-year period after diagnosis, 38 patients (40.9%) started treatment, and 35 patients (37.6%) had new culture-positive sputum. Consequently, 52 patients (55.9%) were classified into the progressed group, and 41 patients (44.1%) were classified into the stable group. There were no significant differences between the progressed and the stable groups in age, body mass index, smoking status, comorbidities, symptoms, or species isolated from bronchoscopy. On multivariate analysis, male sex, monocyte to lymphocyte ratio (MLR) ≥ 0.17, and the presence of combined lesions in the middle (lingula) and lower lobes were risk factors for clinical progression.
Conclusions:
Some patients with pulmonary MAC disease without culture-positive sputum progress within 4 years. Therefore, pulmonary MAC patients, especially male patients, having higher MLR or lesions in the middle (lingula) and lower lobes might need careful follow-up for a longer time.
More Related Videos


Related Concept Videos
 01:31
Pulmonary Tuberculosis III
The first classification is based on the development of the disease, and it includes the following categories:
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:20
Sputum Studies II: Culture and Sensitivity
Sputum culture and sensitivity is a medical procedure used to diagnose bacterial infections in the respiratory tract and select the most appropriate antibiotics for treatment. This process involves analyzing sputum samples of thick and opaque secretions produced in the lungs and airways. These samples are collected from patients and then sent to the laboratory for analysis.
The test can identify various pathogens responsible for respiratory infections, including Streptococcus,...