Related Experiment Video For four-hook anchor device
Updated: Jul 27, 2025
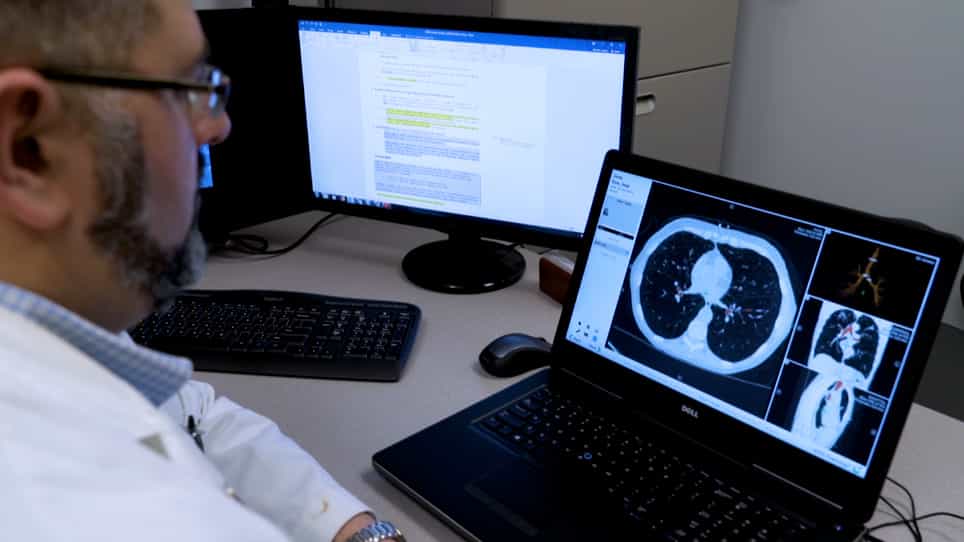

Electromagnetic Navigation Transthoracic Nodule Localization for Minimally Invasive Thoracic Surgery
Published on: May 4, 2022
Randomized comparison of the four-hook anchor device and hook-wire use for the preoperative localization of pulmonary
Xiaowu Zhang1, Jiaywei Tsauo1, Pengfei Tian1
1Department of Interventional Therapy, National Cancer Center/National Clinical Research Center for Cancer/Cancer Hospital, Chinese Academy of Medical Sciences and Peking Union Medical College, Beijing, China.

Objective:
To compare the efficacy and safety of preoperative localization of small pulmonary nodules (SPNs) with 4-hook anchor device and hook-wire before video-assisted thoracoscopic surgery.
Methods:
Patients with SPNs scheduled for computed tomography-guided nodule localization before video-assisted thoracoscopic surgery between May 2021 and June 2021 at our center were randomized to either 4-hook anchor group or hook-wire group. The primary end point was intraoperative localization success.
Results:
After randomization, 28 patients with 34 SPNs were assigned to the 4-hook anchor group and 28 patients with 34 SPNs to the hook-wire group. The operative localization success rate was significantly greater in the 4-hook anchor group than in the hook-wire group (94.1% [32/34] vs 64.7% [22/34]; P = .007). All lesions in the 2 groups were successfully resected under thoracoscopy, but 4 patients in the hook-wire group who required transition from wedge resection to segmentectomy or lobectomy because of unsuccessful localization. Total localization-related complication rate was significantly lower in the 4-hook anchor group than in the hook-wire group (10.3% [3/28] vs 50.0% [14/28]; P = .004). The rate of chest pain requiring analgesia after the localization procedure was significantly lower in the 4-hook anchor group than in the hook-wire group (0 vs 5/28, 17.9%; P = .026). There were no significant differences in localization technical success rate, operative blood loss, hospital stay length and hospital cost between the 2 groups (all P > .05).
Conclusions:
The use of the 4-hook anchor device for SPN localization offers advantages over the traditional hook-wire technique.