Related Experiment Video
Updated: Jul 26, 2025
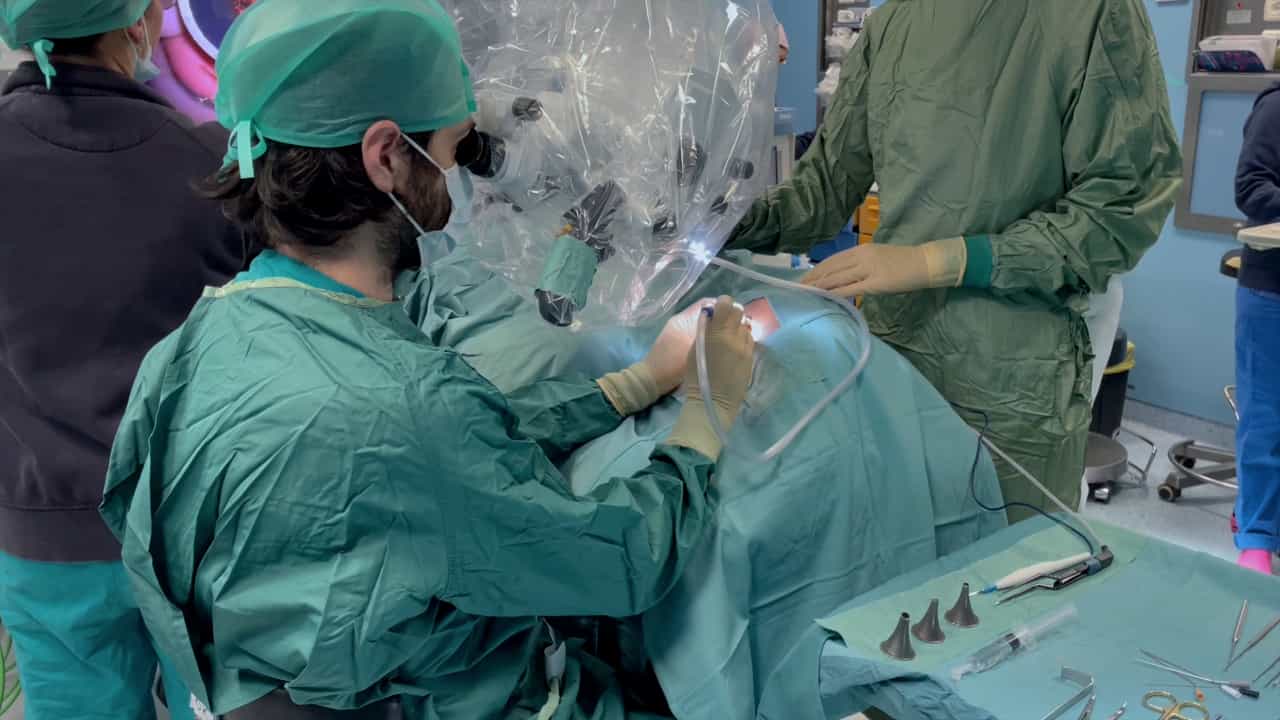

Surgical Treatment of an Endolymphatic Sac Tumor
Published on: May 26, 2023
Clinical evaluation of pulsatile tinnitus: history and physical examination techniques to predict vascular etiology
Daniel D Cummins1, M Travis Caton2, Kafi Hemphill3
1Departments of Radiology and Biomedical Imaging, University of California San Francisco, San Francisco, California, USA.

Background:
Pulsatile tinnitus (PT) may be due to a spectrum of cerebrovascular etiologies, ranging from benign venous turbulence to life threatening dural arteriovenous fistulas. A focused clinical history and physical examination provide clues to the ultimate diagnosis; however, the predictive accuracy of these features in determining PT etiology remains uncertain.
Methods:
Patients with clinical PT evaluation and DSA were included. The final etiology of PT after DSA was categorized as shunting, venous, arterial, or non-vascular. Clinical variables were compared between etiologies using multivariate logistic regression, and performance at predicting PT etiology was determined by area under the receiver operating curve (AUROC).
Results:
164 patients were included. On multivariate analysis, patient reported high pitch PT (relative risk (RR) 33.81; 95% CI 3.81 to 882.80) compared with exclusively low pitch PT and presence of a bruit on physical examination (9.95; 2.04 to 62.08; P=0.007) were associated with shunting PT. Hearing loss was associated with a lower risk of shunting PT (0.16; 0.03 to 0.79; P=0.029). Alleviation of PT with ipsilateral lateral neck pressure was associated with a higher risk of venous PT (5.24; 1.62 to 21.01; P=0.010). An AUROC of 0.882 was achieved for predicting the presence or absence of a shunt and 0.751 for venous PT.
Conclusion:
In patients with PT, clinical history and physical examination can achieve high performance at detecting a shunting lesion. Potentially treatable venous etiologies may also be suggested by relief with neck compression.
More Related Videos
Related Concept Videos
 01:27
Assessment of the Cardiovascular System III: Palpation
Jugular Venous Pressure (JVP) Measurement
Position the patient at a thirty- to forty-five-degree angle or in a semi-fowler's position. Look for the highest point of pulsation in the internal jugular vein and measure the vertical distance to the angle of Loius or sternal angle. A normal JVP is 3-4 cm above...
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:23
Assessment of the Cardiovascular System I: Subjective Data
Initial Enquiry
Ask the patient about their primary concern and thoroughly explore all reported symptoms.
Medical History
Investigate past illnesses affecting the cardiovascular system, such as angina, anemia, rheumatic fever, congenital heart disease, stroke, thrombophlebitis, dysrhythmias, varicosities
Inquire about symptoms...
 01:25
Assessment of apical radial pulse
The A-R pulse assessment involves simultaneous evaluation of the apical and radial pulses. When the apical and radial pulse rates vary, this assessment helps identify a pulse deficit.
Pre-Procedural Preparation
 01:29
Cardiovascular System Abnormal Findings I: Inspection and Palpation
Abnormal findings observed during an inspection
 01:29
Assessment of the Cardiovascular System II: Inspection
Head and Neck