Related Experiment Video
Updated: Jul 26, 2025
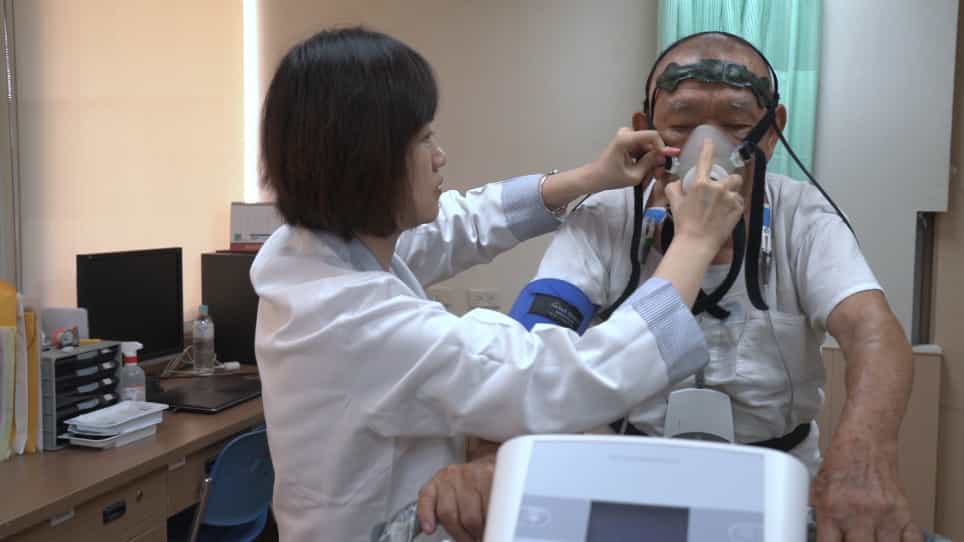
Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Strategic multimodal non-invasive assessment of cardiac performance in patients with heart failure
Mi-Jeong Kim1,2, Jung Sun Cho1,3, Kyusup Lee1,3
1Catholic Research Institute for Intractable Cardiovascular Disease, College of Medicine, The Catholic University of Korea, Seoul, Korea.

Insights
Combining non-invasive cardiac assessments, including N-terminal pro-B-type natriuretic peptide (NT-proBNP) and echocardiography for left ventricular filling pressure (LVFP), improves heart failure (HF) prognostication. Left atrial mechanics and exercise capacity further enhance risk prediction.
Area of Science:
- Cardiology
- Cardiovascular Medicine
- Heart Failure Research
Background:
- Heart failure (HF) management relies on predicting long-term outcomes.
- Various non-invasive cardiac tests exist, but their synergistic potential for prognostication is underutilized.
Purpose of the Study:
- To evaluate the combined predictive power of non-invasive assessments for left ventricular filling pressure (LVFP), left atrial remodeling, and exercise capacity in HF patients.
- To determine if integrating these assessments offers superior prognostication compared to individual measures.
Main Methods:
- Prospective observational study of 224 hospitalized HF patients (Stages A-C).
- Evaluations included N-terminal pro-B-type natriuretic peptide (NT-proBNP), echocardiography with 2D speckle tracking for LVFP grading (Echo-LVFP), and cardiopulmonary exercise testing (CPET).
- Patients were stratified into three groups based on NT-proBNP and Echo-LVFP levels.
Main Results:
- Adverse outcomes (composite of CV death, ACS, stroke, HF hospitalization) were analyzed over 18.6 months.
- Event-free survival differed significantly across the three LVFP groups (log-rank P < 0.001).
- Left atrial dysfunction (peak longitudinal strain <28%) and reduced exercise capacity (peak VO2) were independent predictors of adverse outcomes, incrementally improving LVFP-based risk stratification.
Conclusions:
- Combined NT-proBNP and Echo-LVFP effectively predict adverse outcomes in diverse HF stages.
- Left atrial mechanics and exercise capacity provide incremental prognostic value.
- Integrating non-invasive cardiac assessments offers a comprehensive profile for improved cardiac performance evaluation and risk stratification.
Aims:
Although various non-invasive cardiac examinations are known to be predictive of long-term outcomes in patients with heart failure (HF), combining them properly would provide synergism. We aimed to show that non-invasive cardiac assessments targeting left ventricular filling pressure (LVFP), left atrial remodelling, and exercise capacity would provide better prognostication in combination.
Methods And Results:
This prospective observational study included consecutive hospitalized stage A-C HF patients evaluated with N-terminal pro-B-type natriuretic peptide (NT-proBNP), echocardiography including two-dimensional speckle tracking, and cardiopulmonary exercise testing. According to NT-proBNP and echocardiographic semi-quantitative LVFP grading (Echo-LVFP), patients were classified into three LVFP groups: normal range of both Echo-LVFP and NT-proBNP (Group 1), normal range of Echo-LVFP but elevated NT-proBNP (Group 2), and elevated Echo-LVFP and NT-proBNP (Group 3). The adverse outcome was defined as a composite of cardiovascular death, non-fatal acute coronary syndrome, acute stroke, or HF-related hospitalization. Among 224 HF patients (mean age of 63.8 ± 11.6 years, 158 men) analysed, 160 (71.4%) had ischaemic aetiology. During the follow-up of 18.6 ± 9.8 months, event-free survival in Group 2 (n = 56, age of 65.4 ± 12.4) was better than that in Group 3 (n = 45, age of 68.5 ± 11.5) but worse than that in Group 1 (n = 123, mean age of 61.4 ± 10.5) (log-rank P < 0.001). Mechanical left atrial dysfunction (peak longitudinal strain <28%) (adjusted hazard ratio 5.69, 95% confidence interval 1.06-4.48) and limited exercise capacity (peak VO2 per +5 mL/kg/min) (adjusted hazard ratio 0.63, 95% confidence interval 0.46-0.87) were also predictable adverse outcomes. Serial addition of peak VO2 and left atrial strain to the model incrementally enhanced the predictive power of LVFP-based risk stratification for adverse outcomes.
Conclusions:
The combination of NT-proBNP and Echo-LVFP could be used to predict adverse outcomes in patients with HF of various stages. Left atrial mechanics and exercise capacity are incremental to prognostication. Non-invasive test findings could be strategically combined to provide an integrative profile of cardiac performance.
More Related Videos
 07:49
Author Spotlight: Investigating HR-Dependent Cardiac Function in Mouse Models Through a Novel Atrial-Pacing Approach
Published on: July 21, 2023
 11:50
High-frequency High-resolution Echocardiography: First Evidence on Non-invasive Repeated Measure of Myocardial Strain, Contractility, and Mitral Regurgitation in the Ischemia-reperfused Murine Heart
Published on: July 9, 2010
Related Concept Videos
 01:30
Heart Failure IV: Classification and Diagnostic Evaluation
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:30
Heart Failure VII: Nursing Interventions
 01:30
Heart Failure V: Medical Management
 01:30
Pulse rhythm
Conversely, an irregular pulse pattern is termed dysrhythmia, stemming from disruptions in cardiac...