Related Experiment Video
Updated: Jul 26, 2025
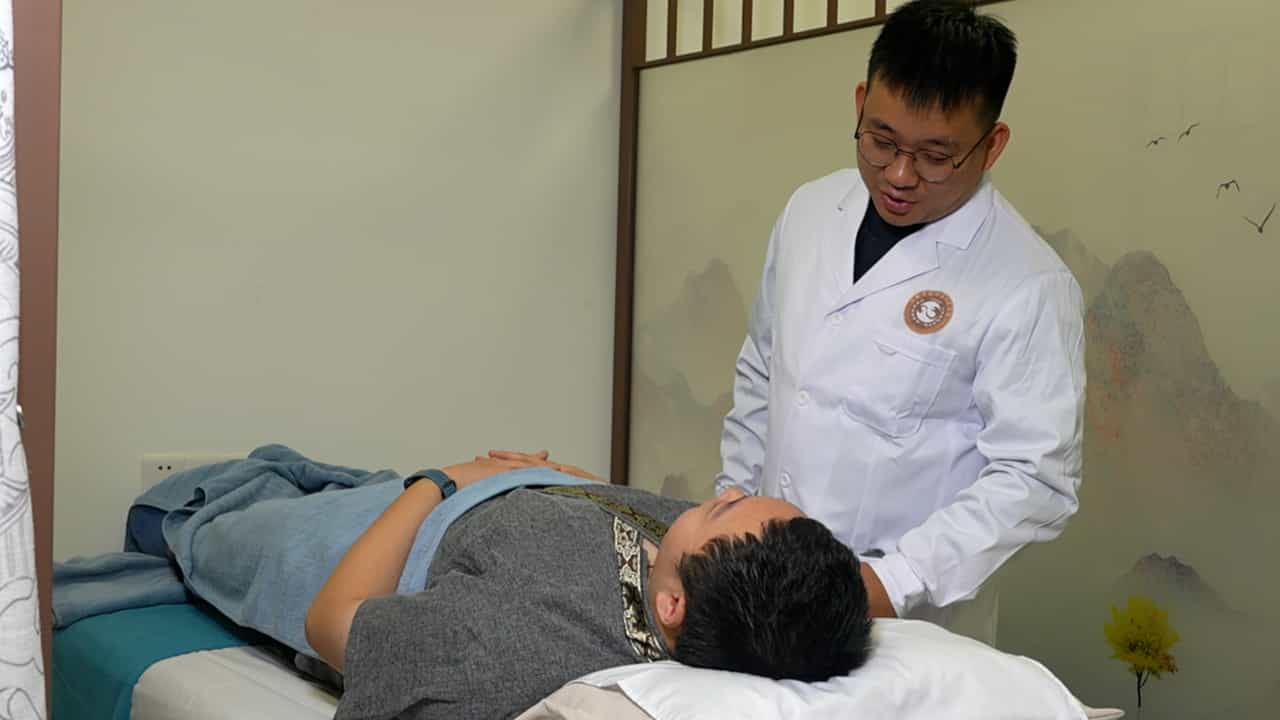
Author Spotlight: Evaluating the Therapeutic Efficacy of Moving Cupping Along Meridians for Acute Exacerbation of COPD
Published on: September 27, 2024
Cause-specific mortality in COPD subpopulations: a cohort study of 339 647 people in England
Hannah Whittaker1, Kieran J Rothnie2, Jennifer K Quint3
1School of Public Health and National Heart and Lung Institute, Imperial College London, London, UK h.whittaker@imperial.ac.uk.

Background:
Identifying correlates of cause-specific mortality in patients with chronic obstructive pulmonary disease (COPD) may aid the targeting of therapies to reduce mortality. We determined factors associated with causes of death in a primary care COPD population.
Methods:
Clinical Practice Research Datalink Aurum was linked to Hospital Episode Statistics and death certificate data. People with COPD alive between 1 January 2010 and 1 January 2020 were included. Patient characteristics were defined before the start of follow-up: (a) frequency and severity of exacerbations; (b) emphysema or chronic bronchitis; (c) Global Obstructive Lung Disease (GOLD) groups A-D; and (d) airflow limitation. We used Cox Proportional Hazards regression and competing risks to investigate the association between patient characteristics and risk of all-cause, COPD and cardiovascular (CV) mortality.
Results:
339 647 people with COPD were included of which 97 882 died during follow-up (25.7% COPD related and 23.3% CV related). Airflow limitation, GOLD group, exacerbation frequency and severity, and COPD phenotype were associated with all-cause mortality. Exacerbations, both increased frequency and severity, were associated with COPD-related mortality (≥2 exacerbations vs none adjusted HR: 1.64, 1.57-1.71; 1 severe vs none adjusted HR: 2.17, 2.04-2.31, respectively). Patients in GOLD groups B-D had a higher risk of COPD and CV mortality compared with GOLD group A (GOLD group D vs group A, adjusted HR for COPD mortality: 4.57, 4.23-4.93 and adjusted HR for CV mortality: 1.53, 1.41-1.65). Increasing airflow limitation was also associated with both COPD and CV mortality (GOLD 4 vs 1, adjusted HR: 12.63, 11.82-13.51 and adjusted HR: 1.75, 1.60-1.91, respectively).
Conclusion:
Poorer airflow limitation, worse functional status and exacerbations had substantial associations with risk of all-cause mortality. Differing results for CV and COPD-related mortality suggests interventions to prevent mortality may need to target particular characteristics or time points in the disease course.

Related Concept Videos
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD: