Related Experiment Video
Updated: Jul 26, 2025
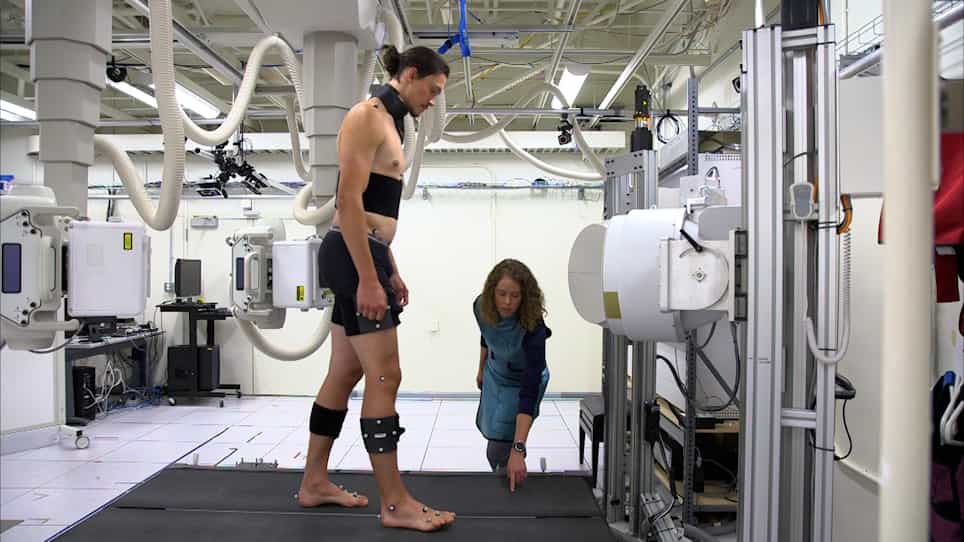
In Vivo Quantification of Hip Arthrokinematics during Dynamic Weight-bearing Activities using Dual Fluoroscopy
Published on: July 2, 2021
Acute calcium pyrophosphate crystal arthritis is associated with an increased rate of hip and knee joint surgery
David Harris1, Christopher Frampton2, Sandeep Patel3
1Rheumatology Department, Waikato Hospital, Hamilton, New Zealand.

Objective:
Acute calcium pyrophosphate (CPP) crystal arthritis is a distinct manifestation of calcium pyrophosphate crystal deposition (CPPD). No studies have specifically examined whether acute CPP crystal arthritis is associated with progressive structural joint damage. The objective of this retrospective cohort study was to evaluate the relative rate of hip and knee joint arthroplasties as an estimate of structural joint damage accrual, in a population of patients with acute CPP crystal arthritis.
Methods:
Data were collected from Waikato District Health Board (WDHB) to identify an acute CPP crystal arthritis cohort with clinical episodes highly characteristic of acute CPP crystal arthritis. Data on hip and knee joint arthroplasties were collected from the New Zealand Orthopaedic Association's Joint Registry. The rate of arthroplasties in the cohort was compared with the age-ethnicity-matched New Zealand population. Additional analysis was performed for age, obesity (BMI) and ethnicity.
Results:
The acute CPP crystal arthritis cohort included 99 patients; 63 were male and the median age was 77 years (interquartile range, 71-82). The obesity rate was 36% with a median BMI of 28.4 kg/m2 (interquartile range, 25.8-32.2), comparable to the New Zealand population. The standardized surgical rate ratio in the cohort vs the age-ethnicity-matched New Zealand population was 2.54 (95% CI: 1.39, 4.27).
Conclusion:
Our study identified a considerable increase in the rate of hip and knee joint arthroplasties in patients with episodes of acute CPP crystal arthritis. This suggests CPP crystal arthritis may be a chronic condition, leading to progressive joint damage.


Related Concept Videos
 01:30
Urinary Tract Calculi III: Medical Management
 01:26
Urinary Tract Calculi II: Pathophysiology and Clinical Manifestations
 01:28
Urinary Tract Calculi I: Introduction
 01:24
Chronic Kidney Disease II: Clinical Manifestations
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:27
Urinary Tract Calculi IV: Nutrition Therapy and Prevention