Related Experiment Video
Updated: Jul 3, 2026


A Bedside, Single Burr Hole Approach to Multimodality Monitoring in Severe Brain Injury
Published on: March 26, 2019
Hydrocephalus is an independent factor affecting morbidity and mortality of ICH patients: Systematic review and
Petra Octavian Perdana Wahjoepramono1,2, Aloysius Bagus Sasongko1,2, Danny Halim3,4
1Department of Neurosurgery, Faculty of Medicine, Pelita Harapan University/Siloam Hospitals, Tangerang, Banten, Indonesia.

Insights
Hydrocephalus significantly worsens outcomes for intracerebral hemorrhage (ICH) patients, increasing mortality and reducing functional recovery. Incorporating hydrocephalus (HC) into prognostication scores is crucial for better patient management.
Area of Science:
- Neurology
- Neurosurgery
- Critical Care Medicine
Background:
- Intracerebral hemorrhage (ICH) remains a leading cause of death and disability.
- Intraventricular extension (IVH) is a known negative prognostic factor in ICH.
- Hydrocephalus (HC), a complication of IVH, has not been consistently evaluated in ICH prognostication.
Purpose of the Study:
- To evaluate the prognostic significance of hydrocephalus (HC) in patients with intracerebral hemorrhage (ICH).
- To compare outcomes of ICH patients with and without IVH and HC through meta-analysis.
Main Methods:
- Systematic literature search for studies comparing mortality/morbidity in ICH, ICH with IVH, and ICH with IVH and HC.
- Meta-analysis using Mantel-Haenszel Risk Ratio at 95% significance.
Main Results:
- ICH with IVH and HC showed significantly higher short-term (30-day) and long-term (90-day) mortality risks compared to ICH and ICH with IVH.
- Patients with ICH, IVH, and HC had lower rates of good functional outcomes at 3 and 6 months.
- Confounding factors included comorbidities, hemorrhage volume, midline shift, and low initial GCS score.
Conclusions:
- Hydrocephalus is an independent negative prognostic factor in intracerebral hemorrhage.
- Inclusion of hydrocephalus in prognostication scoring systems for ICH is recommended.
Background:
Despite advances in our knowledge of the causes, preventions, and treatments of stroke, it continues to be a leading cause of death and disability. The most common type of stroke-related morbidity and mortality is intracerebral haemorrhage (ICH). Many prognostication scores include an intraventricular extension (IVH) after ICH because it affects mortality independently. Although it is a direct result of IVH and results in significant damage, hydrocephalus (HC) has never been taken into account when calculating prognostication scores. This study aimed to evaluate the significance of hydrocephalus on the outcomes of ICH patients by meta-analysis.
Methods:
Studies that compared the rates of mortality and/or morbidity in patients with ICH, ICH with IVH (ICH + IVH), and ICH with IVH and HC (ICH + IVH + HC) were identified. A meta-analysis was performed by using Mantel-Haezel Risk Ratio at 95% significance.
Results:
This meta-analysis included thirteen studies. The findings indicate that ICH + IVH + HC has higher long-term (90-day) and short-term (30-day) mortality risks than ICH (4.26 and 2.30 higher risks, respectively) and ICH + IVH (1.96 and 1.54 higher risks). Patients with ICH + IVH + HC have lower rates of short-term (3 months) and long-term (6 months) good functional outcomes than those with ICH (0.66 and 0.38 times) or ICH + IVH (0.76 and 0.54 times). Confounding variables included vascular comorbidities, haemorrhage volume, midline shift, and an initial GCS score below 8.
Conclusion:
Hydrocephalus causes a poorer prognosis in ICH patients. Thus, it is reasonable to suggest the inclusion of hydrocephalus in ICH prognostication scoring systems.


Related Concept Videos
 01:26
Bacterial Meningitis II: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:19
Cerebral Edema l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
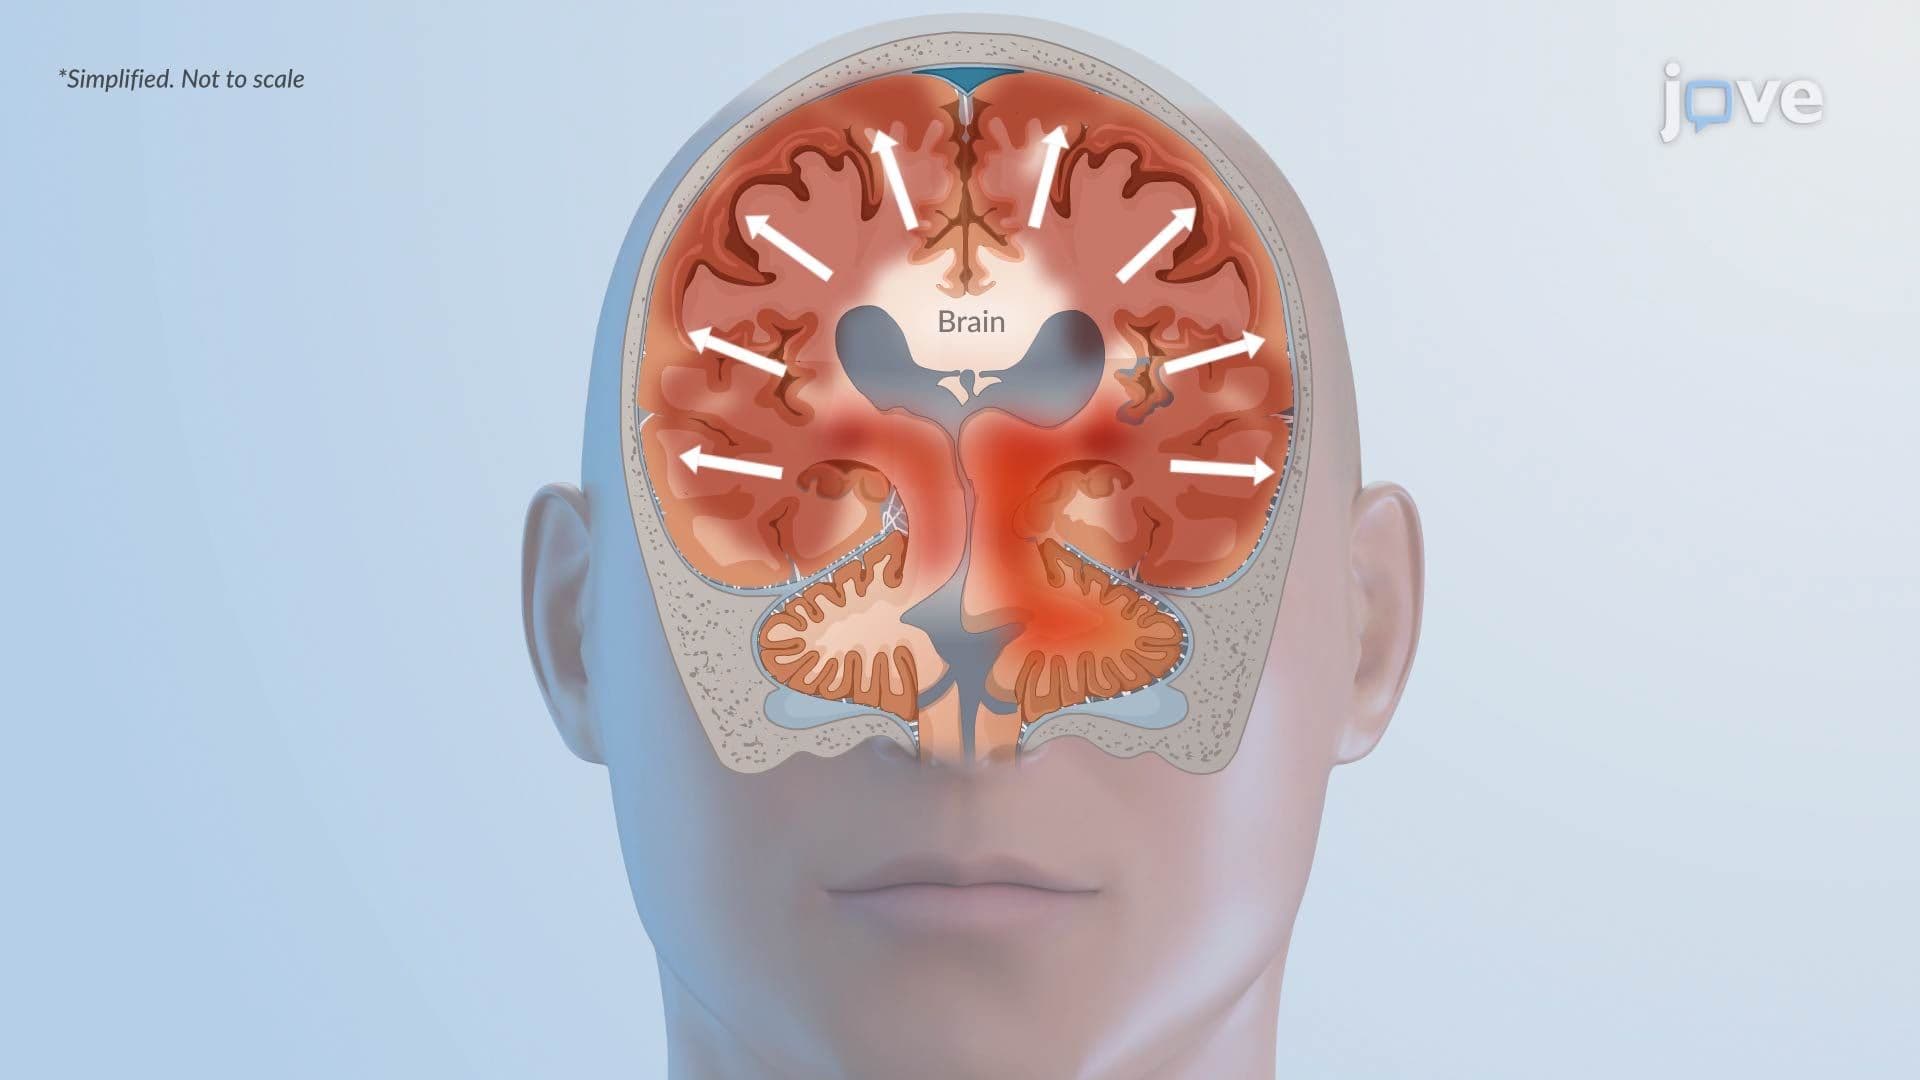 01:21
Cytotoxic Edema: Pathophysiology