Related Experiment Video
Updated: Jul 25, 2025

Assessment of Myofilament Ca2+ Sensitivity Underlying Cardiac Excitation-contraction Coupling
Published on: August 1, 2016
Dystrophic cardiomyopathy: role of the cardiac myofilaments
Thomas G George1, Laurin M Hanft1, Maike Krenz1
1Department of Medical Pharmacology and Physiology, Dalton Cardiovascular Research Center, University of Missouri-Columbia, Columbia, MO, United States.

Abstract:
Dystrophic cardiomyopathy arises from mutations in the dystrophin gene. Dystrophin forms part of the dystrophin glycoprotein complex and is postulated to act as a membrane stabilizer, protecting the sarcolemma from contraction-induced damage. Duchenne muscular dystrophy (DMD) is the most severe dystrophinopathy, caused by a total absence of dystrophin. Patients with DMD present with progressive skeletal muscle weakness and, because of treatment advances, a cardiac component of the disease (i.e., dystrophic cardiomyopathy) has been unmasked later in disease progression. The role that myofilaments play in dystrophic cardiomyopathy is largely unknown and, as such, this study aimed to address cardiac myofilament function in a mouse model of muscular dystrophy. To assess the effects of DMD on myofilament function, isolated permeabilized cardiomyocytes of wild-type (WT) littermates and Dmdmdx-4cv mice were attached between a force transducer and motor and subjected to contractile assays. Maximal tension and rates of force development (indexed by the rate constant, k tr) were similar between WT and Dmdmdx-4cv cardiac myocyte preparations. Interestingly, Dmdmdx-4cv cardiac myocytes exhibited greater sarcomere length dependence of peak power output compared to WT myocyte preparations. These results suggest dystrophin mitigates length dependence of activation and, in the absence of dystrophin, augmented sarcomere length dependence of myocyte contractility may accelerate ventricular myocyte contraction-induced damage and contribute to dystrophic cardiomyopathy. Next, we assessed if mavacamten, a small molecule modulator of thick filament activation, would mitigate contractile properties observed in Dmdmdx-4cv permeabilized cardiac myocyte preparations. Mavacamten decreased maximal tension and k tr in both WT and Dmdmdx-4cv cardiac myocytes, while also normalizing the length dependence of peak power between WT and Dmdmdx-4cv cardiac myocyte preparations. These results highlight potential benefits of mavacamten (i.e., reduced contractility while maintaining exquisite sarcomere length dependence of power output) as a treatment for dystrophic cardiomyopathy associated with DMD.


Related Concept Videos
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:25
Cardiomyopathy I: Introduction and Classification
 01:13
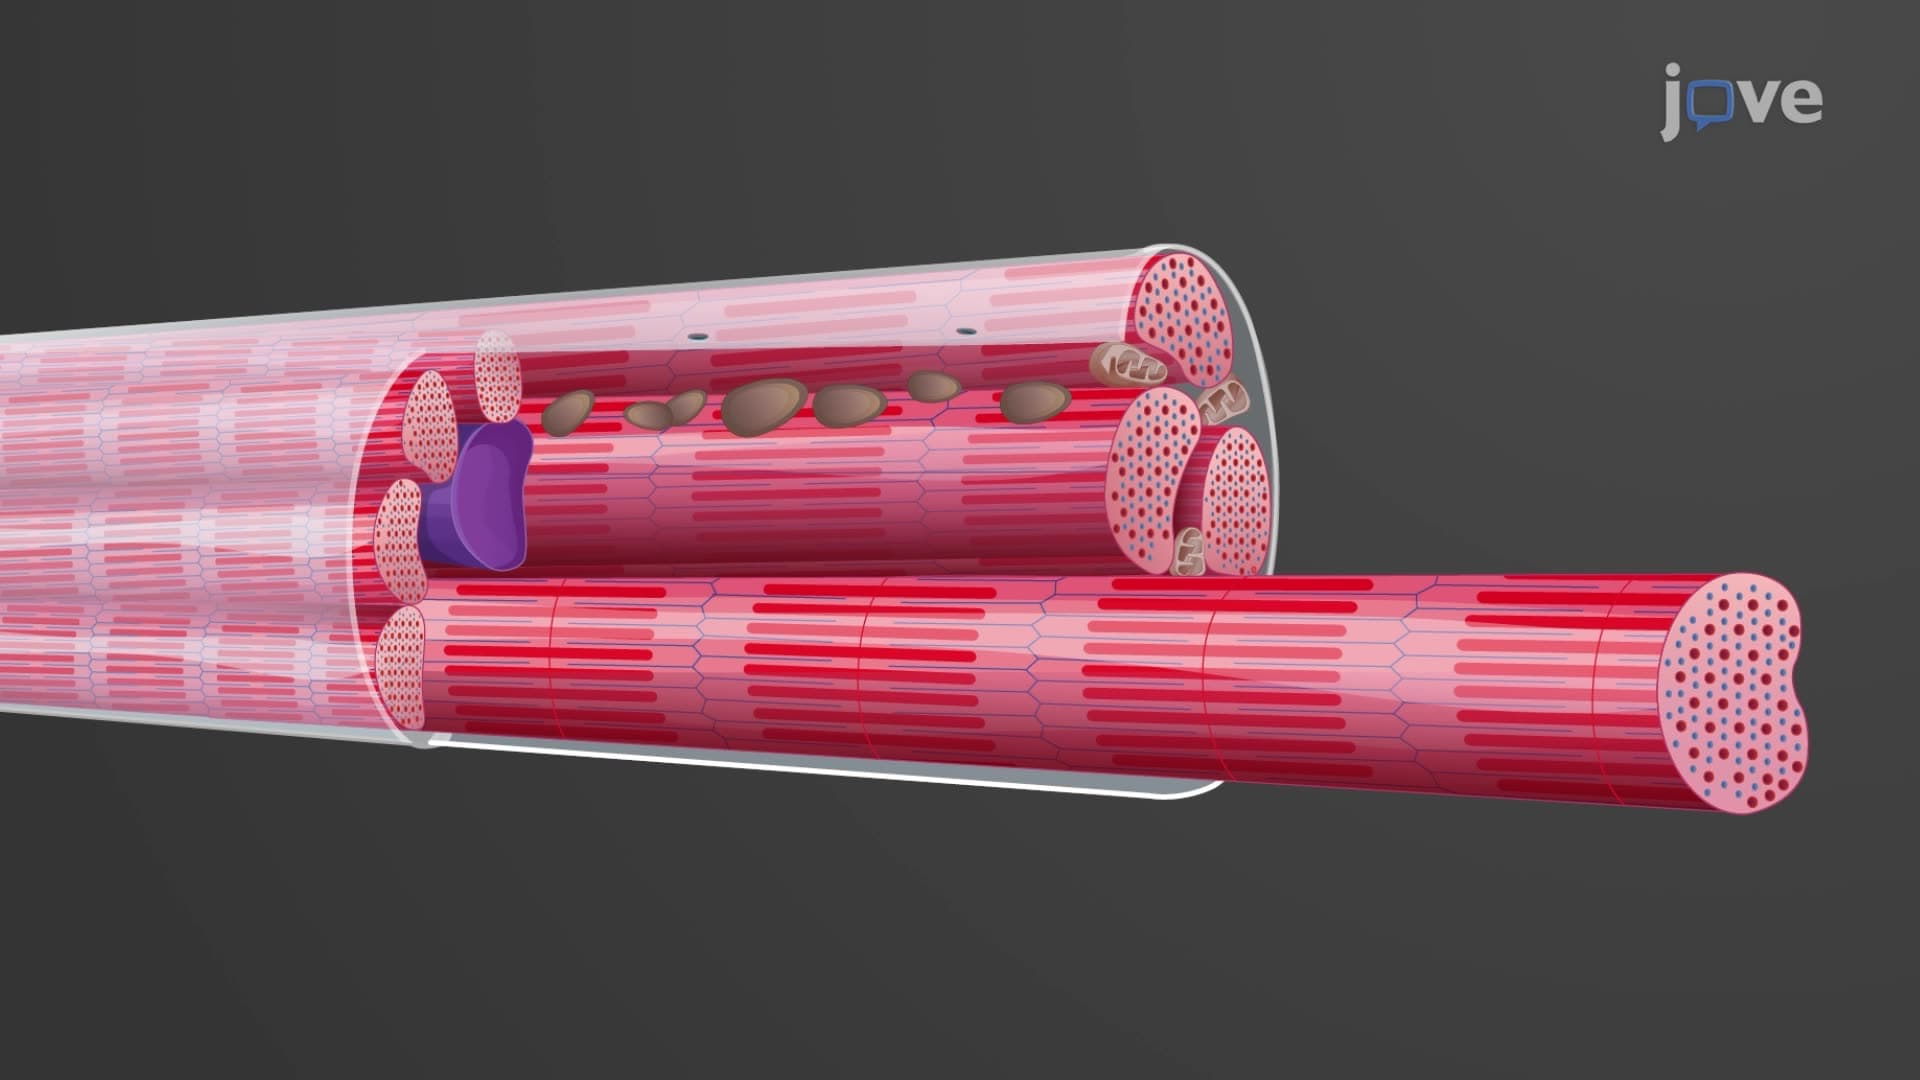
Structure of Cardiac Muscles
Compared to skeletal muscles, cardiac muscle cells are small and mostly have a single nucleus. Additionally, they are usually...
 01:08
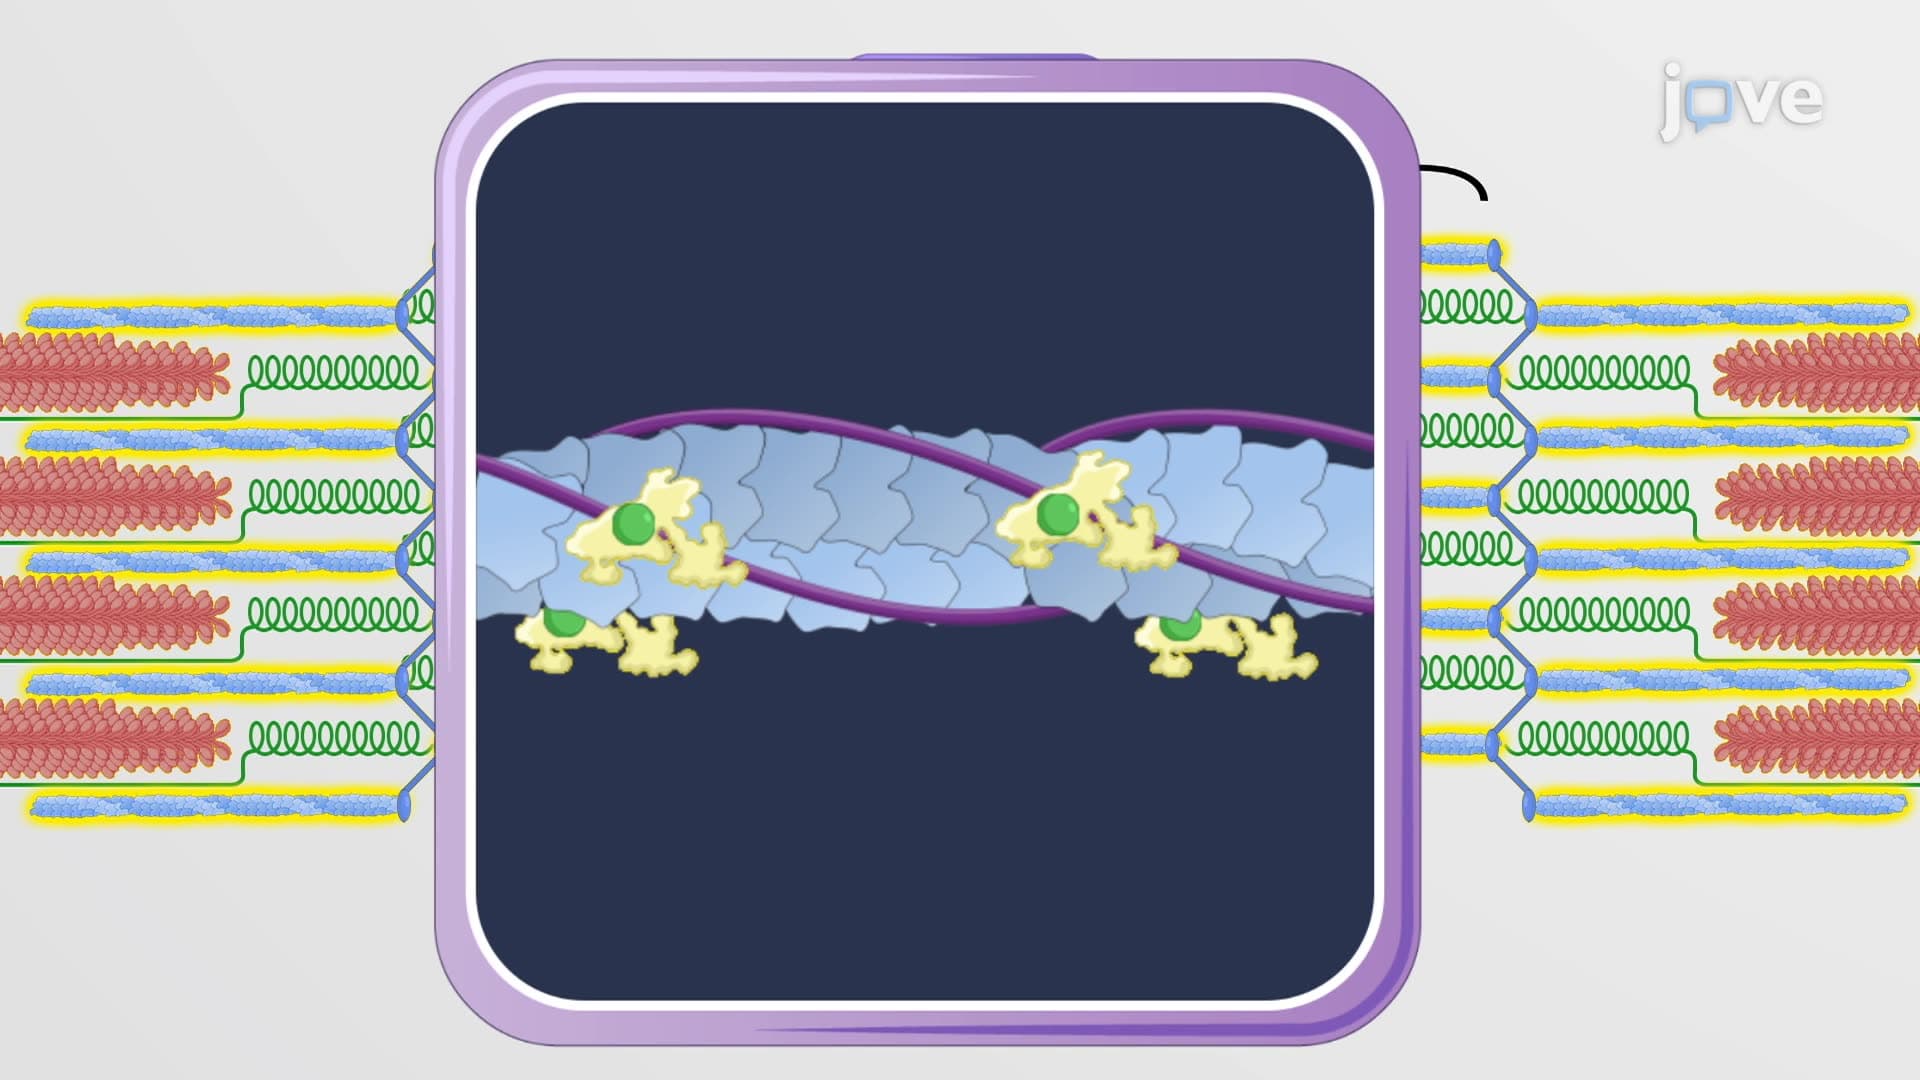
The Sarcomere
Each...
 01:27
Specialized Characteristics of Cardiac Muscles
Cardiac muscle cells are smaller than skeletal muscles, averaging 10–20 mm in diameter and 50–100 mm in length. However, they have large energy demands for continuous contraction and relaxation. This energy is almost exclusively derived from aerobic metabolism of energy...