Related Experiment Video
Updated: Jul 25, 2025
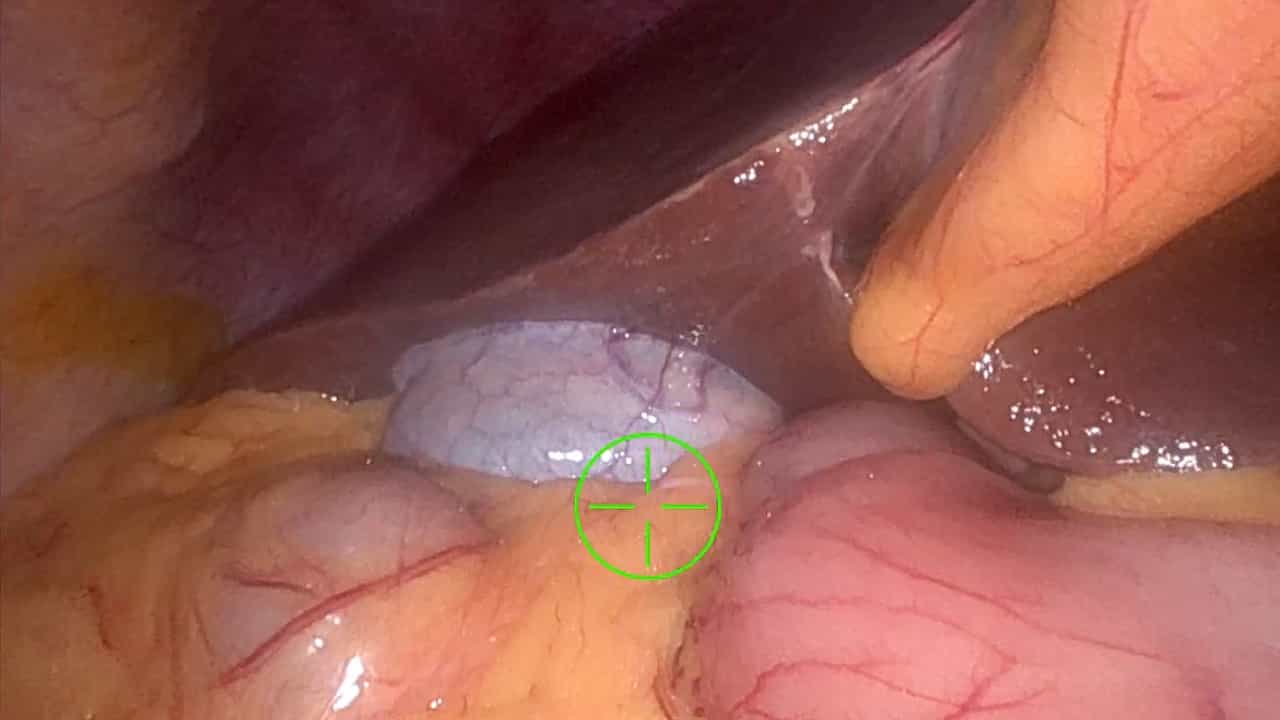

Application of Robot-assisted Pancreaticobiliary Junction Resection in Benign Duodenal Tumors
Published on: December 20, 2024
Endoscopic and Surgical Management of Non-Metastatic Ampullary Neuroendocrine Neoplasia: A Multi-Institutional
Elias Karam1, Marcus Hollenbach2, Einas Abou Ali3
1Hepato-Biliary, Pancreatic and Liver Transplantation Unit, Department of Visceral Surgery, Tours University Hospital, Tours, France.

Introduction:
Ampullary neuroendocrine neoplasia (NEN) is rare and evidence regarding their management is scarce. This study aimed to describe clinicopathological features, management, and prognosis of ampullary NEN according to their endoscopic or surgical management.
Methods:
From a multi-institutional international database, patients treated with either endoscopic papillectomy (EP), transduodenal surgical ampullectomy (TSA), or pancreaticoduodenectomy (PD) for ampullary NEN were included. Clinical features, post-procedure complications, and recurrences were assessed.
Results:
65 patients were included, 20 (30.8%) treated with EP, 19 (29.2%) with TSA, and 26 (40%) with PD. Patients were mostly asymptomatic (n = 46; 70.8%). Median tumor size was 17 mm (12-22), tumors were mostly grade 1 (70.8%) and pT2 (55.4%). Two (10%) EP resulted in severe American Society for Gastrointestinal Enterology (ASGE) adverse post-procedure complications and 10 (50%) were R0. Clavien 3-5 complications did not occur after TSA and in 4, including 1 postoperative death (15.4%) of patients after PD, with 17 (89.5%) and 26 R0 resection (100%), respectively. The pN1/2 rate was 51.9% (n = 14) after PD. Tumor size larger than 1 cm (i.e., pT stage >1) was a predictor for R1 resection (p < 0.001). Three-year overall survival and disease-free survival after EP, TSA, and PD were 92%, 68%, 92% and 92%, 85%, 73%, respectively.
Conclusion:
Management of ampullary NEN is challenging. EP should not be performed in lesions larger than 1 cm or with a endoscopic ultrasonography T stage beyond T1. Local resection by TSA seems safe and feasible for lesions without nodal involvement. PD should be preferred for larger ampullary NEN at risk of nodal metastasis.
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease