Related Experiment Video
Updated: Jul 25, 2025


Hyperinsulinemic-euglycemic Clamps in Conscious, Unrestrained Mice
Published on: November 16, 2011
Decreased branched-chain amino acids and elevated fatty acids during antecedent hypoglycemia in type 1 diabetes
Rui She1,2, Naba Hassan Al-Sari3, Ismo Matias Mattila3
1Department of Endocrinology and Nephrology, Nordsjællands Hospital, Hillerød, Capital Region of Denmark, Denmark.

Introduction:
Hypoglycemia is a major limiting factor in achieving recommended glycemic targets for people with type 1 diabetes. Exposure to recurrent hypoglycemia results in blunted hormonal counter-regulatory and symptomatic responses to hypoglycemia. Limited data on metabolic adaptation to recurrent hypoglycemia are available. This study examined the acute metabolic responses to hypoglycemia and the effect of antecedent hypoglycemia on these responses in type 1 diabetes.
Research Design And Methods:
Twenty-one outpatients with type 1 diabetes with normal or impaired awareness of hypoglycemia participated in a study assessing the response to hypoglycemia on 2 consecutive days by a hyperinsulinemic glucose clamp. Participants underwent a period of normoglycemia and a period of hypoglycemia during the hyperinsulinemic glucose clamp. Plasma samples were taken during normoglycemia and at the beginning and the end of the hypoglycemic period. Metabolomic analysis of the plasma samples was conducted using comprehensive two-dimensional gas chromatography with time-of-flight mass spectrometry.
Results:
In total, 68 metabolites were studied. On day 1, concentrations of the branched-chain amino acids, leucine (p=3.8×10⁻³) and isoleucine (p=2.2×10⁻³), decreased during hypoglycemia. On day 2, during hypoglycemia, five amino acids (including leucine and isoleucine) significantly decreased, and two fatty acids (tetradecanoic and oleic acids) significantly increased (p<0.05). Although more metabolites responded to hypoglycemia on day 2, the responses of the single metabolites were not statistically significant between the 2 days.
Conclusions:
In individuals with type 1 diabetes, one episode of hypoglycemia decreases leucine and isoleucine concentrations. Antecedent hypoglycemia results in the decrement of five amino acids and increases the concentrations of two fatty acids, suggesting an alteration between the two hypoglycemic episodes, which could indicate a possible adaptation. However, more studies are needed to gain a comprehensive understanding of the consequences of these alterations.
Trial Registration Number:
NCT01337362.
Insights
Recurrent hypoglycemia in type 1 diabetes alters amino acid and fatty acid metabolism. This metabolic adaptation may influence the body's response to future low blood sugar events.
Area of Science:
- Endocrinology and Metabolism
- Biochemistry
- Diabetes Research
Background:
- Hypoglycemia is a significant challenge for type 1 diabetes management.
- Recurrent hypoglycemia can lead to diminished counter-regulatory and symptomatic responses.
- Limited understanding exists regarding metabolic adaptations to repeated hypoglycemia.
Purpose of the Study:
- To investigate acute metabolic responses to hypoglycemia in type 1 diabetes.
- To assess the impact of antecedent hypoglycemia on these metabolic responses.
Main Methods:
- Utilized a hyperinsulinemic glucose clamp in 21 type 1 diabetes outpatients over two consecutive days.
- Collected plasma samples during normoglycemia and hypoglycemia for metabolomic analysis.
- Employed comprehensive two-dimensional gas chromatography with time-of-flight mass spectrometry.
Main Results:
- Hypoglycemia on day 1 decreased leucine and isoleucine concentrations.
- On day 2, hypoglycemia led to a decrease in five amino acids and an increase in two fatty acids (tetradecanoic and oleic acids).
- More metabolites responded to hypoglycemia on day 2, though individual responses were not statistically significant between days.
Conclusions:
- A single hypoglycemic episode in type 1 diabetes reduces leucine and isoleucine.
- Antecedent hypoglycemia alters amino acid and fatty acid profiles, suggesting potential metabolic adaptation.
- Further research is necessary to fully understand the implications of these metabolic changes.


Related Concept Videos
 01:15
Hypoglycemia and Glucagon
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:16
Hormones Regulating Blood Glucose
In addition to accelerating glucose uptake and utilization, insulin has...
 01:27
Glucose Homeostasis: Pancreatic Islets and Insulin Secretion
Insulin and C-peptide are...
 01:25
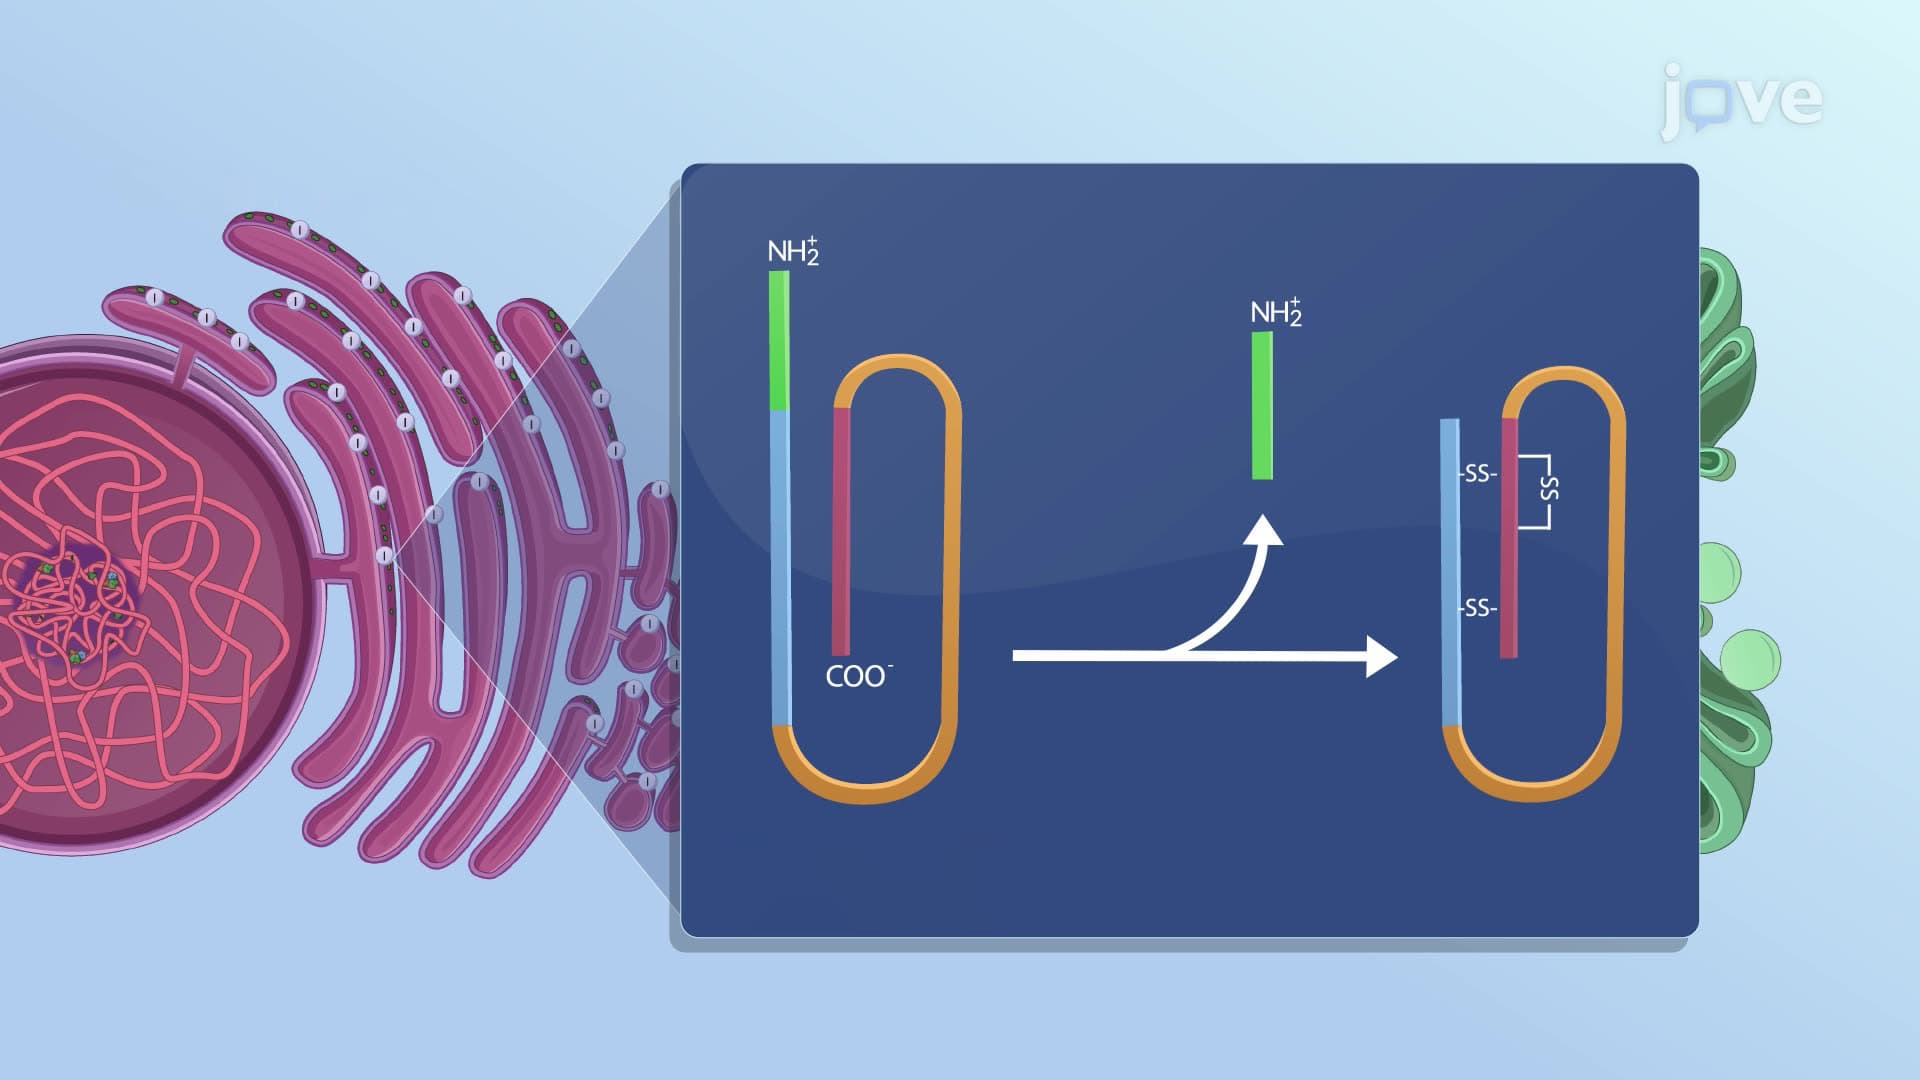
Insulin: Biosynthesis, Chemistry, and Preparation
Damage or functional impairment of β-cells inhibits insulin production, leading to diabetes. Diabetes treatment...
 01:16
Insulin: Dosing Regimen and Adverse Effects
The basal dose constitutes about 40%-50% of the total daily dose, with the rest as premeal insulin. The mealtime insulin dose should mirror...