Related Experiment Video
Updated: Jul 25, 2025
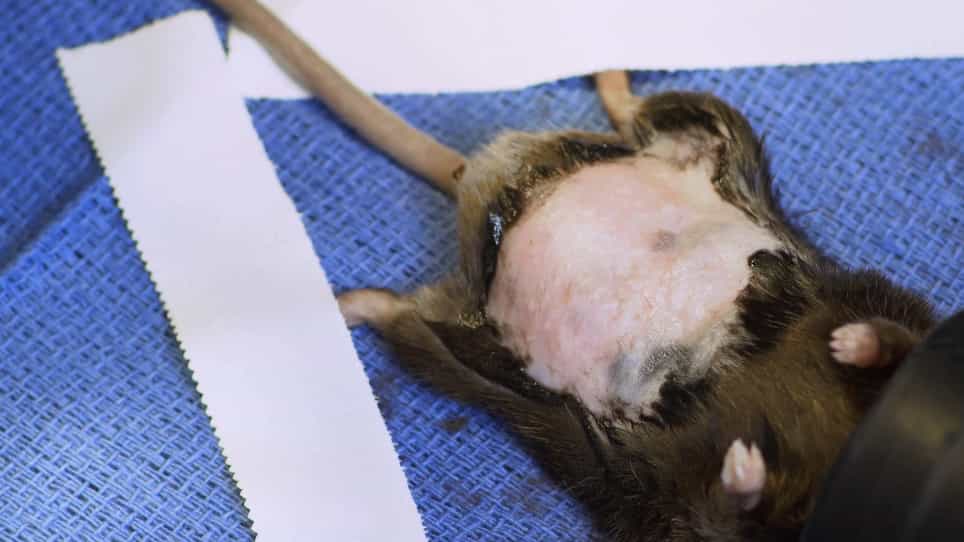

Creation of Colonic Anastomosis in Mice
Published on: January 17, 2019
Pediatric Colonic Anastomosis: Can Method of Anastomosis and Wound Closure be of Help?
Arindam Ghosh1, Somak Krishna Biswas2, Tapanjyoti Ghosh3
1Department of Pediatric Surgery, IPGMER and SSKM Hospital, Kolkata, West Bengal, India.

Insights
Serosubmucosal closure for colostomy wounds enhances the adoption of Enhanced Recovery After Surgery (ERAS) protocols in pediatric colorectal surgery. This technique promotes earlier bowel function and feeding, leading to shorter hospital stays and fewer complications.
Area of Science:
- Pediatric Surgery
- Surgical Innovation
- Enhanced Recovery After Surgery (ERAS) Protocols
Background:
- Enhanced Recovery After Surgery (ERAS) protocols are not well-established in pediatric surgical practice.
- ERAS focuses on optimizing patient recovery through reduced bowel preparation, standardized feeding, and early mobilization.
- This study investigates colonic anastomosis and colostomy wound closure techniques to facilitate ERAS implementation in children.
Purpose of the Study:
- To evaluate the influence of two colonic anastomosis techniques (Halsted and Matheson) and two colostomy wound closure methods on ERAS protocol adoption.
- To assess the impact of these surgical techniques on early feeding, bowel function, and hospital discharge in pediatric patients.
Main Methods:
- A single-institute randomized controlled study conducted over 2.4 years in a tertiary care facility.
- Patients underwent either serosubmucosal (Group I) or full-thickness (Group II) colonic anastomosis.
- Data on bowel function, hospital stay, and complications were collected and analyzed.
Main Results:
- Serosubmucosal anastomosis (Group I) showed earlier return of bowel sounds (1.51 days) and bowel movements (1.91 days) compared to full-thickness (Group II) (1.91 and 3.9 days, respectively).
- Postoperative hospital stay was significantly shorter in Group I (5.88 days) versus Group II (8.9 days).
- Overall complications were 16.48%, with superficial surgical site infections and minor leaks in both groups, and three major leaks in Group II requiring surgical intervention.
Conclusions:
- Serosubmucosal colostomy closure technique significantly aids ERAS protocol implementation in pediatric colorectal surgery.
- This method facilitates earlier bowel movements, earlier feeding initiation, and reduced postoperative complications.
- The findings support the use of serosubmucosal closure for improved ERAS outcomes in pediatric surgical patients.
Background:
Enhanced recovery after surgery (ERAS) protocols after colorectal surgery focused on reduced bowel preparation, standardized feeding schedule, earlier return of bowel function, and earlier resumption of normal activities. ERAS in pediatric surgical practice is not well established. The present study aims to present the results of two colonic anastomosis techniques of interrupted single-layered closure: Halsted (Horizontal Mattress) and Matheson (serosubmucosal or appositional extramucosal) along with two different methods of colostomy wound closure and their influence on the adoption of ERAS protocol of early feeding and early discharge.
Materials And Methods:
This single institute-based randomized control study was conducted in a tertiary care facility in Kolkata for 2.4 years. Patients were chosen randomly for serosubmucosal (Group I) and full-thickness (Group II) anastomosis.
Results:
Among total of 91 patients (Group I-43 and Group II-48), Return of bowel sounds and passage of bowel averaged 1.51 ± 0.51 and 1.91 ± 0.55 days in Group I and 1.91 ± 0.57 and 3.9 ± 0.66 days in Group II, respectively. Postoperative hospital stay averaged 5.88 ± 1.12 days in Group I and 8.9 ± 1.17 days in Group II. Overall 15 (16.48%) patients had complications among which SSI (Suprficial surgical site infection) and minor leaks (Group I-3 and 1 and Group II-5 and 3, respectively) which were treated conservatively (Clavien-Dindo Grade-I) and three major leaks under Group II requiring surgical intervention (Clavien-Dindo Grade-III).
Conclusion:
This study concludes that the technique of colostomy closure in the form serosubmucosal closure helps in the implementation of ERAS protocol by producing early bowel movement, early initiation of food, and less postoperative complications.


