Related Experiment Video
Updated: Jul 24, 2025
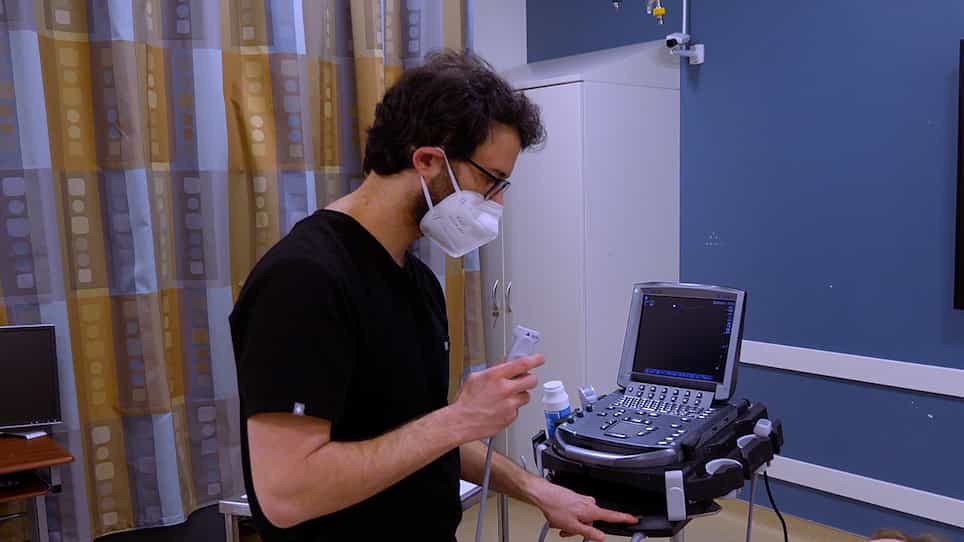

Point-of-Care Lung Ultrasound in Adults: Image Acquisition
Published on: March 3, 2023
Clinical benefit of AI-assisted lung ultrasound in a resource-limited intensive care unit
Phung Tran Huy Nhat1,2, Nguyen Van Hao3,4,5, Phan Vinh Tho4
1Oxford University Clinical Research Unit, Ho Chi Minh City, Vietnam. nhat.phung@kcl.ac.uk.

Background:
Interpreting point-of-care lung ultrasound (LUS) images from intensive care unit (ICU) patients can be challenging, especially in low- and middle- income countries (LMICs) where there is limited training available. Despite recent advances in the use of Artificial Intelligence (AI) to automate many ultrasound imaging analysis tasks, no AI-enabled LUS solutions have been proven to be clinically useful in ICUs, and specifically in LMICs. Therefore, we developed an AI solution that assists LUS practitioners and assessed its usefulness in a low resource ICU.
Methods:
This was a three-phase prospective study. In the first phase, the performance of four different clinical user groups in interpreting LUS clips was assessed. In the second phase, the performance of 57 non-expert clinicians with and without the aid of a bespoke AI tool for LUS interpretation was assessed in retrospective offline clips. In the third phase, we conducted a prospective study in the ICU where 14 clinicians were asked to carry out LUS examinations in 7 patients with and without our AI tool and we interviewed the clinicians regarding the usability of the AI tool.
Results:
The average accuracy of beginners' LUS interpretation was 68.7% [95% CI 66.8-70.7%] compared to 72.2% [95% CI 70.0-75.6%] in intermediate, and 73.4% [95% CI 62.2-87.8%] in advanced users. Experts had an average accuracy of 95.0% [95% CI 88.2-100.0%], which was significantly better than beginners, intermediate and advanced users (p < 0.001). When supported by our AI tool for interpreting retrospectively acquired clips, the non-expert clinicians improved their performance from an average of 68.9% [95% CI 65.6-73.9%] to 82.9% [95% CI 79.1-86.7%], (p < 0.001). In prospective real-time testing, non-expert clinicians improved their baseline performance from 68.1% [95% CI 57.9-78.2%] to 93.4% [95% CI 89.0-97.8%], (p < 0.001) when using our AI tool. The time-to-interpret clips improved from a median of 12.1 s (IQR 8.5-20.6) to 5.0 s (IQR 3.5-8.8), (p < 0.001) and clinicians' median confidence level improved from 3 out of 4 to 4 out of 4 when using our AI tool.
Conclusions:
AI-assisted LUS can help non-expert clinicians in an LMIC ICU improve their performance in interpreting LUS features more accurately, more quickly and more confidently.


Related Concept Videos
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:30
Acute Respiratory Failure-III
 01:21
Acute Respiratory Failure-I
Definition: It is defined by specific criteria based on blood gas measurements. Hypoxemia happens when the partial pressure of oxygen (PaO2) falls below 60 mmHg. At the same time,...