Fractured and delayed: A qualitative analysis of disruptions in care for gynecologic malignancies during incarceration
Related Experiment Video
Updated: Jul 24, 2025
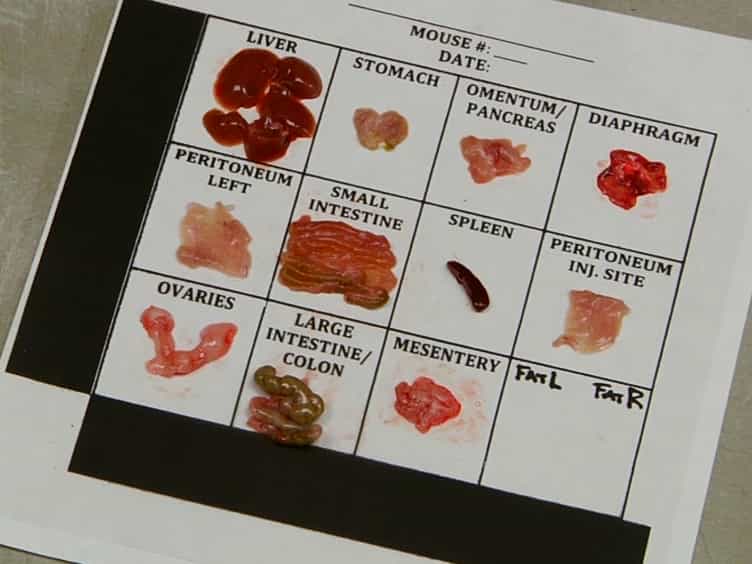
Quantitation of Intra-peritoneal Ovarian Cancer Metastasis
Published on: July 18, 2016
Wesley C Burkett1, Yoshiko Iwai2, Paola A Gehrig3
1Division of Gynecologic Oncology, Department of Obstetrics and Gynecology, University of North Carolina at Chapel Hill, Chapel Hill, NC, United States of America.

Objective:
Women are experiencing growing rates of incarceration at twice the pace of that for men. Additionally, one-third will be older than 55 years of age by the end of the decade. Women who are incarcerated experience a higher prevalence of gynecologic malignancies and present with higher stage disease, which may be contributing to the greater mortality from cancer than the age-adjusted US population. Limited access to guideline-recommended screening and prevention and resource limitations across correctional facilities may result in gynecologic cancer disparities. Reasons for delayed gynecologic cancer care in prisons remain underexplored. Therefore, we sought to identify contributors to delayed gynecologic cancer care among women experiencing incarceration.
Methods:
Women at a single tertiary center in the Southeastern U.S. who were incarcerated and were diagnosed with a gynecologic cancer during 2014-2021 were identified in the electronic medical record. Note text was extracted and contributors to delay were identified and categorized using the RADaR method. Descriptive statistics were used to assess quantitative data.
Results:
14 patients were identified with a total of 14,879 text excerpts. Data reduction was performed to identify excerpts that were relevant to the central research question resulting in 175 relevant note excerpts. Delays prior to the tertiary care visit included patient and institutional contributors. Delays during transition from the tertiary center to prison included discharge planning and loss to follow-up during/after incarceration. Transportation, authorization, and restraints were concrete contributors. Abstract contributors included communication, and the patient's emotional experience.
Conclusions:
We identify myriad contributors to delayed or fractured gynecologic cancer care in women experiencing incarceration. The impact of these issues warrants further study and intervention to improve care.
Related Concept Videos
 01:21
Types of Reports II: Incident or Occurrence Report
Purposes:
In the healthcare industry, reports play a crucial role in documenting incidents within an agency. The primary objective of these reports is to ensure patient safety, uphold the...
 01:24
Disorders of the Female Reproductive System
 01:21
Cancer Survival Analysis
 01:27
Nursing Ethical Principles II
Consider the following scenario, which illustrates how these principles are applied in the care of Mr. John, a fifty-year-old teacher diagnosed with metastatic liver cancer.
Initially, Mr. John's...
 02:07
Oogenesis
 01:30
Specialized Care Centers and Settings-II
Rural health centers are specialized care facilities in remote locations with very few medical personnel. The primary care providers who run the centers are mostly Registered Nurse Practitioners. Here, emergency treatment is provided to critically ill or injured patients before they are transferred to the closest hospital. Fortunately, due to advancement in technology, many rural healthcare facilities and professionals have easy access to diagnostic and treatment...