Related Experiment Video
Updated: Jul 24, 2025
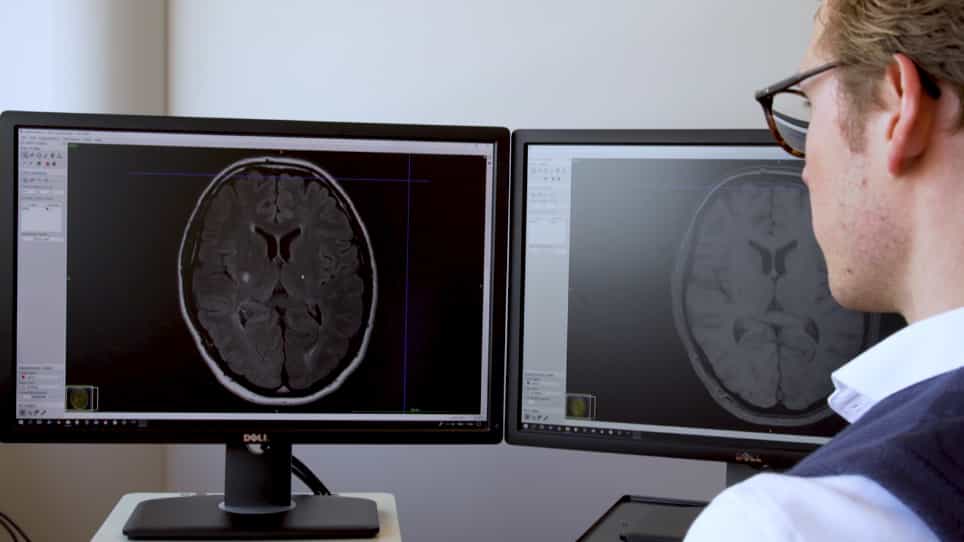
Brain Infarct Segmentation and Registration on MRI or CT for Lesion-symptom Mapping
Published on: September 25, 2019
Anatomical predictors of need for decompressive craniectomy after stroke using voxel-based lesion symptom mapping
Margy McCullough-Hicks1, Karan Topiwala1, Soren Christensen2
1Department of Neurology, University of Minnesota, Minneapolis, Minnesota, USA.

Background And Purpose:
Malignant cerebral edema (MCE) secondary to ischemic stroke is a highly morbid condition. Decompressive craniectomy (DC) is the only treatment for MCE that has been shown to reduce mortality. We examined whether early infarction and/or hypoperfusion in specific topographic regions was predictive of the need for later DC.
Methods:
A retrospective database of patients evaluated for large vessel occlusion (LVO) stroke at Stanford between 2010 and 2019 was used. Thirty patients with LVO and baseline perfusion MRI who underwent DC were evaluated. Propensity matching based on age, lesion size, and recanalization status was performed on the remaining cohort. Baseline masks of apparent diffusion coefficient (ADC) + Tmax >6 seconds lesions were generated using automated perfusion software. Voxel-based lesion symptom maping was used to perform logistic regression at each voxel to generate statistical maps of lesion location associated with DC. Hemispheres were combined to increase statistical power.
Results:
Sixty patients were analyzed. After adjusting for age, lesion size, and recanalization status as covariates, scattered cortical regions, predominately within the temporal and frontal lobe, were mildly to moderately predictive of the need for DC (z-scores: 2.4-6.74, p < .01).
Conclusions:
Scattered temporal and frontal lobe regions on baseline diffusion and perfusion MRI were found to be mildly to moderately predictive of the need for subsequent DC in patients with LVO stroke.
Insights
Early signs of infarction and hypoperfusion in the temporal and frontal lobes may predict the need for decompressive craniectomy (DC) in ischemic stroke patients. This finding aids in identifying patients who may benefit from this life-saving procedure.
Area of Science:
- Neurology
- Radiology
- Neurosurgery
Background:
- Malignant cerebral edema (MCE) following ischemic stroke significantly increases mortality.
- Decompressive craniectomy (DC) is the sole established treatment to reduce MCE-related mortality.
Purpose of the Study:
- To investigate if early infarction or hypoperfusion in specific brain regions predicts the necessity for DC.
- To identify topographic patterns on baseline MRI that correlate with the need for DC.
Main Methods:
- Retrospective analysis of 60 patients with large vessel occlusion (LVO) stroke who underwent DC.
- Utilized perfusion MRI (ADC + Tmax > 6s lesions) and voxel-based lesion symptom mapping.
- Employed propensity matching for age, lesion size, and recanalization status.
Main Results:
- Scattered cortical regions, particularly in the temporal and frontal lobes, showed a mild to moderate predictive value for DC.
- Statistical analysis (z-scores: 2.4-6.74, p < .01) confirmed the association between these regions and the need for DC.
Conclusions:
- Baseline diffusion and perfusion MRI findings in scattered temporal and frontal lobe regions can predict the need for subsequent DC in LVO stroke patients.
- These imaging markers may assist in early patient selection for decompressive craniectomy.
More Related Videos
 12:50
Lesion Explorer: A Video-guided, Standardized Protocol for Accurate and Reliable MRI-derived Volumetrics in Alzheimer's Disease and Normal Elderly
Published on: April 14, 2014
 05:32
Author Spotlight: Assessing Ischemic Stroke Damage Through Middle Cerebral Artery Occlusion Model
Published on: August 11, 2023