Related Experiment Video
Updated: Jul 24, 2025
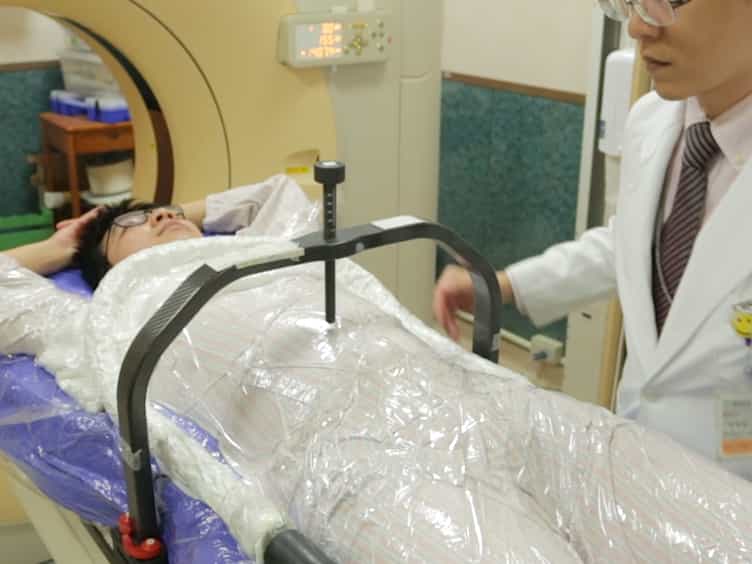
Treatment of Liver Metastases Using an Internal Target Volume Method for Stereotactic Body Radiotherapy
Published on: May 8, 2018
Checkpoint Inhibitors in Combination With Stereotactic Body Radiotherapy in Patients With Advanced Solid Tumors: The
Mathieu Spaas1, Nora Sundahl2, Vibeke Kruse3
1Department of Radiation Oncology, Ghent University Hospital, Ghent University, Ghent, Belgium.

Importance:
Although immune checkpoint inhibitors (ICIs) targeting programmed cell death 1 (PD-1) and PD-1 ligand 1 have improved the outcome for many cancer types, the majority of patients fails to respond to ICI monotherapy. Hypofractionated radiotherapy has the potential to improve the therapeutic ratio of ICIs.
Objective:
To assess the addition of radiotherapy to ICIs compared with ICI monotherapy in patients with advanced solid tumors.
Design, Setting, And Participants:
This open-label, multicenter, randomized phase 2 trial was conducted in 5 Belgian hospitals and enrolled participants between March 2018 and October 2020. Patients 18 years or older with locally advanced or metastatic melanoma, renal cell carcinoma, urothelial carcinoma, head and neck squamous cell carcinoma, or non-small cell lung carcinoma were eligible. A total of 99 patients were randomly assigned to either the control arm (n = 52) or the experimental arm (n = 47). Of those, 3 patients (1 in the control arm vs 2 in the experimental arm) withdrew consent and thus were not included in the analysis. Data analyses were performed between April 2022 and March 2023.
Interventions:
Patients were randomized (1:1) to receive anti-PD-1/PD-1 ligand 1 ICIs alone as per standard of care (control arm) or combined with stereotactic body radiotherapy 3 × 8 gray to a maximum of 3 lesions prior to the second or third ICI cycle, depending on the frequency of administration (experimental arm). Randomization was stratified according to tumor histologic findings and disease burden (3 and fewer or more than 3 cancer lesions).
Main Outcomes And Measures:
The primary end point was progression-free survival (PFS) as per immune Response Evaluation Criteria in Solid Tumors. Key secondary end points included overall survival (OS), objective response rate, local control rate, and toxic effects. Efficacy was assessed in the intention-to-treat population, while safety was evaluated in the as-treated population.
Results:
Among 96 patients included in the analysis (mean age, 66 years; 76 [79%] female), 72 (75%) had more than 3 tumor lesions and 65 (68%) had received at least 1 previous line of systemic treatment at time of inclusion. Seven patients allocated to the experimental arm did not complete the study-prescribed radiotherapy course due to early disease progression (n = 5) or intercurrent illness (n = 2). With a median (range) follow-up of 12.5 (0.7-46.2) months, median PFS was 2.8 months in the control arm compared with 4.4 months in the experimental arm (hazard ratio, 0.95; 95% CI, 0.58-1.53; P = .82). Between the control and experimental arms, no improvement in median OS was observed (11.0 vs 14.3 months; hazard ratio, 0.82; 95% CI, 0.48-1.41; P = .47), and objective response rate was not statistically significantly different (22% vs 27%; P = .56), despite a local control rate of 75% in irradiated patients. Acute treatment-related toxic effects of any grade and grade 3 or higher occurred in 79% and 18% of patients in the control arm vs 78% and 18% in the experimental arm, respectively. No grade 5 adverse events occurred.
Conclusions And Relevance:
This phase 2 randomized clinical trial demonstrated that while safe, adding subablative stereotactic radiotherapy of a limited number of metastatic lesions to ICI monotherapy failed to show improvement in PFS or OS.
Trial Registration:
ClinicalTrials.gov Identifier: NCT03511391.

Related Concept Videos
 02:56
Treatment Resistant Cancers
 02:57
Targeted Cancer Therapies
There are several types of targeted therapies against...
 01:27
Tumor Immunotherapy
 02:49
Cancer Therapies
However, cancer treatments can pose several challenges, as therapies used to kill cancer cells are generally also toxic to normal cells. Moreover, cancer cells mutate rapidly and can develop resistance to chemical agents or radiation therapy. Besides, all types of cancer cells may not respond to the same therapy. Some cancer cells respond to one...
 01:29
Chemotherapy-Induced Nausea and Vomiting: Dopamine Receptor Antagonists
Phenothiazines, such as prochlorperazine...
 01:27
Chemotherapy-Induced Nausea and Vomiting: 5-HT3 Receptor Antagonists