Related Experiment Video
Updated: Jul 23, 2025


Vessel-sparing Excision and Primary Anastomosis
Published on: January 7, 2019
Anal incontinence following obstetric anal sphincter injury: Is there a difference between subtypes? A systematic
Martino Maria Zacchè1, Jayasish Ghosh2, Ilias Liapis1
1Department of Obstetrics and Gynaecology, Birmingham Women's Hospital, Birmingham, UK.

Aims:
Obstetric anal sphincter injury (OASI) is associated with long-term anal incontinence (AI). We aimed to address the following questions: (a) are women with major OASI (grade 3c and 4) at higher risk of developing AI when compared to women with minor OASI (grade 3a and 3b)? (b) is a fourth-degree tear more likely to cause AI over a third-degree tear?
Methods:
A systematic literature search from inception until September 2022. We considered prospective and retrospective cohort studies, cross-sectional and case-control studies without language restrictions. The quality was assessed by the Newcastle-Ottawa Scale and the Joanna Briggs Institute critical appraisal checklist. Risk ratios (RRs) were calculated to measure the effect of different grades of OASI.
Results:
Out of 22 studies, 8 were prospective cohort, 8 were retrospective cohort, and 6 were cross-sectional studies. Length of follow-up ranged from 1 month to 23 years, with the majority of the reports (n = 16) analysing data within 12-months postpartum. Third-degree tears evaluated were 6454 versus 764 fourth-degree tears. The risk of bias was low in 3, medium in 14 and high in 5 studies, respectively. Prospective studies showed that major tears are associated with a twofold risk of AI for major tears versus minor tears, while retrospective studies consistently showed a risk of fecal incontinence (FI) which was two- to fourfold higher. Prospective studies showed a trend toward worsening AI symptoms for fourth-degree tears, but this failed to reach statistical significance. Cross-sectional studies with long-term (≥5 years) follow-up showed that women with fourth-degree tear were more likely to develop AI, with an RR ranging from 1.4 to 2.2. Out of 3, 2 retrospective studies showed similar findings, but the follow-up was significantly shorter (≤1 year). Contrasting results were noted for FI rates, as only 5 out of 10 studies supported an association between fourth-degree tear and FI.
Conclusions:
Most studies investigate bowel symptoms within few months from delivery. Data heterogeneity hindered a meaningful synthesis. Prospective cohort studies with adequate power and long-term follow-up should be performed to evaluate the risk of AI for each OASI subtype.
More Related Videos
 03:49
Anogenital Distance and Perineal Measurements of the Pelvic Organ Prolapse POP Quantification System
Published on: September 20, 2018
 07:41
Quantification of Levator Ani Hiatus Enlargement by Magnetic Resonance Imaging in Males and Females with Pelvic Organ Prolapse
Published on: April 17, 2019
Related Concept Videos
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:26
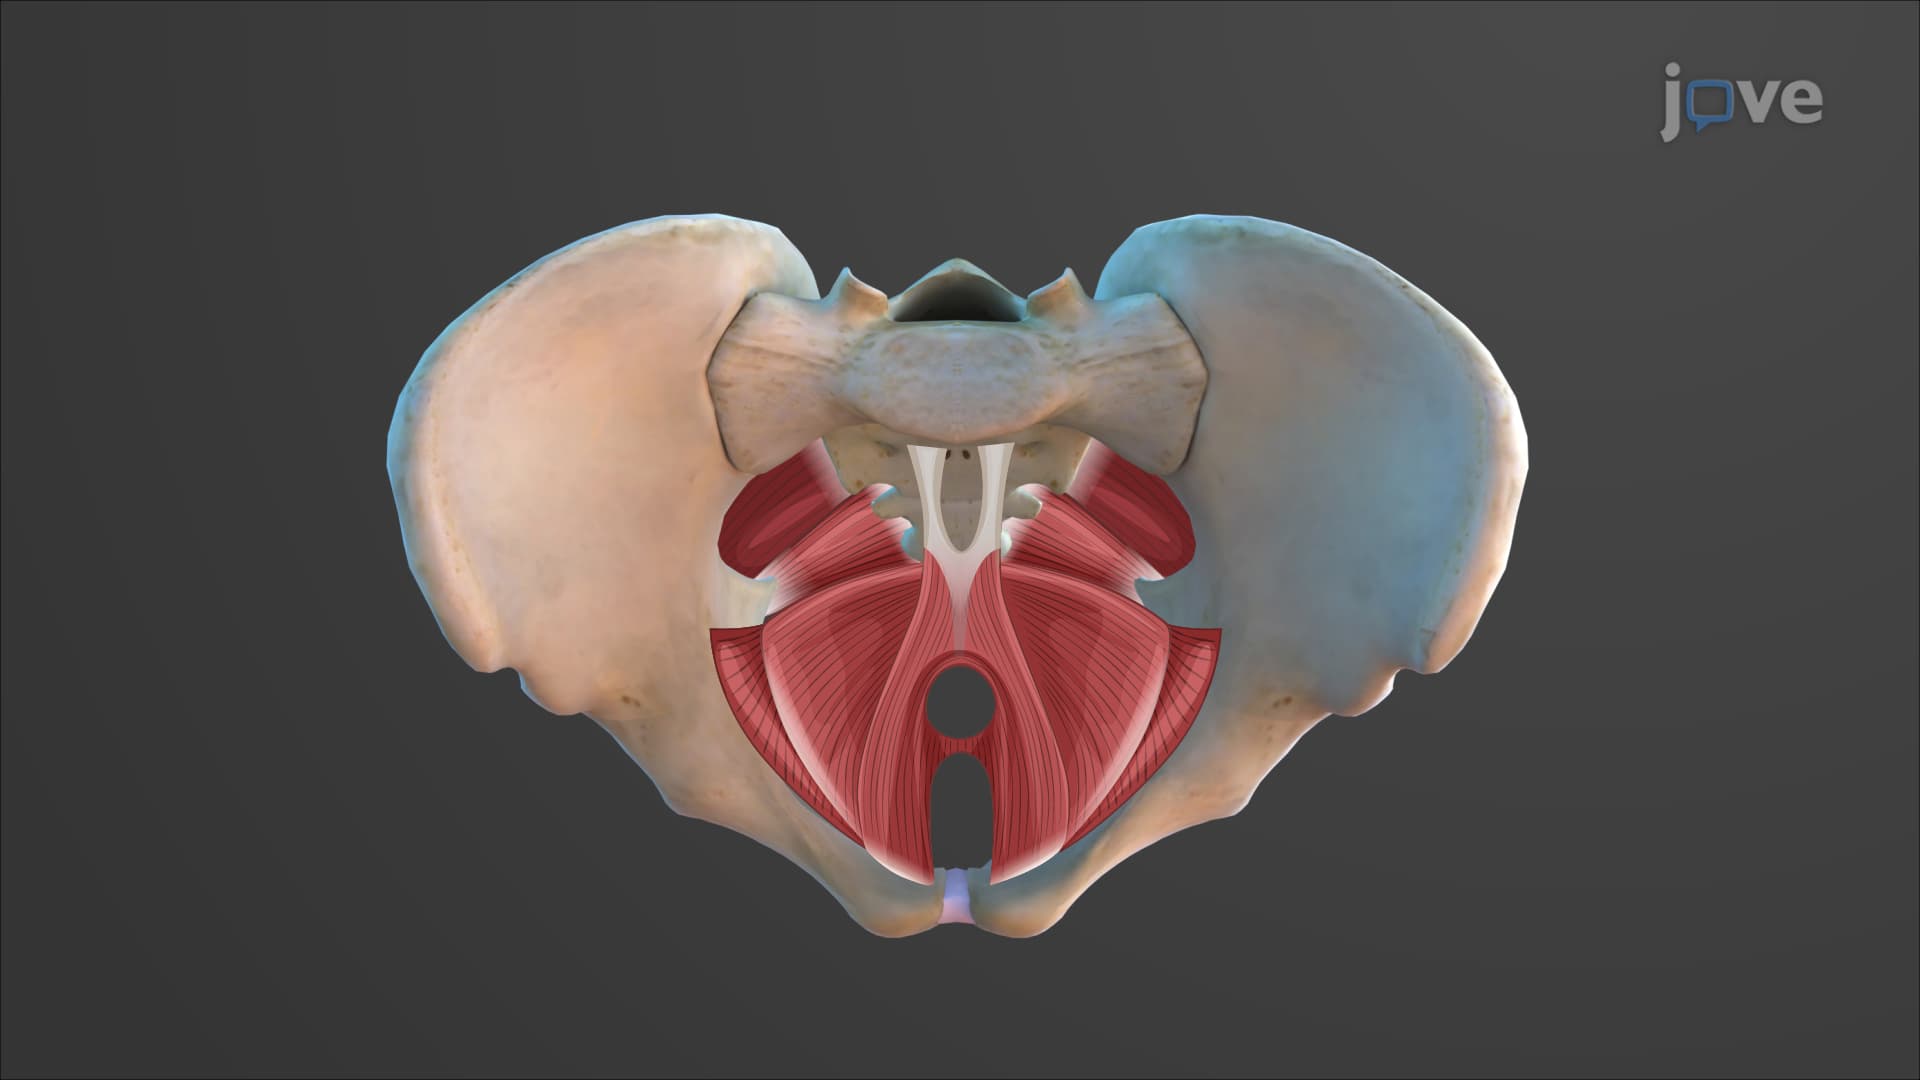
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...