Related Experiment Video
Updated: Jul 23, 2025


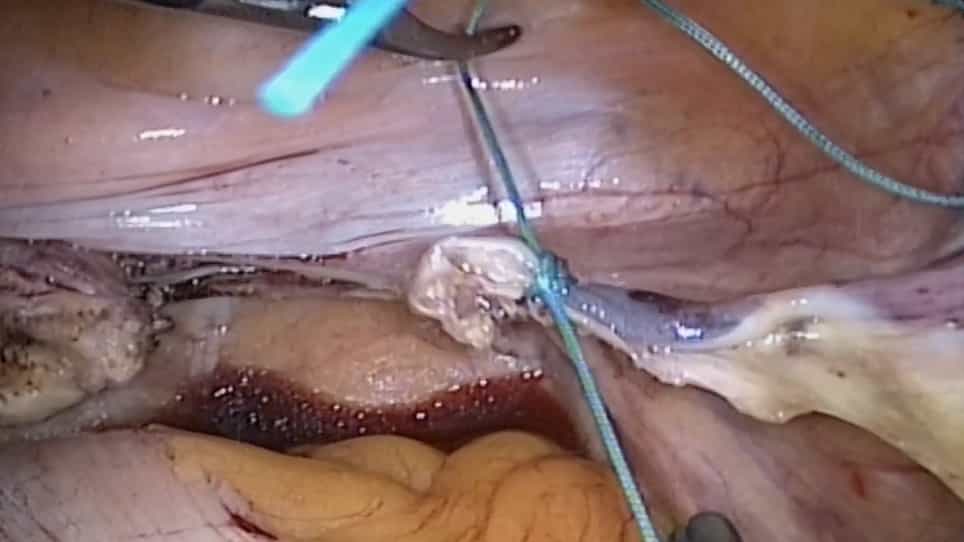
Author Spotlight: Advancing Pelvic Prolapse Treatment with a Non-Mesh Approach using Laparoscopic Pectopexy
Published on: October 25, 2024
Oestrogen therapy for treating pelvic organ prolapse in postmenopausal women
Annika Taithongchai1, Eugenie E Johnson2,3, Sharif I Ismail4
1Department of Obstetrics and Gynaecology, King's College Hospital, London, UK.

Background:
Pelvic organ prolapse (POP) is the descent of a woman's uterus, bladder, or rectum into the vagina. It affects 50% of women over 50 years old who have given birth to at least one child, and recognised risk factors are older age, higher number of births, and higher body mass index. This review assesses the effects of oestrogen therapy, alone or in combination with other treatments, on POP in postmenopausal women.
Objectives:
To assess the benefits and harms of local and systemic oestrogen therapy in the management of pelvic organ prolapse symptoms in postmenopausal women, and to summarise the principal findings of relevant economic evaluations.
Search Methods:
We searched the Cochrane Incontinence Specialised Register (up to 20 June 2022), which includes CENTRAL, MEDLINE, two trials registers, and handsearching of journals and conference proceedings. We also checked the reference lists of relevant articles for additional studies.
Selection Criteria:
We included randomised controlled trials (RCTs), quasi-RCTs, multi-arm RCTs, and cross-over RCTs that evaluated the effects of oestrogen therapy (alone or in combination with other treatments) versus placebo, no treatment, or other interventions in postmenopausal women with any grade of POP.
Data Collection And Analysis:
Two review authors independently extracted data from the included trials using prespecified outcome measures and a piloted extraction form. The same review authors independently assessed the risk of bias of eligible trials using Cochrane's risk of bias tool. Had data allowed, we would have created summary of findings tables for our main outcome measures and assessed the certainty of the evidence using GRADE.
Main Results:
We identified 14 studies including a total of 1002 women. In general, studies were at high risk of bias in terms of blinding of participants and personnel, and there were also some concerns about selective reporting. Owing to insufficient data for the outcomes of interest, we were unable to perform our planned subgroup analyses (systemic versus topical oestrogen, parous versus nulliparous women, women with versus without a uterus). No studies assessed the effects of oestrogen therapy alone versus no treatment, placebo, pelvic floor muscle training, devices such as vaginal pessaries, or surgery. However, we did identify three studies that assessed oestrogen therapy in conjunction with vaginal pessaries versus vaginal pessaries alone and 11 studies that assessed oestrogen therapy in conjunction with surgery versus surgery alone.
Authors' Conclusions:
There was insufficient evidence from RCTs to draw any solid conclusions on the benefits or harms of oestrogen therapy for managing POP symptoms in postmenopausal women. Topical oestrogen in conjunction with pessaries was associated with fewer adverse vaginal events compared with pessaries alone, and topical oestrogen in conjunction with surgery was associated with reduced postoperative urinary tract infections compared with surgery alone; however, these findings should be interpreted with caution, as the studies that contributed data varied substantially in their design. There is a need for larger studies on the effectiveness and cost-effectiveness of oestrogen therapy, used alone or in conjunction with pelvic floor muscle training, vaginal pessaries, or surgery, for the management of POP. These studies should measure outcomes in the medium and long term.

Related Concept Videos
 01:28
Menopause
 02:07
Oogenesis
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:22
Mitral Valve Prolapse II: Assessment and Management
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH...