Related Experiment Video
Updated: Jul 23, 2025

Assessment of Vascular Function in Patients With Chronic Kidney Disease
Published on: June 16, 2014
Insulin growth factor axis and cardio-renal risk in diabetic kidney disease: an analysis from the CREDENCE trial
Reza Mohebi1, Yuxi Liu1, Michael K Hansen2
1Cardiology Division, Massachusetts General Hospital and Harvard Medical School, 55 Fruit Street, Boston, MA, 02114, USA.

Background:
The insulin-like growth factors (IGF) play a crucial role in regulating cellular proliferation, apoptosis, and key metabolic pathways. The ratio of IGF-1 to IGF binding protein-3 (IGFBP-3) is an important factor in determining IGF-1 bioactivity. We sought to investigate the association of IGF-1 and IGFBP-3 with cardio-renal outcomes among persons with type 2 diabetes.
Methods:
Samples were available from 2627 individuals with type 2 diabetes and chronic kidney disease that were randomized to receive canagliflozin or placebo and were followed up for incident cardio-renal events. Primary outcome was defined as a composite of end-stage kidney disease, doubling of the serum creatinine level, or renal/cardiovascular death. IGF-1 and IGFBP-3 were measured at baseline, Year-1 and Year-3. Elevated IGF-1 level was defined according to age-specific cutoffs. Cox proportional hazard regression was used to investigate the association between IGF-1 level, IGFBP-3, and the ratio of IGF-1/IGFBP-3 with clinical outcomes.
Results:
Elevated IGF-1 was associated with lower glomerular filtration rate at baseline. Treatment with canagliflozin did not significantly change IGF-1 and IGFBP-3 concentrations by 3 years (p-value > 0.05). In multivariable models, elevated IGF-1 (above vs below age-specific cutoffs) was associated with the primary composite outcome (incidence rate:17.8% vs. 12.7% with a hazard ratio [HR]: 1.52; 95% confidence interval CI 1.09-2.13;P: 0.01), renal composite outcome (HR: 1.65; 95% CI 1.14-2.41; P: 0.01), and all-cause mortality (HR: 1.52; 95% CI 1.00-2.32; P; 0.05). Elevations in log IGFBP-3 did not associate with any clinical outcomes. Increase in log IGF-1/IGFBP-3 ratio was also associated with a higher risk of the primary composite outcome (HR per unit increase: 1.57; 95% CI 1.09-2.26; P; 0.01).
Conclusions:
These results further suggest potential importance of IGF biology in the risk for cardio-renal outcomes in type 2 diabetes. SGLT2 inhibition has no impact on the biology of IGF despite its significant influence on outcomes.
Trial Registration:
CREDENCE; ClinicalTrials.gov Identifier: NCT02065791.
More Related Videos
 10:31
Comparative Proteomic Analysis of Whole Kidney, Medulla, and Cortical Tubules in Diabetic Pathogenesis of Kidney Injury in Mice
Published on: May 2, 2025
 08:15
Author Spotlight: Network Pharmacology and Molecular Docking to Decipher the Action of Jiawei Shengjiang San Against Diabetic Kidney Disease
Published on: May 10, 2024
Related Concept Videos
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:06
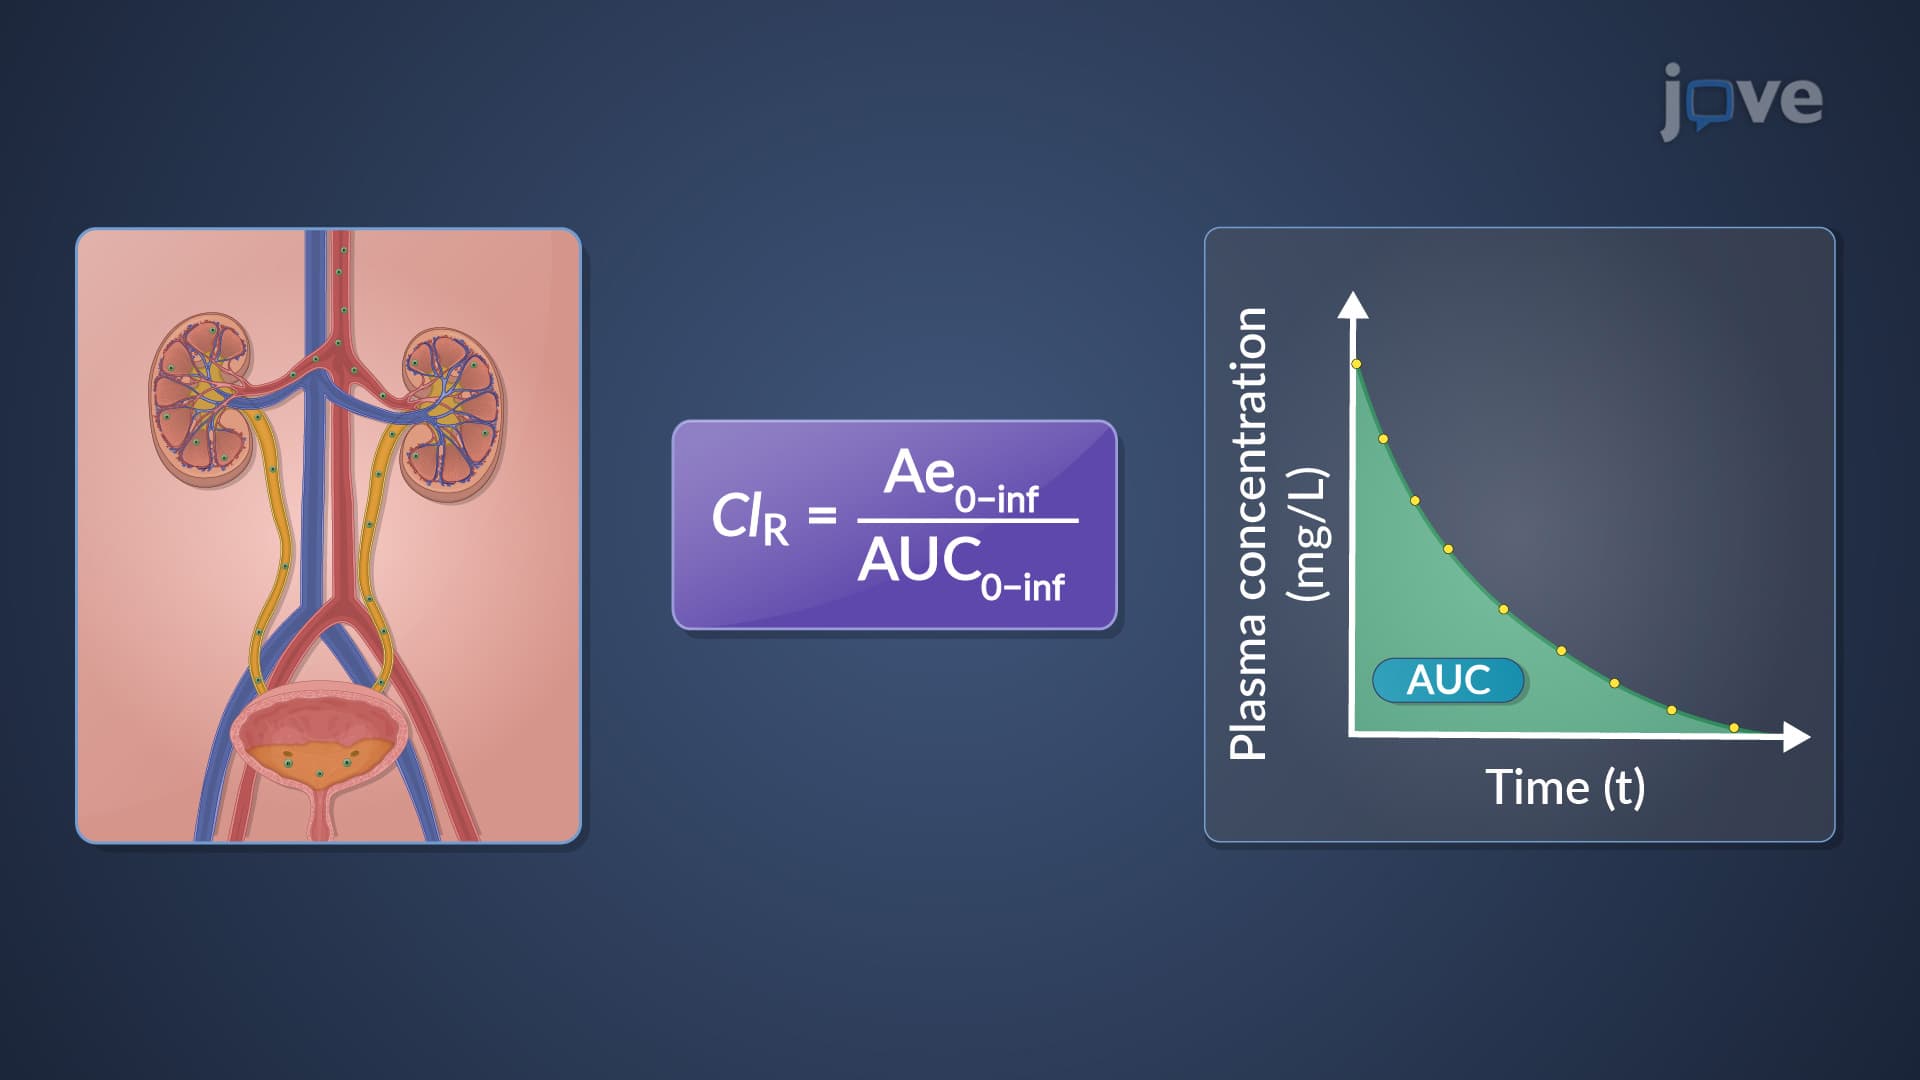
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:17
Factors Affecting Renal Clearance: Renal Impairment
One condition associated with renal failure is uremia. Uremia is characterized by impaired glomerular filtration and fluid accumulation in the body. This condition hinders the renal clearance of drugs, resulting in drug accumulation and potential...
 01:22
Heart Failure Drugs: Diuretics