Concomitant evaluation of cardiovascular and cerebrovascular controls via Geweke spectral causality to assess the propensity to postural syncope
Related Experiment Video
Updated: Jul 23, 2025
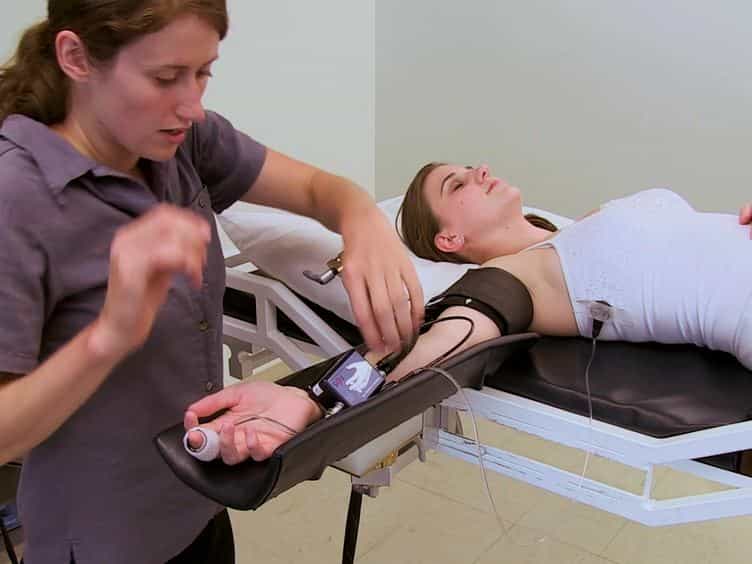
Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
Alberto Porta1,2, Francesca Gelpi3, Vlasta Bari3,4
1Department of Biomedical Sciences for Health, University of Milan, 20133, Milan, Italy. alberto.porta@unimi.it.

Insights
Individuals prone to fainting (syncope) show impaired coordination between cardiovascular and cerebrovascular systems during postural changes. This suggests a loss of baroreflex function and weakened cerebral autoregulation contribute to syncope risk.
Area of Science:
- Cardiovascular Physiology
- Neuroscience
- Biomedical Engineering
Background:
- Postural syncope evaluation requires understanding cardiovascular and cerebrovascular control.
- Disentangling causal relationships in physiological systems is crucial for accurate assessment.
Purpose of the Study:
- To apply Geweke spectral causality (GSC) for analyzing cardiovascular and cerebrovascular control during postural challenges.
- To compare GSC's effectiveness across different linear model structures.
- To identify physiological markers associated with orthostatic syncope susceptibility.
Main Methods:
- Geweke spectral causality (GSC) was used to analyze heart period, systolic arterial pressure, mean arterial pressure, and mean cerebral blood velocity variability.
- Data were collected from 13 control subjects and 13 individuals prone to syncope at rest and during 60° head-up tilt.
- Two linear model structures (bivariate autoregressive and dynamic adjustment) were compared.
Main Results:
- GSC markers were independent of the chosen linear model structure.
- Simultaneous analysis of cardiovascular and cerebrovascular control enhanced understanding of postural disturbances.
- Orthostatic syncope was linked to a loss of coordinated baroreflex feedback and mechanical feedforward pathways.
- Weakened cerebral autoregulation was indicated by an increased pressure-to-flow link in the respiratory band.
Conclusions:
- GSC is a valuable tool for assessing cardiovascular and cerebrovascular interactions during postural changes.
- Impaired baroreflex coordination and reduced cerebral autoregulation are key factors in orthostatic syncope.
- GSC can aid in monitoring physiological disturbances related to posture modification.
Abstract:
The evaluation of propensity to postural syncope necessitates the concomitant characterization of the cardiovascular and cerebrovascular controls and a method capable of disentangling closed loop relationships and decomposing causal links in the frequency domain. We applied Geweke spectral causality (GSC) to assess cardiovascular control from heart period and systolic arterial pressure variability and cerebrovascular regulation from mean arterial pressure and mean cerebral blood velocity variability in 13 control subjects and 13 individuals prone to develop orthostatic syncope. Analysis was made at rest in supine position and during head-up tilt at 60°, well before observing presyncope signs. Two different linear model structures were compared, namely bivariate autoregressive and bivariate dynamic adjustment classes. We found that (i) GSC markers did not depend on the model structure; (ii) the concomitant assessment of cardiovascular and cerebrovascular controls was useful for a deeper comprehension of postural disturbances; (iii) orthostatic syncope appeared to be favored by the loss of a coordinated behavior between the baroreflex feedback and mechanical feedforward pathway in the frequency band typical of the baroreflex functioning during the postural challenge, and by a weak cerebral autoregulation as revealed by the increased strength of the pressure-to-flow link in the respiratory band. GSC applied to spontaneous cardiovascular and cerebrovascular oscillations is a promising tool for describing and monitoring disturbances associated with posture modification.

Related Concept Videos
 01:23
Assessment of the Cardiovascular System I: Subjective Data
Initial Enquiry
Ask the patient about their primary concern and thoroughly explore all reported symptoms.
Medical History
Investigate past illnesses affecting the cardiovascular system, such as angina, anemia, rheumatic fever, congenital heart disease, stroke, thrombophlebitis, dysrhythmias, varicosities
Inquire about symptoms...
 01:30
Dysrhythmias V: Evaluating Dysrhythmias
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:25
Assessment of the Cardiovascular System IV: Auscultation
Normal Heart Sounds
S1 (First Heart Sound)-
S1 is made by the closure of the mitral and tricuspid valves (atrioventricular valves), marking the beginning of systole.
S2 (Second Heart Sound)-
S2 is made by the closure of the aortic and pulmonic valves (semilunar valves), marking the end of the systole.
 01:25
Correlation between ECG and Cardiac Cycle
A cardiac action potential originates in the SA node and spreads throughout the atria and the AV node in approximately 0.03 seconds. This results in the P wave in an ECG and triggers atrial contraction. The action potential is then briefly slowed at the AV node, allowing the atria to contract and fill the ventricles with blood before...