Related Experiment Video
Updated: Jul 23, 2025


Isolation and Quantification of Botulinum Neurotoxin From Complex Matrices Using the BoTest Matrix Assays
Published on: March 3, 2014
Botulism due to Injection Drug Use
Timothy Hoffman1, Jennifer Yee1
1The Ohio State University, Department of Emergency Medicine, Columbus, OH.

Audience:
This scenario was developed to educate emergency medicine residents on the diagnosis and management of wound botulism secondary to injection drug use.
Introduction:
Botulism is a relatively rare cause of respiratory failure and descending weakness in the United States, caused by prevention of presynaptic acetylcholine release at the neuromuscular junction. This presentation has several mimics, including myasthenia gravis and the Miller-Fisher variant of Guillain-Barré. It may be caused by ingestion of spores (infant), ingestion of pre-formed toxin (food-borne), formation of toxin in vivo (wound-associated cases), through weaponized sources, or through inappropriately administered injections (iatrogenic). Cases of black tar heroin injection have been associated with botulism. Regardless of the etiology, prompt assessment and support of respiratory muscle strength and ordering antidotal therapy is key to halting further muscle weakness progression.
Educational Objectives:
At the conclusion of the simulation session, learners will be able to: 1) Identify the different etiologies of botulism, including wound, food-borne, infant, iatrogenic, and inhalational sources, 2) describe the pathophysiology of botulism toxicity and how it prevents presynaptic acetylcholine release at the neuromuscular junction, 3) develop a differential for bilateral descending muscle weakness, 4) compare and contrast presentations of myasthenia gravis, botulism, and the Miller-Fisher variant of Guillain-Barré syndrome, 5) describe measurement of neurologic respiratory parameter testing, such as negative inspiratory force, 6) outline treatment principles of wound-associated botulism, including antitoxin administration, wound debridement, tetanus vaccination, and evaluation for the need of antibiotics, and 7) identify appropriate disposition of the patient to the medical intensive care unit (ICU).
Educational Methods:
This session was conducted using high-fidelity simulation, followed by a debriefing session and lecture on the diagnosis, differential diagnosis, and management of botulism secondary to injection drug use. Debriefing methods may be left to the discretion of participants, but the authors have utilized advocacy-inquiry techniques. This scenario may also be run as an oral board case.
Research Methods:
Our residents are provided a survey at the completion of the debriefing session so they may rate different aspects of the simulation, as well as provide qualitative feedback on the scenario.
Results:
Sixteen learners completed a feedback form. This session received all six and seven scores (consistently effective/very good and extremely effective/outstanding, respectively) other than three isolated five scores. The form also includes an area for general feedback about the case at the end. Illustrative examples of feedback include: "Really awesome debrief, breakdown of pathophysiology and clinical applications. Great work!"; "Great case with awesome learning points," and "Loved this session. Rare case but very great learning." Specific scores are available upon request.
Discussion:
This is a cost-effective method for reviewing botulism diagnosis and management. The case may be modified for appropriate audiences, such as using classic illness scripting (eg, ingestion of canned foods). We encourage readers to utilize a standardized patient to demonstrate extraocular muscle weakness and bulbar symptoms to increase psychological buy-in.
Topics:
Medical simulation, botulism, toxicologic emergencies, toxicology, neurology, emergency medicine.
More Related Videos
Related Concept Videos
 01:29
Drug Delivery: Parenteral Route
There are three primary parenteral routes: intravenous (IV), intramuscular (IM), and subcutaneous (SC). The IV route introduces the drug directly into the bloodstream, ensuring immediate action. The IM route...
 01:14
Prevention of Further Absorption of Poison
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 00:59
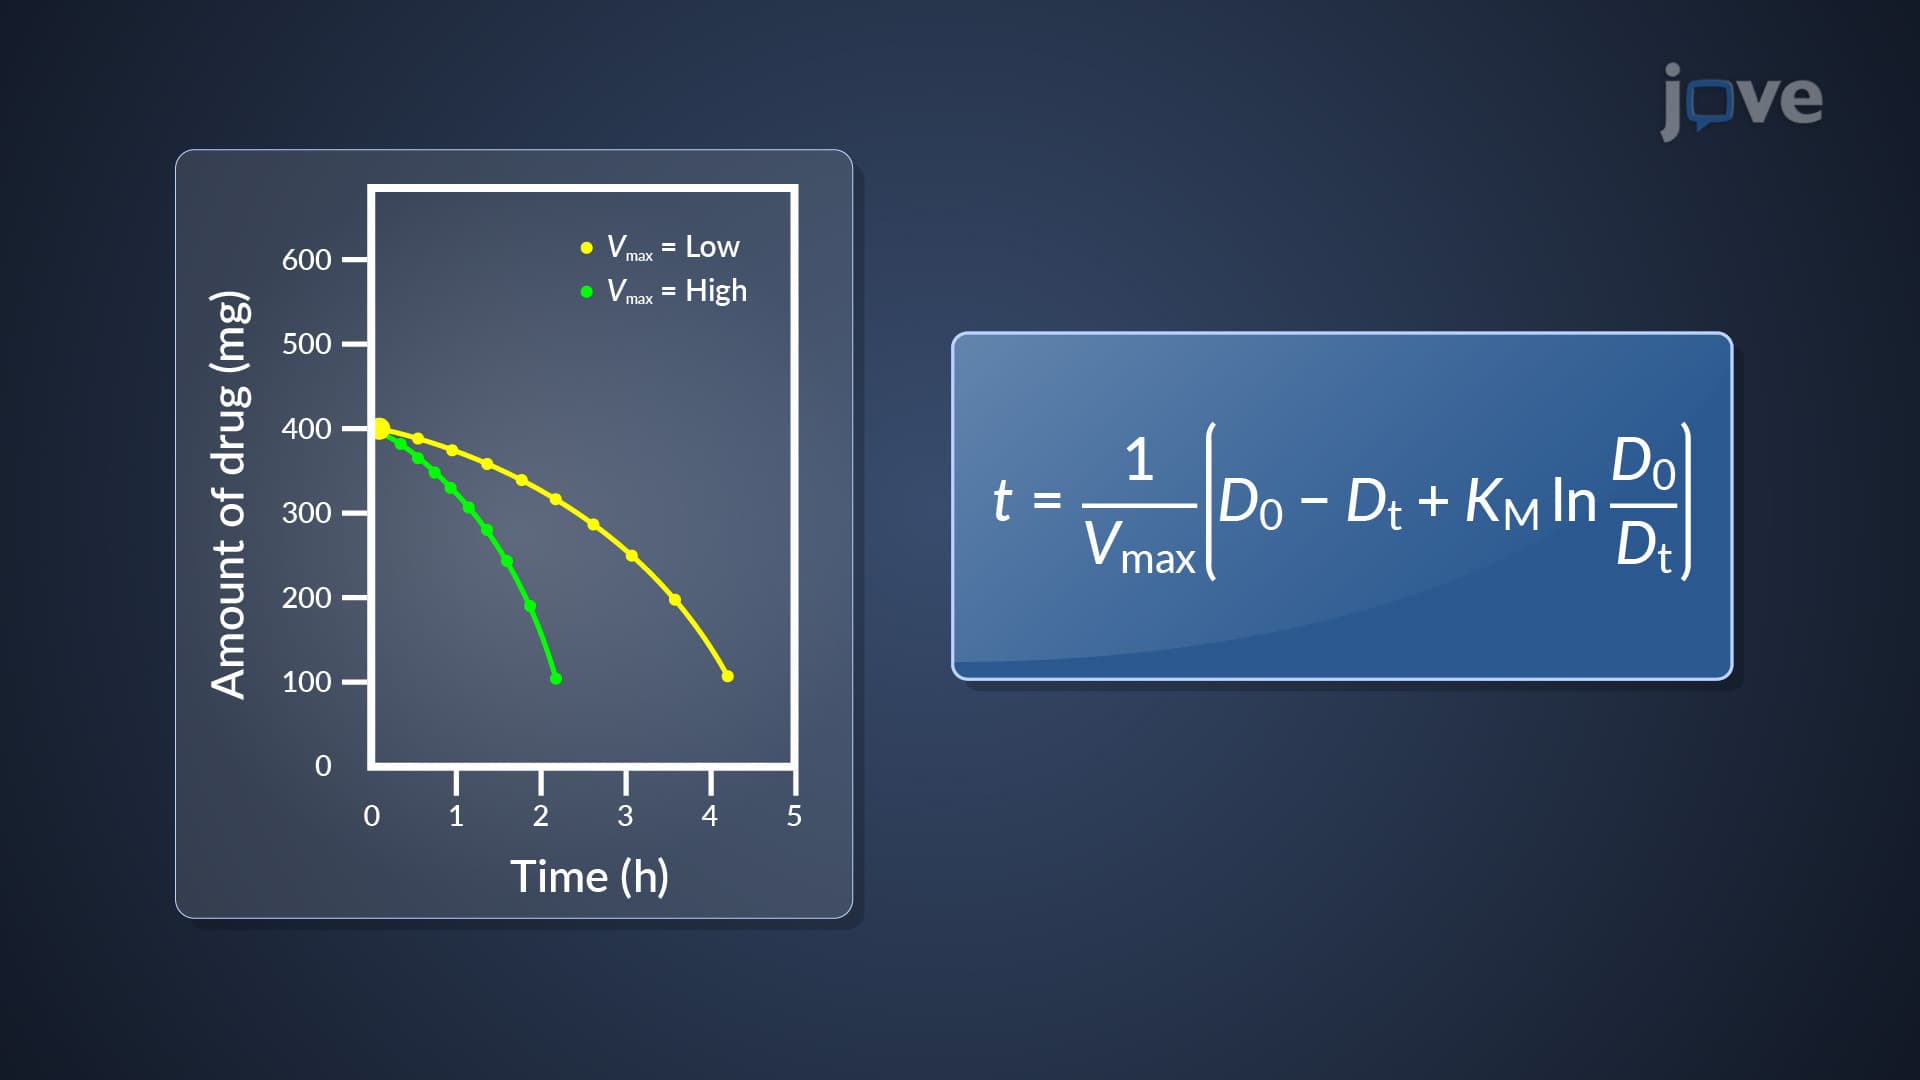
Nonlinear Pharmacokinetics: Drug Elimination for IV Bolus Injection
Following the administration of a single intravenous (IV) bolus injection, we can determine the concentration of the drug in the plasma at any given time. This calculation is achieved using a specific equation that integrates the values of Vmax and KM.
We can also...